
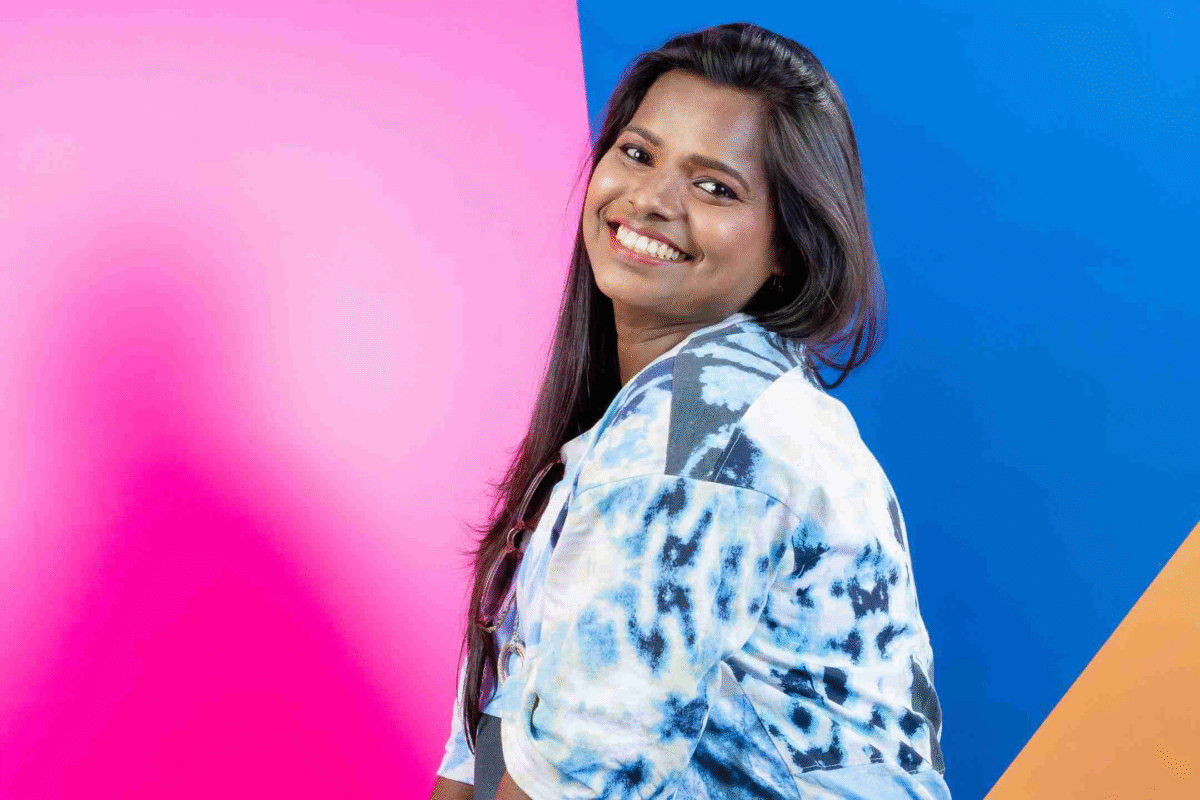
Sri Lanka’s Care System: Progress, Gaps, And Hope – Nimali Kumari

Sri Lanka’s Care System: Progress, Gaps, And Hope

What if turning 18 didn’t mean turning off support? We sit down with Nimmu, a powerhouse care leaver advocate from Sri Lanka, to map what’s changing, what still hurts, and how to build a system that puts children where they thrive—whether that’s family, kinship, or a short stay in residential care. With warmth and precision, Nimu explains Sri Lanka’s current landscape: most children live in Child Development Centres, foster care is in development, and adoption and kinship care remain key alternatives. She shares how things have improved—care plans, school access, and more respectful language—while spotlighting stubborn gaps like early exits at 15–16, patchy counselling, and the silent crisis of IDs and addresses that lock young adults out of services, votes, and formal work.

The conversation opens with a clear picture of Sri Lanka’s out-of-home care: most children live in Child Development Centres rather than foster care, with adoption and kinship care as alternatives. Nimmu, a formidable care leaver advocate, contrasts her experience from 15–20 years ago with the system today. She explains how many children still exit too early—sometimes at 15 or 16—when schooling stalls, and how preparation for independence has often been thin. Yet momentum is real: structured care plans, school access, and public understanding have improved, and there is a stronger refusal to use the word “orphan” when many children have living parents. The question shifts from “which setting?” to “which setting best meets this child’s needs now?”, anchoring the episode’s core message: the best place for a child is the place that offers safety, love, and stability, whether family, kinship, or temporary residential care.

A major advancement is Sri Lanka’s commitment to aftercare, including grants of two million rupees for eligible care leavers to buy land, rebuild, or secure housing. Nimmu celebrates this but flags equity gaps—older care leavers can miss out, and documentation barriers remain. IDs, birth records, and registered addresses are often incomplete, shutting people out of elections, services, and formal work. Psychological support has improved but can be episodic; counsellors arrive during crises, then disappear for months. Nimmu argues for preparation to start years before transition, with life skills, financial literacy, self-defence for girls, navigating public spaces, and consistent therapeutic support that also includes caregivers. You don’t need to be a therapist to be therapeutic, she notes; stable, kind, attentive adults heal, and trained “mothers” in centres can shift culture.

The heart of the episode is family strengthening. Nimmu believes institutionalisation should be a short, last-resort bridge, not a destination. She points to rising divorce and poverty as drivers of placement, arguing that targeted support—cash transfers, mediation, and practical aid—can keep more children at home. At school, younger teachers and peers are more inclusive, but stigma lingers when children are identified by their institution rather than their name. That language sticks and hurts. Healing requires identity, belonging, and dignity—starting with how we speak. Nimmu’s story shows how purpose transforms trauma: advocacy, education, and shared work turn pain into fuel for change, but not everyone carries that fire. Systems must hold those who cannot self-advocate with equal care.

Peer networks are the frontline. Nimmu co-founded Generation Never Give Up and Rise Together to connect hundreds of care leavers with jobs, legal support, hostel access, and higher education. Their next move is a transition home: a safe, non-stigmatising base where young people can work, study, return at night, and contribute to bills as they stabilise. The model recycles rent into the next person’s start, building solidarity and sustainability. Meanwhile, government discussions on documentation reform promise structural fixes long overdue. Globally, Nimmu is not alone. Care leavers are organising across regions, comparing policy wins and pitfalls, and raising a unified voice: don’t make children independent on a clock; make them ready with community, rights, and real options. The pathway forward is clear—invest early, keep families strong, professionalise caregiving, guarantee documents and housing, and treat care leavers as partners in policy, not passive recipients.

You can listen to the full podcast here:

You can watch here:

Transcript:

Colby: 0:00

Hello and welcome to the Secure Star podcast.

Nimmu: 0:05

They are giving 2 million per KR lever, so it means the thousand to the thousand KR levers to build a house or purchase a house. But I know that we are trying to do like uh decrease the number of the children’s uh child development centers in Sri Lanka, but I am pretty sure that it’s not going to be happening. I don’t want children to come into child development centers, and I just want to strengthen the family strengthening. Either it’s a family, either it’s a child development center, either it’s an adoption, or any other forms of like a post-op teachership. Where is the best place for the children? Children should be there. The counseling and psychological support only for the children who are living in CDC, also for the matrons, also for the caregivers should be there. So I’m happy as a careless in Sri Lanka, we are really strong and we are used to government level, we are used to like the private sectors, NGOs and INGs. So we are dealing with all of them. So they should be careful about that. The problems that we what we have faced, it will be not happened with them very soon.

Colby: 1:10

Hello and welcome to the Secure Star podcast. I’m Colby Pierce, and joining me for this episode is a leading care leaver voice in Sri Lanka. Before I introduce my guests, I’d just like to acknowledge the traditional custodians of the lands that I come to you from, the Ghana people of the Adelaide Plains, and acknowledge the continuing connection the living Ghana people feel to land, waters, culture, and community. I’d also like to pay my respects to their elders, past, present, and emerging. My guest this episode is Namali Kumari. Affectionately known as Nimu, Namali is a carelever from Sri Lanka who spent over a decade in institutional care. She holds a degree in journalism, advertising and mass communication from NIILM University in India, along with additional qualifications in criminal investigation, psychology, and social sciences. She has worked as a skill photographer and costume designer for the Indian film Dreams in 2013. Namali has represented Sri Lanka as a speaker at numerous international conferences, including those focused on child protection and women’s rights in Nepal in 2017 and the Baikon International Conference in India in 2018 and 21, in Nepal in 2023, and in Malaysia this past year. Recently, Namali also spoke at the 35th Vice International Conference in Croatia in 2024. That same year, Namali was honoured as a young changemaker by the UN Ambassador and Neon Media. She is an active member of the Global Care Leavers Committee and a member of Care Leaders Council. She represented South Asian care leavers in the UN Resolution Focus Group in 2019. She completed a justice-based approach foundation course at United Edge in the USA in 2021. Since 2021, Namali has appeared on various TV programs discussing her life experiences and has become a social media influencer. Drawing on her lived experience, she is a passionate advocate for children’s rights and alternative care. Namali’s work focuses on reuniting orphaned children with their families and ensuring that they have access to education and employment opportunities. She worked for one of the largest NGOs, Savadaya, for 10 years and later for the Egyptian Embassy. Currently, she is employed at Their Future Together in both the UK and Sri Lanka. She is registered as an alternative family and foster care manager and leads the foster care program, ensuring that children grow up in safe, loving families. Inspired by her own 15 years in orphanages, Namali co-founded the Asia First Care Leavers Network, Generation Never Give Up, in 2017. She also co-founded and currently works as director of Rise Together Care Leavers Leading Network. Recently, Namali launched her autobiography, The Caged Girl, A Journey to Justice, which translates into Sinala as Dumburu Pathuk. Welcome Nimali.

Nimmu: 5:26

Thank you so much.

Colby: 5:28

I think a few times in there I ran out of breath. So such a long and impressive bio. I was very keen to present it all. But uh the longer they are, the greater the opportunity for me to get my tongue in the way and and mispronounce things. So fortunately I can edit some of that out. So Namali, you did ask me, you did say to me that you prefer to be called Nimu, and I’ll have to remember that. Apologies if I do call you Namali again through the through the podcast. But Nimu, you are my first guest on the Secure Start podcast from Sri Lanka. Um I’m wondering if in the first instance, if you could tell us a little bit about the out-of-home care system in Sri Lanka.

Nimmu: 6:20

Okay, thank you so much, and I’m really happy to be here. So I will directly go into the answer. So, what I really feel like uh the system aftercare of the children who are leaving of the children’s homes. So currently we have 3563 children’s homes in Sri Lanka, so more than 9,191 children are residents in there. So uh I was uh uh a child who uh I think uh before 20 years, I was a child in child development centers because we are calling child development centers, not the CCI, like a child care institution. We are calling as a CDC. So in our CDCs, there is a system like um we after we uh turn out to 18, that’s we have to live. Uh I think it’s the global things that’s happening. But uh when it comes to Sri Lanka perspective, like uh for in our 12th, grade 12th means it’s a 13 years after study, uh we will reach out to 19, our age will be 19. So there the CDCs, CCI, which you are expecting, like they are not asking us to leave. If we are studying, they are not asking us to leave, and until 19 or 20, uh, if we are studying, that we can stay there. So after care, like when we leave, sometimes it can be after 15 years, sometimes it can be after 18 years or 19 years, because the 15 years is the age that the Sri Lankan children who set for the first ordinary level examination. Most of the children who are get past marks, they can sit for the another advanced level examination. Those who can’t afford for get them higher marks for that education system, they must leave the CDC. Because they are not uh most of the children are not getting the second chance to appear, second appear, which I got, but some institutions they are not getting the chance to do. So it means like most of the time, the 15 years or 16 years or so the age that the children are leaving the childcare institution. So when it’s come to uh aftercare, so there is no actually when I was there, so there were no actually the proper system to go out and have like not proper preparation for them, like a psychological support or financial uh training, or it can be like any vocational training. So it was not happened earlier, but currently, which is happening, like it’s already happening here currently. But the thing was that when I was there, there were no much um awareness on that how we can how we should go outside and how we should uh like uh deal with the people in the society because we just depended when we were in the child development centers. So we are hoping that someone will take care of us after we go out of the care. So it was the earlier system that uh children you must leave after 18 or after 19 or after 15 once they have done completed their education. So it can be the way that government is supporting to the uh youth, uh finding a job opportunities, or sometimes they used to get married, or sometimes they used to get like a vocational training, but where there are hostel facilities. The thing is that I was really wondering since that, like are they really going for their interesting because sometimes they like they would like to be uh become a uh a fashionable designer, but there will be uh courses uh only they are having the hostel facility, it’s gonna be the nurse, so they have to uh take out their dreams out and they should go there. So it’s something like that is happening, and uh the current time it’s uh we will speak in later, so it’s definitely changes, but the thing was that earlier it was like there were no proper system to go out, and that was the um aftercare uh aftercare things that what happened in Sri Lanka.

Colby: 10:12

Yeah, yeah. So you’ve got um the perspective of when you were in care um some years ago and and you you’re working in the care sector now. While you were speaking, I was just wondering was there a mix of development centers and foster care or foster home, or or was were children in care primarily in those development centers?

Nimmu: 10:37

Yeah, we we we have only this uh because we are not implementing foster care system now, it’s it’s still in Sri Lanka. So we have only child development centers, adaptation. So as an alternative, we have adoption and child development centers and the kinship care. So first is not still there, but uh currently it’s uh like in the on the process.

Colby: 10:56

In the process, yeah. And I I I nearly did the maths in my head and and gave it up pretty quickly. But um, what would you say is the kind of average number of children who are in each development center?

Nimmu: 11:12

Uh most of the time, some child development centers they have 22, 25.

Colby: 11:18

Yep.

Nimmu: 11:18

So we have the separation, like uh for girls there is separation, one for boys there’s a separation. So from these three, five, six uh children’s homes, there are 43 government-run child development centers. Others all are from the volunteer organization than NGOs.

Colby: 11:33

Yeah, yeah. And in the current system, what what do you think works well in Sri Lanka, the current out-of-home care system?

Nimmu: 11:44

Yeah, I’m so happy uh to share that uh uh as you know that uh the children who are leaving the child development centers, they really need the two uh place to stay. The housing issues, education support, and also the psychological support, uh, the financial support, these are the things that really uh want for the after care support as aftercare support. So, what currently uh the Sri Lankan government has taken uh forward to include the care leavers, we are calling as the carelivers. So include the care levers into their budget, and they have been taken forward to support the carelivers, like example, uh they are given two million per care lever, so it means the thousand to the thousand care levers to build a house or purchase a house or uh uh do uh uh like uh purchase a land or uh to rebuild their houses and all damages houses and all. So the government are paying two million rupees per car lever. So the system uh it’s going on, like the selecting the car leavers and uh uh getting the information of the carelivers that everything is currently happened, and also they are supporting for the children who are living in CDC uh the with the 5,000 Sri Lankan rupees, which goes direct to the uh child’s accounts, so it will be 2,000 for child’s account and 3,000 for their uh dairy expenses and all. So these things is currently happening, and also apart from that, uh the government is trying to implement an other alternative care options uh the other than the children’s going into the institutional care.

Colby: 13:18

I hope I heard you right. But did you say that the government that the government grant of 2 million rupees is that sufficient to buy a house or is it sufficient to um put down a deposit to buy a house as such?Nimmu: 13:36

Uh for me, like uh the children who like uh for the car leavers, uh they always try to uh uh have in their own homes. They they it’s something like to me also, I also want to have a kind of a home, my own house. So the car levers are really happy on that. And uh, but the thing is that we leave that uh work properly because there are systems like there are criteria that select in the car livers, like uh age uh 18 to 30, 18 to 40 years. But the thing was that I have heard like after even after 40 years, even 40 to 45 years, they don’t have any place to stay and all. So they are asking for that. Uh why we are not getting uh support and all. So I think that the equality is really uh not happening there.

Colby: 14:27

So we had a little bit of a technical issue there, but um, I was interested in the generosity of the Sri Lankan government to to offer those grants to carelivers that effectively give them an opportunity to have a have a home. And um I just wonder, Nimu, before we move on, um what what is the what’s it like for children growing up in the development centers there in Sri Lanka?

Nimmu: 14:58

Uh it’s totally different when I was the child development centers because it was almost 20 years back, the story, like more than 15 years. So uh the situation is uh really increasing uh with a positive way, to be honest, because uh uh the things that uh things and the uh most opportunities the children are getting in child development centers are uh getting increased. Like uh when we were in there, like there were no much proper awareness, or there were not uh kind of uh uh training or something, so it was not there much properly, but now they are have they are having kind of a care plan for the children, and there is there are also uh a lot of opportunities, the fun activities, and there are a lot of uh picnics going on. So uh all the people used to get understand about the children who are living in CDCs. To be honest, that when we were there, so most of the time people used to talk about like talk about us like uh orphan girls, orphan children, and all. But the word of orphan using in Sri Lanka, some people are using, but most of the people know that they are not the orphan. So these things are also uh differently in Sri Lanka, and apart from that, the children living in CCI, everyone is attending the schools and everyone is getting support for the education system, and those who are not uh ready to take forward the formal education, most of them are getting the informal education within the center until the court uh get the decision, until the court gives the decision to go them on out of the care out of the care. So these are the things that what’s going on uh currently in the CDC.

Colby: 16:39

You said that the children don’t identify uh or aren’t identified as being orphans any longer. Um what what do you think, how do you think that change is experienced by the children? How do they experience that?

Nimmu: 16:56

Yeah, you know, like uh with the uh like uh when there are a lot of group of children, group of friends of mine that uh sometimes if they call me as uh like my children’s home’s name, not with my name, but they are calling as a child that who are grow uh with our name of our institution. So that feels called and feel really painful, but at that time it was just uh just a word, but when we grow up, we that trauma is triggering, like we feel like oh they they didn’t talk about from my name, they just talk about with my institution name. So this is something really painful thing for the children who are living in centers, and also uh the most most probably what I can see the difference is like uh the current in the current situation in Sri Lanka, the most of the uh teachers in the schools are young, so uh most of the young group they’re really close with the children, so that means they are getting uh much uh closer to the children who are living in the CCI, and there is no any uh like a discrimination between the children who are coming out from coming from the home and coming from the CDCs. So, because of this case, uh the children are living happily in the school, but in somehow there there might be, and I know that there are a little bit of um things is happening, thing incidents is going happening, uh, that still uh the children are getting that name as often, sometimes because every children in the CDCs is not um uh well uh trying to well get well education because they are some most of the children they don’t like to get uh formal education, they want to go uh go outside and they want to earn money and they want to be in the independent. So and the thing is also as I mentioned that earlier when I was there, it was actually uh the orphan children was there, like there is no one to care, no visitation, no one to see. But currently 79% of uh children they have the parents, at least a single parent, at least one mother of parents. So they want to go outside not to be in the CDCs, and they they they feel like they have the family, but then why I am in the CDC? So they are not trying to get their education, they just want to escape from CDC and work and join with the family. So the main thing I think that that’s the things, and um the taking of the positive or negative the things that whatever the people are saying to the children in CDCs, it’s depend on their mentality, like the children’s mentality. Like uh the children who are actually totally open, they understood that yeah, yeah, that’s totally fine. Whatever they say, that’s totally fine. I’m okay, I’m okay. The children who are coming out, uh come into the system currently they know that they have parents and why I’m getting I should wear as uh like a bully as orphan. So this is a generation cap pose.

Colby: 19:54

When I was listening to you, I just thought, was thinking to myself how about how strong that uh pull to that that pull is or that tie is to to family for the children growing up and and how how much, you know, regardless I guess of the circumstances that led to them coming into a children’s development centre, in their heart they want to be back with family. Yeah. And do you think um do child do the children feel safe and uh well cared for and loved in the development centers these days, would you say?

Nimmu: 20:39

This is something uh difficult question because I grew up in three child development centers. The reason for that, like in my first child development centers, I have been uh named as the radical character in the center. So, with that case, uh sometimes I got uh rude uh uh behavior from the uh matron. But I know that because we used to meet the child development, various child development centers, uh friends together when it is World Children’s Day. So once a year, all the province uh children will be coming together, and so we used to share our experiences sometimes, like how we see our CDC, because we know that if we did something, so we will be transferred to the another side development center, so we should have keep connected with them. So we used to share our experience and all. So sometimes I heard that when my when it was my eighth time that I was heard that they have beaten sometimes, they used to do so much of work and they have to do do uh sometimes they are using for their personal things and all. So they have a lot of things is going on. But when it comes to children to get to know about their rights and they they get to know about their uh protection, they should uh what what what’s their rights and all? So they used to fight it out. So it’s uh become like uh some incidence has become uh uh the the decrease a decrease in the incidence. With the bad uh bad incidents. But currently there is a proper maintenance system. So but still, I’m saying that still there are some child development centers. The children are getting um badly treated. But most pro mostly, most of the children’s homes are going well and the treated well because now they are hiring the matrons, not the matrons, the mothers. So means like the love is the main thing to change the children’s life in child CDC. So I can go, I can definitely say there’s a both the side. The negative thing is happening, positive things also happening. So it’s everywhere is that, but the thing is that how much it’s affected the children’s mind.

Colby: 22:44

I do want to ask you about that in a moment, but I just wanted to confirm it’s my ob my observation listening to you that um there has been a lot of progress in with in terms of um um the experience of of children who are cared for in the development centers even over the last 15 years since you you were there.

Nimmu: 23:09

Yeah, that’s definitely true. It’s totally has been totally different. Like they to be honest, like example, uh when I was in CCI, it was the time that I have to be appear in the court so many times, the per year, at least two to three times. Even I have to try uh go with the police officers and with the prison bus and all, but now it’s already uh change, like they are having the video recording room, so there will be only one time uh they’re asking for the evidence, and then there are officially they have a vehicle to travel, uh uh take here and there with the children. So everything has been changed. That’s really fine because I uh as a person that who grew up in there, that I definitely want to see everything is growing up, not the things that uh should have same thing happen should not happen, but I was experienced.

Colby: 23:56

What what has driven that change, Nimu? What what has kind of um been some really uh influential factors in in driving this improvement in development centers?

Nimmu: 24:12

Yeah, to be honest, like uh the ex as I mentioned that the experience, what I have gained as a negative side, I’d never wanted to give it to the other, my other generation. That I know that we are trying to do like uh decrease the number of the children’s uh child development centers in Sri Lanka or in everywhere. I think everyone used to uh everyone is thinking on that, but I’m pretty sure that it’s not going to be happening like at least there will be at least there will be uh less number of children’s homes there, definitely, because we can’t totally uh get destroyed all the uh child development centers because uh there are a lot of children who really support those who need this kind of shelter because I either we get uh negative positive parts, or there are things that the children can be get educated within the centers, so it should be those who can’t really go for the uh kinship care or the adoption or um to the foster care or anywhere, so there should be a place to stay. So I think uh what I was interested mostly uh to protect the children who come into the child development centers because I don’t want children to come in into child development centers, and I just want to strengthen family strengthening because they everything is go coming and everything is happening within the family. So if we can strengthen families so we can do the awareness in the family, if we can support the family, it can be the financial, it can be the economics, it can be the uh like uh kind of uh uh so there can be various situations, like most probably in Sri Lanka now divorce cases has been increased. So the effect on the divorce case uh going to the children. So the par both the parents are not okay to take the child on their custody, so they are going to the child development center. So I think these incidents, this kind of topic that uh influenced me to go out and talk about these things. That yeah, and uh as Asian country, you know that we are very close to the family members, like the parents and all. We culturally we are connected to each other. So the most touched part is that if we can touch the heart of the parents, that it can be uh they can be together as a family. So, what I am doing currently as in getting to that, and I’m currently doing the the things that I feel like this is the best thing that doing the awareness and talking about my stories and sharing my stories, and then asking them not to send child into the child development center. Keep as much as you can with yourself.

Colby: 26:46

Yeah. If I can summarize, um advocacy by people like yourself has has been a real driver for change. You’ve been advocating for maintaining family connection and strengthening families. The preference is not for children to go into development centres, but the reality is that there will always be children who uh need to be in a development centre. Yeah. There will always need to be development centres. So I guess the challenge is to um advocate for the best possible care while the young people are there in those development centres. There will always be children in a residential care environment, and what we need to do is one, recognize that for some children that is the best place for them to be for a period of time, and two, ensure that they have the best care possible while they’re there.

Nimmu: 27:48

That’s definitely true. I also feel like uh uh the either it’s a family, either it’s a child development center, either it’s an adoption, or any other forms of like a post-op kinship. Where is the best place for the children? Children should be there.

Colby: 28:04

Yep, absolutely. And and so the children’s placement should not be determined by what the system can manage. It it should be determined by what is what is in the best interest of the child. And we need so we need care options. The system or the out-of-home care system always needs options for children and young people. Another thing you mentioned in there was um talking about leaving care and issues around psychological support. This is something actually that I’m that is very close to my heart at the moment because I work uh primarily as a psychotherapist with children and young people, most of whom are in out-of-home care. And each year some of them turn 18 and leave care. And so that support that they had that was funded by the local child protection authorities for me to work with them comes to an end, and we have to find other avenues to maintain that support, um, which aren’t not always the same. So I think I was just wondering, you you raised it in in Sri Lanka. What would you say is the kind of cycle the psychological support or psychosocial support that is on offer to children in care? And then what what does happen to them when to that when they do transition from care?

Nimmu: 29:38

Yeah, uh, this is something really important thing because uh uh the either they are tour children in the child development centers, their psychologically, their mentally, they are totally different for each one to each other. So within this uh period of time when they are in CCI, uh CDCs, and uh they they are getting counselor support, like uh where but the thing is that is that really on time because sometimes when they get aggressive, they used to call for the counselor, and that time they will be uh that uh time uh very comfort level to her, but after that, might be in the two to three months or four four months, they come visit and again. So I don’t know uh is that the the uh uh best things to do the counseling for the children because every children is coming from the traumatic family, some because some most most of the some sometimes can be the domestic violence family and also their aggressive behavior because of that case. So it’s not should be the counseling and psychological support only for the children who are living in CDC, also for the matrons, also for the caregivers should be there. Other than like like I think like um if we only give the psychological support to the children who are living in CDCs, uh it’s not going to be work. So when it comes to the uh aftercare, like uh leaving the care of the children, so if you if they are not prepared, like the mental is not prepared uh to go out, most of the children they are not prepared. Look at like when you are in the 15 years of your age, you are celebrating your birthday very uh happy, might be very happy. But the children who are living in CDCs, when they come to 15, they are just thinking that not their birthday to where I will go after three years, where I will go after one year. So that’s the starting point of their uh mentality going down. I feel like at the age of 15, there should be psychological support, there should be mentally prepared them already to go outside. And I think it’s not wait until the 15 years of old, but the counselor or psycho psychiatric or psychological support can give before the 15 years, and they there can be start the preparation for the children to go out, so then they know that how to uh deal with the people, how to stay in their by own their own feet, and they know how to uh deal with any kind of people and everything. So I have seen some organizations in Sri Lanka kind of emerge or so. They are little kind of organizations that they are giving support, especially uh the self-defense, as to the girls, especially. Because uh you know that when we go outside in the because when we even series, the children are not getting exposed to the outside society, especially for going on the bus, going into the market, going to the bank or anything. So without knowing anything, that when they go outside, so if someone is like jagging their in the bus, they got afraid, they are not raised their voice. But if they learn how to defend on that, so it will not uh make them uh like uh uncomfortable because even that small thing also uh can be effective to their mentality. So I think before go out, these all the children, there should be proper psychiatric support, psychiatric, uh even the mentality, make especially to make their mentality uh think that yes, I am now ready, I am okay to go outside. Uh, that’s the definite thing because you know, like most of the children who are going out of the care they don’t have proper birth certificate, they don’t have proper identification, they don’t have a proper place to stay. So there are a lot of things that should be prepared and go outside, otherwise, they are going to be definitely again going to be the uh helpless children.

Colby: 33:29

Yeah, so I I guess what I’m hearing is that um one important aspect of the out-of-home care sector that could be improved is is the psychological support for the children, uh including supporting their psychological readiness to transition from the CDCs into independence. And um I thought w when you were mentioning it earlier that you said something about that that reflected that um when they leave whatever support that was offered just comes to an end or or or um uh diminishes in some way. Is that was I right in understanding that that that that it’s not only that you have to move on from home and you and you and you’re moving on from formal education perhaps, um, but you’re also moving on and you’re you’re moving on from the ha the people that you’ve been living with, but you also uh move move on from or move away from mental health supports for that that help with the preparation for independence. Is that right?

Nimmu: 34:41

Yeah, to be honest, uh for me, like uh when I got uh uh failed in my first exam, attempt of my first attempt of my examination, I was thinking that then now I have to go wherever that they are uh they are telling, but it was not happened. They are asking me to do the repeat examination and then I do did it and I get the pass. So I think the best decision that they have taken is giving me second second chance. So it was a turning point. Then I was moving to the advanced level examination and then I got this scholarship to study in India. So until this period, that I was in the same time, I was happy many times in the courts. So it was really damaging my mind, like thinking that no matter that how much I studied, that I have to be in the court, I have to repeat my cases, which I was it’s really traumatic things. So I was not mentally uh totally uh like uh recover. To be honest, when I writing my um bio autobiography, it stood more than four years to write down because it was almost all the flashback is coming to my mind. So I I I was I wanted to get the psychological support for that while I’m writing this story. So you know that how much it’s hard to remind my childhood memories when I was in um my home, my own biological family. So I think what I got uh through the people that who are surrounding me, it’s uh not 100% the car leavers, to be honest, it’s the teachers most of the time, and also the people who are really um uh supporting me uh and supporting the children who are living in CC that those supporters give me the strength to go out. So, also I think uh my strength was uh especially getting through my uh flashback incidents. Whatever the bad things happen to me, I have taken it as a positive points to go out. So I’m sharing like this my stories to each and everyone. But the thing is that every girls who have this kind of strength they can go out, but those who can’t go out, those who can’t get this strength, who will be looking after them? So it’s better to be the voice for that those kind of voiceless children. So that’s why I think that uh I’m kind of I I I feel like I’m kind of a candle to me. So I’m burning myself, but I’m supporting for others. That’s something that I feel like about myself. But that’s totally fine because uh either I am uh psychologically not uh fully recovered or mentally full not fully recovered. That uh if something’s not happened to the child, same thing happened to me, that’s really something I can be fresh and I can be happy. So it’s make me heal uh when I see someone same uh someone uh going into different ways and they can find their life. So it’s something that I feel uh I’m getting healed to myself.

Colby: 37:47

Yeah, yeah. So um that’s lovely. What I what I’m hearing is that um part of the healing process for you has been purpose, has been the the purpose that you have in your life to uh advocate for and on behalf of other young people young people in care whose voice isn’t often heard. And when you see when you see good outcomes of that uh uh of that advocacy and that support, that that really boosts your own uh well-being. You mentioned earlier that you think that um not only should the children and young people receive support, but also the people who look after them, the teachers, the the the mums in the homes and so on. Um That’s it’s interesting. We’re not because I’ve sp over the last year I’ve spoken to um people from around the world who are involved in um um the provision of residential care for children and young people. And um one of the consistent themes is the need for um for therapeutic input or for input with the people who look after the children and who interact with them uh a lot. And some of that is is about just is about support. It’s also about um support for them, but it’s also about helping them to have a better understanding of the young people in their care and of how to uh care for them uh in the in the most therapeutic way. Just wondering if that that was what you were uh kind of uh suggesting or or or representing when you when you mention support, not only for the children, but also for the adults around them.

Nimmu: 39:48

Yeah, that’s true. Like for me, like I think like uh there should be uh children who so also must be ready to take this uh uh support from outside people because most of sometimes some children they’re really afraid to open up and they’re really afraid to talk about uh with the outside people, especially. Uh, because children who are in the centers they lost their trust with their own biological family members, so they are thinking about how to uh get how to believe other people. So I think um the people who are going into the CDC and the people who are really wanting to support uh with the psychological support of the children, I think they should understand the mind of the children, and before they should study the children’s and then they can uh reach out because most of the children are not uh going to uh hear everything, whatever the psychological support are given. So sometimes they might be they’re interested in getting kind of activities and they might be getting kind of uh I think video recording or something. They they they like to have kind of it’s kind of a cartoon type. There are a lot of ways. Uh so like example, like when I was um even the 25ers, uh, my uh one of my uh working places, they have me, they they thought that I want a psychiatric support because I used to get angry all the time. So they just sent me into the psychiatric, and she was asked that uh uh I wonder that you are really young, then uh how you why you are getting angry, and also then I told that I’m the one who’s uh really want to have this justice for each and everyone. So when there is injustice, I used to get angry, so that’s a normal thing. But uh psychiatric was asking me to get the treatment like tablets, taking tablets. So that’s not the thing that for me, like within the first day they asked if they ask him for the take the tablets, that’s time also I’m getting angry. So I think it’s better to understand and uh having kind of a uh pre uh getting pre-information about the children that before they go for the logical support. That’s really important thing, I think.

Colby: 41:54

Yeah, I think what you’re uh part of what you’re also saying, and which others have mentioned it before, is that um um you don’t have to well, in fact, one of my previous guests, Megan Corcran, said you don’t have to be a therapist to uh provide a therapeutic experience for a child.

Nimmu: 42:16

Most of the yeah, because most of the children who are leaving the CDC, they they are not 100% need of the psychological support. They really need the kind kindness, attention, and the love and care.

Colby: 42:27

Yeah.

Nimmu: 42:28

If you can give these four things, they’re definitely automatically they will be mentally healed.

Colby: 42:33

Yeah, yeah. Now I know a great passion of yours is is is the careless like yourself. Um, what what is what’s the current situation? Um, you’ve mentioned uh the grants, the grants that they get to to purchase land or purchase a house and kind of set themselves up. Um what what other support uh systems and organizations are in place for carelivers now in in Sri Lanka?

Nimmu: 43:03

Yeah, for the carelivers like uh myself from 2017, we started and co-founded this care leavers network of generation never gives us. So we are as the care levers, we are supporting for the carelivers uh to finding out uh job opportunities and we are giving the psychological support through and the legal support and higher education support and everything. We are just as a group, we are supporting. So we have in the GNG network more than 500 care levers already registered. And in the same time, on 2025, I have been um started and co-founded uh another care lever’s network, which is fully focused uh with the psych uh with the um job opportunities, finding the job opportunities for the care levers. That’s the same thing, and the trusted place and the hostel facilities and everything. So we are 15 children uh care leavers who came together and built up this network. Uh, and we are on the way, we are just calling each and every companies, and we are getting their Vacancies and we are just giving to the preparation department, and we are uh placed the child into the uh job opportunities after 18 or 19. So these are the things that as a carelavers, what we are doing. So apart from that, there are a few NGOs in Sri Lanka, few CSOs in Sri Lanka that they are taking the care of the children, so like caregivers, they are giving the facilities for the carelivers to stay there until they get independent and all. So we also have a kind of a uh plan to uh build a transistent uh home. It’s kind of a home, not a hostel, transistent hostel, like uh to stay there until they get find out uh the best place to go. Uh like uh once they are started their uh career, they can pay to their place where they are, and then we can uh spend that money to another child who comes coming into this uh coming out from the system. So we am planning kind of a build up the this transition home. So there will be facilitation for all the carelivers that it’s not kind of a against, it’s kind of a home for them. They can stay there and they can go for the work, they can go for the universities to the studies and everything, and they can come back because now they can think that oh now they are I have a place to come back. So they they can come there and while they are earning, they can pay for the light bills, the water bills, and electricity, everything they can pay by their safe, and in the same time, we are hoping to give the uh them IT knowledge and the uh reading skill and life skill and the yoga therapy. This everything we are just having kind of in our mind, and now we are having also so the proposals, these items, and we are making the proposal and we are trying to get with the funds, and then we will start this process also for the car levers. It’s for the car leavers from care levers. So, this is also something what we are doing. So, apart from that, yes, the government is now focusing on that the care levers support for the car leavers, especially. Uh, the uh they are going to address the about the documentation issues because most of the car levers they have probable age certificate other than national birth certificate. So, probable age certificate is there is a lot of blank, they don’t have any birthday, they have only the birth year, so which really affect the mentality of the child in in uh after the leave. Also, most of the care leavers they don’t have identity, like they don’t have vote to the uh like in the elections because uh they don’t have proper ID in the their identity car where they have put in address, they don’t have home to put in address. So these issues are also going to be addressed soon within the government system. Now there is a discussion is ongoing. So I’m happy as a care leavers in Sri Lanka, we are really strong and we are used to government level, we are used to in the uh like a private sectors in GOS and INGO. So we are dealing with all of them. Uh so we we expect that the children who are coming out of the system in recently in the after after 2010, yeah, uh I came as of 2010. So I think after 2010, when 2017, as we uh started this advocacy, I think it has changed a lot, and uh there are a lot to change, and also I feel like for most of the care levers uh really happy to support for each car leavers, each other leavers, not the national level, so international level also we are raised this sub-advocacy work, and we are getting support from the people and we seek continuous support because uh there are a lot of children who uh lost their education, higher education without the financial support. So, as a car lever, by myself, I used to have find uh so many donors and all, and I just give this uh child information, and they used to get uh appoint in the schools and uh sorry, education in the universities. So there are there are a lot of children who get support from me. It’s not actually my money because I’m not a kind of a person who rich with money, but I personally believe that I can support them with other people’s uh around me. So there are a lot of children who are studying in the university with our support. So I’m proud of that of that, and also I’m proud that as a careliver, so now there are a lot of carelivers come out and they are speaking about their rights and whatever they want. So it started with actually myself that I have been speaking about my whole story, so with through my autobiography and also through social media and the TV channels and everything. So people get to know about most of the people they don’t know that the children who are living in CDC should leave after 18 years. So the question what I was asking the uh uh interviewer, I was used to asked that either you ever ask your child to go out when they turn out 18. If not, why the children who are living in CDC should go out. I because they even they don’t have anyone to care. So if they go out, also there should be continuous support at least until they stand by their own feet. Because the children are uh like everyone is thinking that children are the future of their country. So it’s they should be careful about that. I think it’s happening now, and I think that there should be more more because we we always think that more is more we need, no. So I think uh it should be happened more and more, and I believe that the children who are coming out of the system, the problems that we what we have faced, it will be not happened to them very soon.

Colby: 49:28

That’s inspirational. And um as you were talking, I was just I was thinking about carelivers even here in my own local jurisdiction, and um um I do have some plans. I’m going to re um I’m not talking about them until uh after I’m a little bit further along, but um let’s just say I I’m similarly concerned in my own jurisdiction about certain aspects of of the ongoing care and support that that get lost when they turn 18. And as you as you say, we wouldn’t we don’t normally expect children to be independent, whether they’re in a Western country or an Asian country uh like there in Sri Lanka. We we we don’t expect our children to be out standing on their own two feet independently at 18, and especially when they when when they’ve had troubles in their life um uh as as they’ve grown up. So I tell you what, it sounds fantastic and uh like you’ve achieved a lot. And I guess there would be listeners to this podcast who would be thinking, if only we could get namali to come and advocate in our country, or or if only we could bottle what what she bottle up what she’s been able to uh achieve and uh and kind of have that here in in our country. So um there are examples around the world where carelaver support is really good, but there’s a lot of examples where it’s it’s not in so-called first world countries.

Nimmu: 51:12

Yeah, no, I I mean like that’s true because I used to meet um so many countries, care leavers, and we I we used to have a chat and we used to have kind of a cafe and we used to have a discussion about what’s ongoing in their country, what’s going on our country, so it’s can’t be Western or European or in the Asian. So we are coming together. So it’s really something like um I feel like the most of the care leavers in the all of the country, all of the like globally, now they are getting really strength to come out and talk about. I think the attitude is getting uh really positive because the change in the mind of the peoples, the attitude of the people is a really difficult thing, you know, every country is so. But I think that uh when coming not coming as a one person, it’s coming as a group, it’s really a lot of effect. So I think that as a global Kalivers, I I’m one of a member of the Global Calibur’s Committee and National Kalivers Committee. So we always talking about these issues and we are taking all uh this into the advocacy world. And now I feel like the topic is Kalivers is going uh beyond than other topics. So it’s really something really great thing because uh now people know that what system is happening, what’s not happening, and what should be done. But it’s really something really great that we care came out.

Colby: 52:28

Yeah. And and what what is happening is that um the voice of children who previously, children and young people who previously didn’t have a voice, is being heard. And it really takes um it takes people like you. I think you described yourself um as some something of a disruptor as you were growing up in in the home that you were in. Uh it takes someone like you, I think, who’s got a bit of a bit of drive and a bit of strength and even a bit of and and passion for fairness, for for the rights of of young people um who uses their voice to to um create change and be a change maker.

Nimmu: 53:13

So what’s definitely true?

Colby: 53:15

Yeah, yeah.

Nimmu: 53:16

I also just want to those people who really wanted to see about the what the system is doing and what’s really happened and what’s ongoing and how I became kind of an advocate, uh, they can definitely read my book, whatever I can fit in Amazon also, so people can read it out, and then they can really understand more and more that because uh there are a lot of things that what I didn’t speak out, but everything is in my book.

Colby: 53:41

Yeah, yeah, yeah. All right, and that was a deliberate plan for me. I I don’t I I didn’t want you to relive your your whole history here uh on the podcast, but yeah. Thanks. Thank you again, Nimu, for for coming on, and uh I look forward to hearing more uh in the years ahead about the accomplishments that you um that you have and and that your networks have in this in this space.

Nimmu: 54:11

Thank you so much for inviting me. So, because uh at last I want to say that um people like you that’s taking this kind of topic in out that’s really make different for without you knowing that you are making the so much of uh positive impact for the children who are leaving the child development centers. Because uh, if at least one single person who listened to you are one, so they will understand that what’s really going on. So that’s the things that we don’t want like a thousand or two thousand people to get involved, but at least a single person to get uh involved and move forward, that’s really important thing for us. So, thank you for taking us and thank you for giving that much honors for the car leavers uh to invite for your broadcast. It’s really mean to us, and I will be the only uh one person who is there today, but there are a lot of care leavers who stand there by their own feet and living very happily their life. So I I bit uh so I wish that all the car leavers will be definitely uh get healed from their traumatic life, and they will be definitely be happy and talk uh in front of Mike or in front of uh everyone is not should not talk in front of my by Mike, but within their life, they will be definitely happy with the people’s support like you. Thank you so much for inviting this podcast.

Colby: 55:33

Thank you.

More about Nimmu:

Affectionately known as Nimmu, Nimali is a care leaver from Sri Lanka who spent over a decade in institutional care. She holds a degree in Journalism, Advertising, and Mass Communication from NIILM University in India, along with additional qualifications in criminal investigation, psychology, and social sciences. She has worked as a still photographer and costume designer for the Indian film DREAMZ in 2013.

Nimali has represented Sri Lanka as a speaker at numerous international conferences, including  those focused on child protection and women’s rights in Nepal (2017), and the BICON International Conference in India in 2018 and 2021, in Nepal in 2023, and Malaysia in 2025. Recently, Nimali spoke at the 35th FICE International Conference in Croatia (2024).

In 2024, Nimali was honoured as a Young Change-Maker by the UN Ambassador and Neon Media. She is an active member of the Global Care Leavers Committee and member of the Care Leaders Council. She represented South Asian care leavers in the UN Resolution Focused Group (2019). She completed the Justice-Based Approach Foundation Course at United Edge, USA (2021).

Since 2021, Nimali has appeared on various TV programs discussing her life experiences and has become a social media influencer. Drawing from her lived experiences, she is a passionate advocate for children’s rights and alternative care. 

Nimali’s work focuses on reuniting orphaned children with their families and ensuring they have access to education and employment opportunities. She worked for one of the largest NGOs, Sarvodaya, for 10 years and later for the Egyptian Embassy. Currently, she is employed at Their Future Today in both the UK and Sri Lanka, is registered as an Alternative family and foster care manager, and leads the foster care program, ensuring that children grow up in safe, loving families.

Inspired by her own 15 years in orphanages, Nimali co-founded the Asian First Care Leavers 

Network, Generation Never Give Up, in 2017. She also cofounded and currently works as Director of Rise Together Care Leavers leading network. 

Nimali recently launched her autobiography ‘The Caged Girl: A Journey To justice’’ & 

‘’Dumburu Pathok ‘’ in Sinhala.

Related Podcasts:

If enjoyed this podcast episode with Nimmu, you may also be interested in the following:

Surja:

Listen here:

Watch here:

Dr Hayley Lugassy:

Listen here:

Watch here:

Links:

Patreon: https://www.patreon.com/c/TheSecureStartPodcast

Podcast Blog Site: https://thesecurestartpodcast.com/
Secure Start Site: https://securestart.com.au/

Disclaimer:

Information reported by guests of this podcast is assumed to be accurate as stated. Podcast owner Colby Pearce is not responsible for any error of facts presented by podcast guests. In addition, unless otherwise specified, opinions expressed by guests of this podcast may not reflect those of the podcast owner, Colby Pearce. Finally, all references to case examples are anonymised to the extent that the actual case could not be identified, or are fictional but based on real-life examples for illustrative purposes.


Building Trauma-Responsive Care – A podcast interview with Richard Cross

What if “care for the carers” is the real key to healing children? Richard Cross unpacks attachment, containment, and why residential care isn’t always a last resort.

Why caring for carers is the first step to healing children

The conversation with Richard Cross traces a clear through-line from first principles of attachment to the practical, daily realities of caring for children who have lived through repeated adversity. The central idea is disarmingly simple: care for the carers as deliberately as you intend to care for the children. When organisations build genuine containment for staff—through reflective supervision, stable leadership, and shared language—adults think more clearly, tolerate uncertainty longer, and respond more humanely. This is not abstract. It shows up in fewer reactive decisions, more patient attunement, and a culture where difficult feelings are metabolised rather than acted out. Richard’s pathway is parallel by design: a staff pathway that mirrors what we want adults to offer children—holding, reflection, and growth—so that therapeutic care becomes a living experience rather than a manualised aspiration.

This lens also reframes how we choose care environments. There’s a prevalent belief that family is always best, and that residential care is an option of last resort. Richard challenges this. For some children—especially those phobic of family life due to traumatic family histories—early, high-quality residential care is the right first option. It offers increased containment, predictable routines, consistent relational responses, and an integrated team that can share the emotional load without burning out a single carer. Used early and well, residential care is not a cul-de-sac. It can be a structured bridge that shortens the overall care journey, stabilises education, restores trust, and improves placement matching into foster care when the child is ready. The cost argument fades when we look beyond a single year and count the human and financial toll of repeated breakdowns.

Translating theory into practice depends on leadership. Trauma-informed care is not a leaflet or a one-off training day; it is a culture choice repeated under stress. Richard starts with directors and senior managers, setting an honest expectation of a long journey. Leaders must protect time for reflection, model transparent communication, and respond to crises without abandoning the principles that keep the system humane. Shared language is the glue—terms like containment, emotional holding, thinking-not-acting, and amber flag meetings give teams a way to notice patterns, signal risk, and convene quickly to think together. Staff need spaces to explore triggers, write safety plans for themselves, and acknowledge that not knowing is often the wisest starting point. Tolerating uncertainty creates room for curiosity about what a child’s behaviour is communicating, rather than rushing into control strategies that escalate distress.

Integration across services magnifies healing. When residential homes, foster services, schools, and clinical teams all use the same concepts and responses, children experience adults as consistent and coordinated. Anxiety drops when staff don’t contradict each other, and when ideas flow freely across settings. Practical structures make this real: cross-service supervision, shared formulations, and “amber flag” meetings anyone can call when pressure rises. These routines stop fragmentation before it sets in and keep the system relational. The message to commissioners is equally clear: bring psychologists into placement planning, invest earlier rather than later, and track outcomes credibly so trust grows. Evidence from practice shows that the right residential intervention can reduce total time in high-intensity care, improve education continuity, and increase the success of subsequent family placements.

Mentorship underpins all of it. Richard’s story threads through good governors, supervisors, and collaborators—people who stood at his shoulder while he learned to hold complexity without panic. That’s the same stance we need for staff stepping into tough roles, and for children learning that adults can be steady, honest, and kind. The north star remains attachment: safety, proximity, and reliable responses that let minds turn back on. When organisations embody that for staff, staff can embody it for children. That is how cultures change, how placement breakdowns slow, and how healing becomes less about slogans and more about daily practice that holds firm when it matters most.

Listen here:

Watch here:


About Richard:

Richard is a UK Registered Psychotherapist and Child Psychotherapist.

His career for over 30 years has focused on working with relational approaches in areas associated with attachment, trauma and dissociation.

Richard’s early career was focused on developing relationally based treatments within correctional environments to reduce recidivism, as well as managing democratic prison-based Therapeutic Communities for high-risk adult life-sentenced offenders (HMP Dovegate, England).

Richard collaborated with Sandra Bloom to introduce the Sanctuary Model to the UK in 2004.

Since then, Richard has developed an interest in trauma-responsive models and continued his focus on Therapeutic Communities, exploring how to bring these aspects to life in organisational cultures. One example is a multi-component approach called ATIC (Attachment and Trauma-Informed Care), which is now harnessed across multiple residential child care homes. 

Richard is actively involved in research and innovation, and he also provides consultancy services to organisations, and training to qualified mental health professionals. 

Richard is Director of Clinical Services at Five Rivers Child Care & Midhurst Children’s Therapeutic Services, where he leads teams of psychologists and psychotherapists. He is also a Fellow and Faculty member of the International Society for Trauma and Dissociation, and serves as a trustee of the Bowlby Centre in London and The Consortium of Therapeutic Communities (TCTC).


Related Podcasts:

If you liked the conversation with Richard, you may also like:

My Interview with Patricia Sheridan of Moore House:

You may also like my conversation with Dr Kevin Gallagher:


Transcript:

Colby: 0:00

Welcome to the Secure Start Podcast.

Richard: 0:03

There’s something about having a really good mentor, having a good individual who can create the space for you to think, grow, and develop and wrestle with some of these tensions and unknown elements that can often come around in the world. It’d be great if you could put an old head on your own shoulders, but the reality is that that can never be the case. So we need to go through this. Through this process of learning. It’s that experience that we have someone there that’s going to stand by us through that process of learning, through that process of growth. It’s so reassuring, and we don’t want to care for the staff equally as much as we do the children. We often see the graduates of within the home having other children in mind. I speak to leadership and management, but what’s that going to mean in terms of the leadership style in the organisation and the culture that’s going to permit staff to be able to move to a place where we can truly use the structures and attachment to twelve and form. And we start to think, to learn, to grow, to develop. But if people think twelve and four care to be responsive is easy. It’s not. To be able to deliver this and to be able to do it, so it’s created as a living experience for the staff and a direct experience for the children. It takes a lot of courage and bravery because people need to go and think about hearings and would not really think of it. Foster care can be highly effective for those children who have anaphobic about family living. You know, the great thing at the moment is that five of us is changed caring for over a thousand children, and then the much of it those children are in foster care. Very happy, really good outcomes, you know, great foster parents, you know, doing great work. But there is a group of children and young people that are still the BO them to identify when residential the residential environment is the environment that’s best for them.

Colby: 2:25

Welcome to the Secure Start Podcast. I’m Colby Pearce, and joining me for this episode is a leader in therapeutic and social care in the UK who has a particular focus these days on supporting those whose therapeutic task is to support children in need. Before I introduce my guest, I’d just like to acknowledge the traditional custodians of the lands that I come to you from, the Ghana people of the Adelaide Plains, and acknowledge the continuing connection the living Ghana people feel to land, waters, culture, and community. I’d also like to pay my respects to their elders, past, present, and emerging. My guest this episode is Richard Cross. Richard is a UK registered psychotherapist and child psychotherapist. His career for over 30 years has focused on working with relational approaches in areas associated with attachment, trauma, and dissociation. Richard’s early career was focused on developing relationally based treatments within correctional environments to reduce recidivism, as well as managing democratic prison-based therapeutic communities for high-risk adult life sentenced offenders. Richard collaborated with Sandra Bloom to introduce the Sanctuary Model in the UK in 2004. Since then, Richard has developed an interest in trauma-responsive models and continued his focus on therapeutic communities, exploring how to bring these aspects to life in organisational cultures. One example is a multi-component approach called Attic, Attachment and Trauma Informed Care, which is now harnessed across multiple residential childcare homes. Richard is actively involved in research and innovation, and he also provides consultancy services to organisations and training to qualified mental health professionals. Richard is Director of Clinical Services at Five Rivers Childcare and Midhurst Children’s Therapeutic Services, where he leads teams of psychologists and psychotherapists. He is also a fellow and faculty member of the International Society for Trauma and Dissociation and serves as a trustee of the Balby Centre in London and the Consortium of Therapeutic Communities. Welcome, Richard.

Richard: 5:18

Thank you. Thank you so much, Colby, for that very warm welcome. And it’s really good to be here.

Colby: 5:24

Yeah, and look, it’s lovely to have you and thank goodness for the technology. Otherwise, uh be coming from a different uh well, I’m in the future for you, um, because I’m later in the same day. Um, and and also this technology uh allows me to sound very professional in the opening, even uh if you had to sit through a couple of uh blooper worthy moments there. Now, Richard, is there anything um that you’d like to add to that um that short bio I just uh gave of you?

Richard: 6:01

No, naturally, that’s that was that was very kind for you to share about a little bit about my developmental work history there. Uh but naturally it can’t cover off uh everybody that’s been really supportive of the thinking and innovation that I’ve had the privilege to do because often it takes organizations and systems a leap of faith to consider doing something something new or innovative.

Colby: 6:32

So yeah. Yeah, well, I I want to I do want to um talk to you as we go through about um about individuals, organizations that that that have um uh been influential, I guess, in in uh your career to this point. But I guess I’m wondering in the first instance, maybe if you can tell us a little bit about how you got into this um this space, this space. Uh you might even uh have some other words to describe the space you occupy uh in your work.

Richard: 7:11

Yeah, it’s fascinating when we end up at a destination. We often think about how did we get here, and I think for many people that getting gets involved in thinking about how to supporting children and young people, often there’s a real benefit to think about port supports being our motivators uh to engage in the task, and I’ll sometimes even help the care staff and the people that I support to really think about joining the dots around us. Uh personally uh yeah, you know, I had uh I think one of the driving forces was thinking about the key significant peoples in my early development that supported me through what wasn’t uh uh a particularly easy time coming into the world and uh starting starting off in life, and those experiences really stuck with me. So when I uh left the military in uh 1991, I left the services uh the Navy. I thought, what is it I’m gonna do? And for some unconscious reason, I I ended up working in young offenders. That was my first sort of task. That started off as a prison officer. Uh but very quickly within I think it was six months, I had this really supportive governor, uh, somebody called Dan Gunn, who uh MBE who uh supported me to go on my journey to become first qualified in psychology, but then start up my route to become a psychotherapist over the over the preceding 12 years and get some, you know, and then I got involved in the programs and the like. But yeah, so yeah, there’s there’s uh I often reflect on how I ended up, but there was something that was driving me to think about understanding the needs of children and young people. Uh even back then, it was thinking, thinking be sort of beyond what the label was back then, back in the 91 when I first joined the young offenders. It was all about the young person who committed a certain offense, which which is important. But quite early on, I was thinking, what is it that we need to do to think about what happened to this young person? What was the drivers, what was the antecedents for them to end up in their journey to end up in the young offenders? So yeah, that was that’s a little bit about my early embryonic sort of foray into the work.

Colby: 10:10

Aye, aye. And um uh was is there through your um uh your career since then, you’ve you you hinted at before that there’s been individuals and organizations, I guess, that have been willing to give give things a go or give give your ideas and innovations a go. I’m really excited to have you on because um I said the magic word when I in your bio, uh, which was bulby. And uh I think I think early on in each podcast, I I tend to ask people um about what theoretical orientations um uh influence their work. And I’ve been waiting for someone who who to uh who obviously um has drawn on attachment theory um probably similarly, uh if not uh more than I have done in my own career.

Richard: 11:08

Yeah, John John Bowlby and the subsequent pioneers. Uh because often thinking has its origins, and hopefully then there’s there’s others that can come after and pick up the bat and uh and carry on these these areas of development and thinking, and just as John Bowby’s uh theory is and uh and all uh and also pioneers about the social mind as well. Uh Colin Trif Island, for instance, uh there’s there’s been so many pioneers who who who create idea. Uh so John Balby was a very significant influence in my early war. That’s in part that was why I chose to go and they support places like the Balby Centre in London, but also thinking about how that relational aspect about how it can be applied not only to the practitioners themselves, thinking about their relational aspects in the work and the therapeutic task, but also thinking about the tasks with the child or the young person. Yeah, it’s very important, and I think the whole notion that John Bowlby brought, and I can remember watching his very last interview that was filmed, he uh he often said he had a regret about not incorporating as much as he wanted around the whole notion of trauma. He did move the theory away from the fan this notion of fantasy into the reality, but he had this element uh in his last interview with Peter was saying that there’s so much we need to do in terms of hearing what the children are bringing to us and and understanding that context in the relation of adversity. Uh so yeah, John Bowlby is a very influential person, but so so has been the people that I’ve had the privilege to work with. Uh so I can remember back in uh 2003 I was presenting at a conference in Scotland, uh, and at that time it was presenting on attachment, it was called broken bonds. Uh and in the audience was somebody called Sandra Bloom. And I’m fascinated when we’re passed cross, just like we’ll pass across in today, Colby. Uh when I pass cross with like-minded people, it can often create an energy to think about how we can collaborate and work together. So that was a significant experience for me because I was speaking about things like essays, the importance of the therapeutic relationship within residential childcare. And some of these concepts back then, because that was before trauma informed ideas were in the UK in a big way, it seems to just have become massive like overnight. But in the audience was Sandra who had uh developed this model, and it was great to be able to collaborate with her uh and and and bring that to the UK, which was great.

Colby: 14:32

And that was the sanctuary model.

Richard: 14:34

That was a sanctuary model, and I suppose at that moment, 2004, that had been after I’d my path had crossed with with uh someone called Roland Woodward who uh developed a democratic prison-based TC called HMP Dovegate, and he gave me the opportunity of being the therapy manager for a 40 40-bed therapeutic community. And I wish I could bottle experiences sometime to to give people an experience because to be able to work and manage a team in a therapeutic community for a period of time uh and embody principles like containment and management of anxiety and start to understand how these ways of working can be really effective in turning people’s lives around. Uh it would be because sometimes I feel it’s really hard for people to understand how cultures need to be in a live and breathing way, unless they’ve experienced it. You know, I used to say have faith in the process, uh but that can be difficult if you you haven’t experienced what a process is. And uh I’m going to say thank you for like to roll in because he was there’s something about having a really good mentor, having a good individual who can uh create the space for you to think grow and develop and wrestle with some of these uh these tensions and unknown elements that can often come around in the work. Uh yeah, there’s so many people I could actually say thank you to, you know. There’s I’m sure everybody is that what’s in this field, you know. We’ve like we’ve often had somebody, I’m gonna say something about Bulby here. Uh we’ve often had somebody that’s been at our shoulder that can help and support us in our work, particularly in the early, you know, the early foundational stages of our growth into either being clinicians or therapeutic residential practitioners. We’ve often had somebody at our shoulder that’s that’s embodied that confidence to then go through the professional maturation process, as I call it, to get to a point we can feel more comfortable in the task.

Colby: 17:03

I’ve I’ve I’ve kind of referred to it when previous guests have brought it up as the importance of had people who have confidence in us until we have confidence in ourselves.

Richard: 17:16

That’s that’s such a nice way of putting that, you know, that whole notion that uh and I think this is what children and young people need, you know, this this intentionality that we believe in someone, it’s it’s uh it’s often the unspoken though. It’s like it’s that experience that we have someone there that is going to stand by us through that process of learning, through that process of growth. Uh it’s so reassuring, and and it can automatically reduce anxiety because often that is that’s the critical element that I feel that I’m day-to-day. It’s like it’s my day-to-day task almost of being the being the processor of anxiety from like for staff, creating spaces where they can sit and gain their confidence and tolerate uncertainty and uh yeah, develop that understanding. That’s a nice, very nice way to put it, Colby.

Colby: 18:17

Yeah, well, thank you. I I I had these moments every now and then, but um I I’d forgotten about it until you were talking just then. But um uh you I mean, you’re obvious you were also talking about containment when you were talking about holding on to and and processing other people’s anxiety. So I I sense that containment theory and perhaps the work of Beyond has also uh been of some um well thank you.

Richard: 18:46

Yeah, I’ve I was I was so lucky I had a supervisor for a long time called Bob Hinchelwood. Uh he’s a professor and he’s a psychoanalyst, and uh often that transfer of knowledge and wisdom. I used to have like my first supervisor used to say uh it’d be great if you could put an old head on young shoulders, but the reality is that that can never be the case. So we need to go through this through this process of learning. So yeah, Wilfred Beyond, he was uh when I got involved in therapeutic community work, I used to prolifically read the texts about the origins of TCs, you know, Northfield experiments, you know, thinking about how Beyond, Tom Main, uh Maxwell Jones. I I really like his ideas of the social, the social environment as well. Uh there’s all these active ingredients and knowledge that people have people have identified and brought that we can think about bringing to life, and there’s often interconnections as we know, so so Beyond’s work on containment is really connected as well to Donald Winnicott and that notion of emotional holding, as Winnicott called it. And Winnicott naturally worked with Barber Docker Drysdale. So sometimes when we look, you know how we’re talking about people’s past crossing. Often, often there is the crossing and history of uh how knowledge is then translated from one to another. So, yeah, containment, emotional holding, thinking about how we can use the day-to-day environment effectively for the therapeutic task and all that’s been the foundation of my work, yeah, for many years.

Colby: 20:43

And what one of the things that I often say about Balby is that he was not insular or siloed in it, you know, in the way that so many can be. Um you know, in his time and and and more recently, he was drawing on work from other areas of endeavour and integrating it into attachment theory. So attachment theory is an integration in a way of multiple areas of endeavour. Um and I just go off like I’m sorry. No, no, you say, you go ahead.

Richard: 21:20

No, it’s interesting because if you ever, you know, if I don’t know if you’ve ever been to the Taverstock clinic where Bowby was based, uh in London, it’s a you know, it’s it’s still a center of psychoanalytical thinking. But but even back when Bowlby arrived, and often often a new theory when it emerges, it’s there’s often a there’s often a rejection, there’s often a pushback. And I find this is a fascinating dynamic, particularly in work around children, because often children we can be very clear about their histories and why they’re having to get the supports they’re needing, but often just like theories are often struggle with. I think in general, this notion about attachment theory, thinking about how we handle that. There can be a bit of a bit of a wrestle for professional organizations and systems to you know to truly embrace it, to truly understand it and how to translate it in actual direct practice. Uh there’s there’s there’s often a real challenge about walking the talk, as I call it, in the field. And this is natural and normal in terms of human beings, it can be hard to do what we say we’d like to do. Uh so that’s why systems really need to develop approaches that they can tolerate almost the checking out. Are we sticking to where we want to be? Are we you know we’re staying in staying in this position of therapeutic mindedness and relational-based practice, particularly when the stress comes on the system.

Colby: 23:02

Yes.

Richard: 23:12

And sometimes Bowby, I think, had a really difficult time of it. He didn’t think you know, the very you know, the very early stages. Now it’s like one of the widest embraced uh frameworks that’s in the world. But back in the early thing, yeah. Yeah, yeah.

Colby: 23:33

There’s a there’s a lot in there. One of the things that you mentioned it was about it can be difficult to walk the walk sometimes. Yeah, I think I think theories are good if they have good explanatory power and and and they’re easily understood, digested, and and I think you know, for me, from when I first got involved in child protection work, attachment theory and 30 years ago, attachment theory gave me the best way of um helping me with with um understanding the work that I was doing. Just going back to um I liked your your your idea of having a mentor that you know someone that just is there at your shoulder, guiding you in a way, and and I talked about them having having someone that has confidence in you until you have confidence in yourself. And you mentioned too that that that’s essentially something that we we do for the children that we work with. Um and um and I you know I’ve talked about this with previous guests, but I we talk about you know, we want I think a really important aspect of the work is to ensure that the adults have it have this have an experience of being held in mind, an experience of of being looked out for and looked after in a way that we want them to in turn transmit to the child or or to be to be doing with the children it themselves.

Richard: 25:13

Yeah, and that’s that’s that’s that’s part of the model and the thinking that I’ve actually embodied within attachment and trauma-informed care. Because I thought about how to distill quite complex ideas into uh a model which can be easily embraced and understood. And what I created was two parallel pathways, uh one for the staff and one for the children and young people. And basically the parallel pathway is saying we are going to care for the staff equally as much as we do the children because they are the therapeutic agents of change, and it’s like what does what does an adult adult practitioner need in terms of that mentoring, that support, that guidance, supervision? So, yeah, I work through these parallel models, which fascinatingly it then starts to give the practitioners or the carers or the staff the knowledge and the experience to more directly to be able to do this with the children and young people, because not everybody arrives at the therapeutic task having the knowledge, experience, attunement, and the abilities to do the work with the children. So we we really put as much nourishment as we possibly can into the care staff because so my role really and my my clinical services teams are to care for the carers, to do that that you’re describing very eloquently, Kobe, about giving that that that sense of uh togetherness, uh and it’s fascinating because we even see this happening between the children and young people. We we often see group like the graduates of uh within the home having having other children in mind, starting you know, helping and supporting them. So it’s I see the system as everybody, I see the system as the staff, the children, young people, and also the relationships with the two children themselves, and about how they can start to support and think about each other and help each other.

Colby: 27:37

Yeah, you you’re I think the point to make is that if you want to create a healing system, you need to be supporting your staff very well in a in a way that is analogous or closely aligned with, I should say, with with what how you want the staff to um care for the children. And I think you know, when I think about who comes to the work, um and previous guests referred to the the kind of wounded healer, or you know, you all you’ll often you’ll often get people who come to the work who um haven’t had the the best of upbringings themselves. Yeah, and so they don’t they’re not necessarily they they probably come with an idea of what they don’t want to repeat, they don’t want the children to repeat. And it repeat they want to relieve suffering, they don’t want other children to to experience and go through what they’ve gone through. What they maybe um benefit from is is is a form of um reparenting in terms of setting that re resetting the parenting model for them, yeah. And a containing mentor, supervisor, I guess is it it’s an important part of that relationship.

Richard: 29:05

Yeah, and that supervisor relationship needs to needs to create the environment, the you know, the weather system almost about how that uh professional development can take place. Uh because there is there is a process that often goes through for new staff coming into the field, and I used to find this uh even within the prison-based T sort of TC environment, that the first stage is people arrive believing they’re going to be this omni-important saviour for the children and do this sort of change over like married days, you know. They’re gonna be able in some way make uh significant changes quickly, but then often it’s the repeated relational attunement. Attachment over quite a period of time, and that takes sometimes the need to be really resilient and to be aware of our own biologies and responses, and really understand ourselves and our triggers. And that supervisory relationship can hopefully create an environment where staff can have their own uh well-being and safety plans, so they really start to understand themselves, understand their own responses when the therapeutic task gets difficult. Have a space that they can go and talk about how they feel emotionally before this anything gets acted on. So that uh I really like Tom Main’s notion of thinking non-action, being able to create an ability where practitioners can think but not act. Uh naturally, that’s what we want to support the children with as well, to get to a place where they can think and then you know, through this thinking stuff and not have to act through behaviors. But staff need to learn that, staff need to be able to be in the presence of a child and create a space between them and the child that they can do this thinking and understanding so they can do the attachment work, like we know they can, you know, they know what how they can be in their best of selves uh and respond to children.

Colby: 31:29

Yeah, and and of course, containment the idea behind containment theory and what Beyond wrote about that was essentially um we support another person and in doing in doing so we facilitate their capacity to think.

Richard: 31:45

Yeah.

Colby: 31:46

And I think and I think staff staff who are thought of are better equipped to think of others. If you yeah, when you encourage reflection on your own motivations, the reason why you do things, the reason why you you reacted in that way, your blind spots, when when you’re encouraged and supported to do that, then I guess in turn you don’t just jump to the immediate conclusion that children are bad because they’re doing behavior that is not um agreeable, and uh and they should and they need to be disciplined in some way. You there’s a there’s a cart and a horse thing going on here, and I I myself have been across my career guilty of putting the cart before the horse. If the whole if the cart is teaching this is teaching the adults, this is how you um you need to be relate therapeutically or care therapeutically for the children. If that’s your first step, your first move, then I’ve been as guilty of it as probably you know great many people have. But as I’ve gotten older, and you talked about putting an old head on young shoulders. I am hoping the podcast by interviewing very experienced people does help uh new practitioners in the area a bit, accelerate the growth, so to speak. But yeah, you know, the first step needs in in therapeutic endeavor, it’s become much more clear to me over time, needs to be to um needs to be our endeavours to support the staff and contain the staff and facilitate their own reflective capacity.

Richard: 33:33

Yeah. Yeah, there’s there’s someone that sadly passed away recently called Philip, Philip Bromberg, who’s a psychoanalyst, and he’s written written prolifically about working with complex trauma and dissociation. And yeah, his notion is about always being aware to hold us hold a space between you and the other. That like beyond beyond stuff was about being able to create this metabolic, this this said sort of digestion of another’s person’s uh transference or affect or whatever notion we want to consider. But without creating a space to think, hopefully, all structures out there trying to do the therapeutic task, uh hopefully they have a place where it can be protected to do to do that work, as a group, but also individually in supervision. Uh because without that, people can start to get a bit lost in the task.

Colby: 34:40

Well, I think yeah, my view is that they become procedural and and heartless in the sense that there’s you know, the heart is lost from the work because it’s just a cognitive, it’s not even a cognitive exercise, it’s it’s a reflexive approach, you know. Um, there’s not not that thinking. I I am very concerned about child protection systems, like statutory child protection systems, where workers from you know supervisors down to the to to workers um at the coal face are just you know so much under the pump that they don’t have that opportunity to stop and think about the work that they’re doing.

Richard: 35:24

It becomes a paradoxical situation around the whole things around the social care system, is that everybody like I come from the position that everybody are good entities wanting to do the good task, but often the systems be can can become unconsciously uh distracted due to the some of this parallel shift in us, but some of the anxieties, some of the trauma-related challenges, and actually these systems are working with extreme distress, extreme challenges that can often create reactivity in the systems, but like uncannily that we know what can help and sometimes it’s around holding the boundary around the systems and the processes that we know that work because they’re often the things that go out the window of us, sadly. Uh so it’s like trying to know that people are good people, but be able to find ways that we can raise it in the consciousness about what’s happening because people find it really easy to deal with the rational about uh objectives and well, we’re doing great, and but when things become irrational and they become really difficult, there’s a rule, there’s a real challenge for people to consider that, to think about it, and to really tap into what the reality might be going on, so then solutions can be identified. Thought you know, thought like this, thought through relational-based solutions for people, but also families and children.

Colby: 37:09

It’s it’s such an interesting area. I and I wonder about your experience of introducing um maybe new staff or or new organizations, your experience your experience of trying to introduce um this this thing that we’re talking about, where what we how we want the staff to interact with the children, we’ve we’ve got to offer that as an experience for the staff in their in supervision, in mentoring, in yeah, how how does how does that how does that go down, so to speak, when when you try that?

Richard: 37:52

Attachment and trauma-informed care. So it’s a model now that’s uh you know it’s been in five five rivers childcare for a long period of time, but it’s also going into all the organizations outside the five rivers now. And the first thing I’ve the first thing I say to organizations and the leadership, so start the leadership, even right up at the the point of the directors of the organization, because uh I’ll say this is a journey, it’s not uh I’m gonna arrive today and we’re gonna do this intervention and it’s gonna be in place tomorrow. I’m gonna hand out these leaflets, I’m gonna I’m gonna do a bit of training, and then all of a sudden, the whole organization is going to be trauma involved. Uh so I start off with a realistic base about the journey, about how that’s going to be, what it’s going to feel like. That’s a notion I’ve taken from my work uh as a psychotherapist with traumatised clients. So, like clients will come into me and they’re often like, What’s this going to be like, Richard? And I give a sense about what the journey is going to be like. And it’s like we’ll give a sense about what we need to achieve first. And so, in terms of trauma-informed practice, it’s safety, stabilization, all these notions. But it’s the same for organizations, we go back to we go back to the sort of foundational ways, and this is where the A in attachment and trauma-informed care comes in. I speak to leadership and management about what’s that going to mean in terms of the leadership style in the organization and the culture that’s going to permit staff to be able to move to a place where we can truly use the structures in attachment and trauma-informed care to allow staff to think, to learn, to grow, to develop. How are you as a leadership team going to respond when things might not go quite well within our service? How like how are we going to respond? Uh, how are we going to work together to embed uh these ways of working? Uh so right from the start, it’s all about collaboration, open, transparent communication, you know, it’s almost setting setting the tone, setting the culture. Uh but you know, if anybody thinks trauma-informed care is an easy option, but it can be if you do a bit of training and you get a leaflet and you think you’re trauma-informed. But if people think trauma-informed care and and being responsive is easy, it’s not to be able to deliver this and to be able to do it so it’s created as a living experience for the staff and a direct experience for the children takes a lot of courage and bravery because people need to go and think about areas they would not normally think about in terms of the work.

Colby: 40:58

Yeah, so um I think you’ve touched on the importance of senior management um and or setting setting expectations, managing expectations from the outset. And uh, you talked about you know going into an organization, speaking to those leaders. And while you’re speaking to me, it reminded me of of some previous conversations I’ve had on the podcast about about how we ensure that our that the very leadership of the of these organizations are um uh uh supported to have experiences of of of the model, basically. That you support you know have a have a containing supervisory relationship or relationship with the mentor. Yeah.

Richard: 41:46

Yeah. Can I just say a little bit about how I came to attachment and trauma and phone care? Just a little bit

.Colby: 41:54

Yeah, absolutely. Go ahead. I was working my way around, I was working my way back around to that, but you’re reading it.

Richard: 42:01

Well, because yeah, no, it just somebody came to mind there, and it was and it was the person called Pam Pam McConnell that created five five rivers childcare. So 36 years ago, uh actually on the 19th of September, Pam McConnell created the entity which is called Five Rivers Childcare. And it’s I’ve been there nearly 16 years, and I’ve I’ve stayed there because it’s a secure base for me. Because I believe places of work can also create this sense of security, places you can grow and develop. So I’ve been there for 16 years, but what Pam created, even away back 36 years ago, she noticed that those children who had sadly experienced sexual abuse, trauma, and neglect, the systems weren’t designed to meet their needs. So she was she was very creative and very innovative, and she she started to create residential environments, residential homes for children and young people to come and stay in. And since then, the organization’s significantly grown, we’ve gone into foster foster care, uh, education, we’ve got clinical services, but the key task is to support children at the heart, you know, at the heart of the organization, it’s doing good, thinking about how we can help children and turn their lives around. But PAM allowed the creative thinking about developing a model that could be easily accessible across multiple multiple geographical locations, about thinking about how we we we package up what can be quite complex psychoanalytical, therapeutic community ideas, adapting it into a model that can be translated and easily uh applied if the live and breathing system is on board, if that leadership manager team is in place. Um so yeah, Pam, you know, Pam McConnell just naturally came to mind because without her support and uh Five Rivers is a social enterprise, it’s you know, it’s it’s uh in the UK that means that paradoxically, people have difficulties thinking about sadly, care organizations need to charge because we need staff wages to pay and all that sort of stuff. But as a social enterprise, we reinvest, we reinvest in research, development, invest in our staff, and a bit of the investment that Pam gave was to allow me to invest in creating a model for the organization, which was great. So, yeah, yeah, I wanted to say my appreciation to Pam McConnell for that.

Colby: 44:59

Yeah, it is a remarkable organization because as you mentioned, it has residential care, it has foster care, it has education as a school, has clinical services. Yes, it has multiple schools, multiple services, and crisis intervention. Yeah, and and crisis support services as well.

Richard: 45:19

So, yeah, it’s got these multiple uh so in terms of children, in terms of their care journeys, they can come in at any part. Sadly, children, you know, it’d be a you know, the world would be a great place if children didn’t have to access our services. But the reality is children do, and sadly, in an increasing way across societies, there’s an increase. So, like in the UK at the moment, there’s about a 10% increase in the use of residential childcare. Yeah, uh often sadly, residential childcare isn’t seen as an early intervention, and that’s partly why I developed ATIC because it’s for under 12s initially. That was when I sort of developed the idea that children who are going through repeated placement breakdowns and disruptions in foster care given a given an idea to commissioners and uh uh people who are not sadly not often practitioners in the field. Look, if you see this pattern, there is something else, there’s something else that can be really helpful and harmless for good, and that’s residential childcare. So the notion that we have is we’ve got multiple ways that children can come in and uh have a home with us, uh, and that’s either in residential care or foster care, uh and also access education and the therapeutic services is the need. Yeah.

Colby: 46:51

Oh, yeah. Look, um you’ve drawn you’ve drawn on a number of themes from some fairly recent podcasts. But as I’ve as I’ve been doing these podcasts, one of the things that um has been more and more clear to me is that the this option of last resort is just I mean, that’s what there’s a look, there’s a bit of a story to it. I won’t go into it all, but that that was one that was almost what spurred me on to do the podcast, and in particular a stream of the spot podcast that looks at at residential childcare. I just think that there’s so many problems with this idea of residential care being an option of last resort. I think as I think you did you just touched on in there, there are times when it can be an option of first resort. There are it, and that and and I I’ve been writing and thinking about that and talking to people about that. Um you it it it does, it is something that a number of guests have talked about uh that can be utilized, and this has got to be good quality, good quality, therapeutic focused residential childcare. It can be it can arrest one of the most harmful aspects of out-of-home care, which is repeated placement breakdown. And the other thing is, and Bruce Henderson talked about, he’s my most recent past guest uh on the podcast. He’s he’s probably done the the largest review of the literature, including the uh empirical literature around uh social care, including residential childcare. And um he talked really clearly about um placement matching, and he was in he’s involved with the Black Mountain um care organization, he’s in America over there, and and similarly they have residential and foster um options, and um and it it it it’s allowed what I think you know it sounds like you’re able to do there at Five Res Rivers as well, is is to uh mobilize the care that the children need um where where they are in their journey, and sometimes that’s residential care, often enough that’s residential care.

Richard: 49:24

Yeah, this is very embryonic work in the UK. Um so embryonic uh attachment and trauma-informed care came out of 36 years, you know, the past period of time that we’ve been working, so we’ve harnessed all that knowledge, but that’s only been really since 2016. So I know that’s it might sound a long time, but in terms of changing systems and changing knowledge, uh we’re still on that journey to collaborate and work uh with commissioners with with local authorities because I I feel we’ve got a responsibility to explain really accurately about what can be supportive and helpful for children in terms of their needs. Often we need to translate that for the local authorities and commissioners in terms of the plans that we do. So we’ve got uh you know, when we get the privilege to have a referral for a child, a young person, we spend a lot of time about right, even at that initial phase about really understanding the child’s needs and taking the responsibility for being truly able to say that we are able to support this child, and this is what we would suggest would be helpful in terms of that part of their care journey. Often it comes down to trust, though, with with local authorities and commissioners around is this going to be something that’s gonna be helpful for the child? And and naturally, this is where research and evidence comes in. Being able to deliver really focused uh supports and how to explain outcomes and how to translate that as we go through the journey as well, is support the commissioners to understand that this is being effective, then it then it generates uh more more trust, trustworthy reactions again in the future. So it’s like, yeah, we’ll go back to Five Rivers and we’ll consider this approach again, like residential. It should can be the first option because of the experience. So there is a big responsibility on providers, isn’t that, to be able to make sure that we deliver what we say on the outside of the tin, you know? Yeah, uh, that we walk the talk, going back to that walk the talk bit again.

Colby: 51:57

And I’ve whilst you’ve been talking, I’ve I’ve been thinking about how five rivers with all of with all of those divisions, it’s probably not I mean divisions is the wrong word in if you because it it implies divide, but you’ve got those streams is a better word, and and and you are able, I think I’m hearing, to be to provide an aligned service so that staff might move between the streams, kids might move between the streams, but they have a consistent experience of care across those streams.

Richard: 52:34

And that’s where the model almost provides a tapestry for that. So one of the great things that Sandra Bloom told me when and I learned from what going back to the mentorship thing again, was language becomes the glue in terms of the model, in terms of how we speak about the work, uh how we see the task. And if that is shared consistently, if that language is shared across the different uh almost threads like the education, residential fostering. Children experience this as well. Children experience staffs using the same language, the experienced staff having the same response if situations are occurring. You see the adults sitting down and thinking together, you know. Uh yeah, it creates that uh that harness in the tap. Well, often people call it integration. Uh so one of the things that we do seek to make sure we don’t experience is this fragmentation in the system. In actual fact, people do become that sort of separate siloed uh thinking and the breakdown and communication. So part of the model was as well about the shared language is also making sure we keep these strands interconnected and almost be really aware if they start to drift apart, which can be natural and normal and anxiety. I’m not saying that there’s there’s anything abnormal about that that tension that that can happen, but we are really aware so we can bring things back together.

Colby: 54:11

It’s like and how reassuring for children who leave chaos and uncertainty to come into a place where they uh where the adults interact with them similarly. Because I think I think a task, a therapeutic task or a primary task and a model, it doesn’t make everyone clones of each other, it just ensures that there are there are aspects of uh the way they go about things that are consistent across home and school. And I think that that even just in and of itself, as long as there’s that consistency, that alignment between home and school, and it’s safe and and nurturing, but as long as there’s that, that it that’s gonna have such a massive impact on heightened nervous systems, yeah.

Richard: 55:04

So that magnification is a you know, when I was developing attachment to trauma and informed care, I thought, how can I magnify these helpful relational experiences? Going back to attachment again. How can I magnify these experiences?

Colby: 55:19

Can I say it all comes back to attachment? Sorry, I didn’t want to talk over you, but I I just needed to chime in there. It all comes back to attachment. Sorry, yeah, go ahead.

Richard: 55:30

No, it’s it’s great, yeah, because naturally it’s great, you know. All like research shows like if we’ve got one person, you know, it can have like quite a significant impact on us. But imagine if we can magnify that having 12, 15 people. So like I was looking at okay, if I can create this this approach in the residential care environment and have it in the schools, and when children are prepared and ready to go to their home in foster care, and the carers are embodying this stuff as well. It’s you know how enriching, how nourishing is that for the children, but also it creates this really helpful relational way of working and way of managing stuff between the staff and the adults as well. They’ve got this sense of understanding about okay, when this stuff happens, we get together. Uh, we’ve got different approaches for crisis management. There’s one called an amber flag meeting, which is anybody can call it, it’s like when things start to become difficult, staff can raise the flag, call a space, everybody gets together. We’re all involved in thinking, all involved in supporting. Uh and it, you know, it takes away the anxiety and fear that it becomes an everybody approach rather than somebody feeling their left on their own with a situation. Again, going back to attachment theory, uh, you know, often yeah, we’ve got our own resources and we want to develop that and our staff increase their resiliency. But when it gets to a point they feel overwhelmed, they feel like people either grow or they go sadly in the work. You know, people either grow in the work or uh it feels it gets too much, they leave. So we have like we’re all about growing people, so create and make sure people know they’ve got an outlet if they feel they’ve got to the end of their solutions or the end of the resources. We create this space where they can come and talk through and uh get the helping support they need.

Colby: 57:42

And of course, um um the first of my guests to um talk something uh a little about this was John Whitwell and uh of Cotswold Community and ISP uh integrated services. I’m not sure I got that last bit right, but anyway, John John was talking about uh going to because he went to the it went from residential care to foster care, and uh on the first day the staff, you know, there was something was going on in Stafford came to him and said, What do we do? What do we do? And he says, I don’t know. But but let’s talk, what do you mean you don’t know? Um but let’s talk about it, and I think, yeah, yeah, yeah. Like there’s and that has come back a number of times. Um, in fact, Peter Wilson, who we were talking to about a little bit beforehand, uh uh wanted to name his forthcoming book or title his first coming book forthcoming book, I don’t know. The because the I think the the the the um the the power or the influence or the strength in that is that it invites collaboration. And one of the things that that I’ve noticed, just as a bit of an aside, when I when I do training with um carers, uh if we if a carer brings up an issue to do with um a child in their care and they just don’t and they don’t know where to go with that, the other carers are actually really good at offering solutions, yeah. Yes, but then those same carers feel stuck in coming up coming up with solutions about their own the the children in their in their care. So it’s it’s quite fascinating that if you take if you take almost like a metacognitive stance, yeah, you’re yeah, you’re one step removed from it. The the yeah, that’s such a resource to be around people who are one step removed from being in the in that particular challenge.

Richard: 59:54

I think it’s I think it’s one of the key areas that can impede for. Trauma informed practice in my mind is the inability to tolerate what I call the unknowing. And that’s a direct translation from my work with clients because we can be sitting thinking we’ve got the answer. But the sad bit is if we think we’ve got the answer, we’re missing the opportunity to find out what it is actually like or what the meaning is from the other person. And equally with staff, the temptation is to think about that we’ve got the answer and to do the quick solution. And uh thinking really like back in my early work 30 years ago, I used to be so keen about just getting a solution. Let’s just let’s just do something. Because I used to come to the thing about doing something was better than doing nothing, right? But in actual fact, being able to tolerate uncertainty that uncertainty, that unknown for a period of time creates opportunities that uh can make people feel the part people need to feel part of the solution because otherwise, what what we find out in the terms of the attachment uh people go into that ambivalent state, they feel that they’ve not got a voice, there’s no point in saying, they become silent, and those toxic things within care environments are unawanted because we need we need people to feel they’re part of, they’ve got a voice, they can be heard. Uh and it may be a difficult process this about working through this, but the outcome of it is as golden as I see it. It’s it is to me, it’s the work to be able to because equally the staff are going to have to do this for the children, they’re gonna have to try and understand what the children are communicating through their behavior, trying to make sense of it, uh, and coming to that from a certain lens as well, as we know it’s about uh trying to illuminate about what that communication is that the you know the child is doing between them and the staff.

Colby: 1:02:17

Yeah. While we’re while we’re talking, Richard, um a question without notice has been formulated in in my mind a little bit. Um but hopefully you don’t you don’t mind. Um the question is what it was starting out as what sort of child need needs residential care and it and and but it’s now it’s also kind of in my mind it’s it’s blending a bit with what what does residential care offer uh to children to children in need of care that that perhap of that is per hot perhaps superior that time of need for the child than than other forms of out-of-home care.

Richard: 1:03:11

I’d be interested in your thoughts about that well foster care in its is a in its own right can be highly effective. So in terms of my comments that I’m gonna say about is foster care can be highly effective for those children who are anaphobic about family living. Some of the responses I see children displaying, and it’s not about the family they go and stay in, but they carry inside themselves experiences about being in families that mean it’s going to be highly unlikely that they’re going to be able to stay and create security within that family. Uh it becomes unbearable for them. It’s uh and it becomes unbearable for the uh foster carers as well. And it’s the foster parents can sadly they can they can almost be placed in a situation where the material that they’re getting given to process and uh the behaviours and stuff gets to a point, and often foster carers can get to a point they they feel this task is task is too much for me. It’s too much. They get to yeah, too much. And sadly for children, then if they they start to expand, well, naturally they’ve had one, but their uh the original scene was in the family or origin, uh this is often replicated and reenacted within the foster replacements, and I’ll see the attempts to use foster care well into double figures sometimes. You know, children children will be in that repeated cycle. So if we can identify children as early on that that are gonna often I’ll I’ll see social workers and stuff understanding the children’s history through an attachment and trauma and form lens, understand about their experiences and knowing that that containment is going to be needed in terms of the children’s distress, it’s gonna need much more than foster care. Yeah, foster carers can’t typically manage situations where children act out excessively in terms of acting out against other people or uh the environment of the home, the foster foster parents’ home. So, quite early on, you can almost you can see what I call gateways. I’ve got this notion of gateways to particularly uh care options uh to help be able to identify through assessment, and this is where the psychological lens can come in within care organizations commissioning. I don’t know how it is in Australia. I don’t know if you know, I worked in New Zealand for a little period of time myself, but yeah. And I’m like I’m always fascinated about where care the care system is sort of held within the UK, it is social care. There is a greater involvement with health. To me, there needs to be even more. The more that we can help commissioning teams understand the psychological and emotional aspects of the child’s needs, then that can more effectively inform what part of the care journey does that child need. Does the child need residential care and all that that it offers, increased containment, and less risky staff burnout, foster carers, fostering families, massive risk of that? Uh we can provide this more integrated educational magnification of these principles that often child needs. And that often cuts down the time. Some of my some of my research at the moment has shown that if you do this early enough, it can be an early intervention that over the care journey period actually reduces not only the the child’s need for in terms of staying in these higher higher recruiting environments, so the child can go to foster care, uh but it also cuts down the time. Uh because naturally I saw the other end like working in that prison-based therapeutic community for adult male life offenders uh who had committed it was sad to see how many of those uh human beings had been in the care system. So this notion of early intervention and about stopping patterns and doing the you know, doing the work as early as possible, not as late as possible. To me, it’s a cost saver. To me, it’s uh to me it’s a no-brainer. It’s like just it’s just uh uh but it’s a challenge I know for systems to think past a year. You know, most uh business plans only cover one year, most governments I think only covers the their term in office. Some of this stuff is moving the systems to longer term thinking, longer term perspectives. Uh but I but I truly believe the more people that have these these ideas, the more we can send the messages out in the box to social care and social work and the political system. About let’s turn this thinking, you know, the mindset from short termism, like to sort of longer term.

Colby: 1:09:02

And and I mean, I think part of the whole option of last resort is for residential care is is it’s the most expensive form of care. So we don’t want we don’t want to be uh what we don’t want to be uh focusing initially on on the most expensive form of out-of-home care.

Richard: 1:09:24

Is it not?

Colby: 1:09:26

We’d rather we try foster care. And and and there is a a deeply held belief in society that the that family is the best place to raise children. But it’s not it’s not for those children, as you said, who are phobic of family, who have a phobia. And I’ve written, I first wrote about this um in a published paper 13 odd years ago. That um, and and so to me, residential care provides a psychologically so people think, oh, you know, with all the scandals and and so on, this is you’re mad for saying this. But in actual fact, residential care provides a psychologically safe, relationally safe care environment that is better for certain young child certain children and young people than than putting them into a into a family-based environment. And we we need all those options. We in my state here, they they embarked on a bit of a uh um uh an endeavor to to get rid of residential care because it was seen as being because it was of low quality, seen as being of low quality, option of last resort, expensive, all of these things. But but in a what I’m hearing you say is in a um in a functional, adaptive, um, effective uh social care system that that meets that is able to tailor care to the needs of the children and use fitness and match it placement matching um to its best ability, then residential care has an equal place alongside uh family-based uh care options. And I really like what you said that you think that it that it can enhance the young person’s preparedness to go into or ability to go into a family-based placement such that that’s uh more successful for them.

Richard: 1:11:39

Yeah, uh the evidence illustrates that uh so early on in the delivery of the attachment trauma-informed care model, it was children and young people who had largely been through that repeated placement disruption and ending and leaving one one relationship and going to another relationship, and often being out of education that would come into the service, and naturally we we we were we were still able to attain the trajectory that we wanted, the aspirational trajectory for the children in terms of them being able to go into foster care and becoming more secure. Uh but while even the children used to say to me about the trust thing, about almost their mindset was that they were gonna even have to leave that home, you know. It’s like the you know, the attachment systems have become so uh hyper-vigilant that they believed that nobody could care for them, nobody could uh tolerate what they were going to give us. And it’s like, wow, I’m not like I used to say, I’m not surprised that you’re giving me this stuff to have to handle for you. You know, this is what I used, you know, in terms of my understanding with the children, is that uh it’s quite understandable if they’re exposed to situations that are repeated and chronic and things don’t work. Uh yeah, it is still possible, but it’s much better for the for the child and the whole system to be able to identify those children, it’s not all children. No, uh you know, the great thing at the moment is that Five Rivers has changed caring for over a thousand children, and uh the majority of those children are in foster care, very happy, really good outcomes, you know, great foster parents, you know, doing great work, but there is a group of children and young people that I feel that we owe them to identify when residential uh the residential environment is as the environment that’s best for them. Yeah, yeah.

Colby: 1:13:59

I think that’s a wonderful spot to finish up, uh Richard, because um time is time is marching on. I’ve put I’ve kept you for over an hour. Um it’s been fantastic to chat with you and um and talk more about attachment uh on the podcast. Everything comes back to the catch. Um I’m being a bit time-cheapy. I’m kind of sort of being time cheap about that. Yeah, it’s been thank you for taking the time and uh invariably I I say it before I’d like to have you back on again at some stage because there’s so much more that we could talk about. So thank you.

Richard: 1:14:42

Thank you so much, Colby, for the time today. I’ve really enjoyed speaking to you.

Colby: 1:14:47

As have I. Thank you.

The Case for Quality Residential Childcare – A podcast interview with Bruce Henderson

“We don’t need to pit different kinds of care against each other. The real question is quality.” Professor Bruce Henderson shares compelling research showing why high-quality residential care should be an option—not a last resort—for vulnerable children.

Rethinking Residential Care

In a world where residential care for children is often viewed as a “last resort,” Professor Bruce Henderson’s evidence-based approach brings a refreshing perspective. His comprehensive analysis of the research challenges longstanding assumptions about what’s best for vulnerable children in out-of-home care.

Professor Henderson’s experience with Black Mountain Home for Children in North Carolina provides a compelling case study. What began as a struggling facility with outdated approaches was transformed through quality leadership into a model organisation offering a continuum of care. Today, Black Mountain provides not only residential care but also foster care, adoption services, family reunification support, and programs to help young people transition to independence. This approach recognises that children’s needs are diverse and often change over time.

The concept of “fit” emerges as central to Henderson’s argument. Rather than adhering to a rigid hierarchy of placements where family-based care is always prioritised, Professor Henderson advocates for matching each child’s specific needs, history, and circumstances to the most appropriate care environment. For some children, especially those who have experienced multiple failed foster placements or who need to remain with siblings, high-quality residential care may be the most appropriate first choice – not a last resort after everything else has failed.

One of the most disturbing statistics Professor Henderson shares is about children who have experienced dozens of placements. He mentions a young person who had been in 35 different placements by age 15, and the interviewer notes working with a child who had experienced 50 placements. The damage caused by this constant upheaval – educationally, socially, and psychologically – is immeasurable. For these children, stability in a well-run residential setting may be far preferable to continuing the cycle of failed family-based placements.

Professor Henderson’s critical analysis of the research literature is particularly valuable. He points out that much of the negative perception of residential care stems from a handful of influential studies, particularly research on Romanian institutions, which examined exceptionally poor care provided to infants and very young children. These findings have been inappropriately generalised to all forms of residential care for children of all ages. Meanwhile, research showing positive outcomes from quality residential care – including survey research with alumni who report positive experiences – receives much less attention.

The core issue, Professor Henderson emphasises repeatedly, is quality rather than setting. “You can find good and bad versions of every kind of care,” he notes. Quality care comes down to relationships – selecting the right staff, training them properly, supporting them adequately, and providing stability. When these elements are in place, children can thrive in residential settings.

Professor Henderson challenges the “family first” language common in child welfare policy, preferring the Danish approach of “children first.” This subtle but profound shift places the focus where it belongs – on the needs of individual children rather than on ideological preferences about care models. For some children, particularly older adolescents or sibling groups, quality residential care may be the environment where they can best heal, develop, and prepare for independent adulthood.

As jurisdictions around the world reconsider their approaches to child welfare, Professor Henderson’s evidence-based perspective offers a valuable corrective to simplistic thinking. Rather than eliminating residential care options, we should be focused on ensuring quality across all care settings and making placement decisions based on the specific needs of each child. Our obligation is to provide vulnerable children with environments where they can heal from trauma and develop to their full potential – whatever form that environment might take.

You can listen here:

You can watch below.


About Bruce:

Bruce is Professor Emeritus of Psychology at Western Carolina University, and is a child psychologist (PhD for Minnesota) whose research until 2018 focused on the development of curiosity and memory in children, and on teaching in higher education. Since then, most of his writing has been about residential care. His book Challenging the Conventional Wisdom about Residential Care for Children and Youth: A Good Place to Grow (Routledge, 2024) is a critical appraisal of the research on residential care and a defense of high-quality residential care for children who need it. For over 35 years, Bruce has been involved with the Black Mountain Home for Children, Youth, and Families, an organization that provides residential care, but also has foster care and adoption services, transitional and independent living programs for older youth, and works to reunite children with their families of origin whenever possible. Bruce lives with his wife Judy in the mountains of Western North Carolina. 


Related Podcasts:

I am sure you will also like my conversations with Dr Laura Steckley and Dr Jenna Bollinger. Click the links below to watch and listen:


Transcript:

Colby: 0:00

Welcome to the Secure Start podcast.

Bruce: 0:04

I think it’s a huge mistake to break up sibling groups when that may be the only part of their family that they’re still in touch with on a regular basis. I think the record that I know of was a young man at the age of 15 had been in 35 different placements 35 different placements, and if you think about what that does to your life, it’s just. I mean educationally, socially every way you can think of.

Bruce: 0:37

I think the issue is a matter of finding a fit between a particular child, that child’s history and an environment that’s going to work for that child, and I think residential care needs to be one of the options. I don’t think we need to pit different kinds of care against each other. I mean, you can find good and bad versions of every kind of care. And the question, the real question, is quality, the quality of the care, and it comes back to that every single time and to a large degree, the question of quality is a question of building relationships. If in fact, there’s a good chance of going back to the family of origin, residential care is kind of a neutral place to go.

Bruce: 1:18

The evidence is that we lose foster care families at a rapid rate and I think it’s oftentimes because of that insensitivity about the nature of that child. I don’t think residential care should be the norm for kids who need care. I think it’s gonna be relatively rare, but it needs to be one of the options. The last resort notion came from a belief that residential care was inherently bad for children. But if you ask a large number of alumni of residential care about their experiences and they tell you. They had good experiences and they never would have preferred foster care. You’ve got to give some attention to that.

Colby: 2:08

Welcome to the Secure Start podcast. I’m Colby Pearce, and joining me for this episode is the author of perhaps the most comprehensive review ever of the research evidence in relation to children’s residential care. Before I introduce my guest, I would like to acknowledge the traditional custodians of the lands that I come to you from the Kaurna people of the Adelaide Plains, and acknowledge the continuing connection the living Kaurna people feel to land, waters, culture and community. I’d also like to pay my respects to their elders, past, present and emerging. My guest this episode is Bruce Henderson.

Colby: 2:55

Bruce is Professor Emeritus of Psychology at Western Carolina University and is a child psychologist with a PhD from Minnesota, whose research until 2018 focused on the development of curiosity and memory in children and on teaching in higher education. Since then, most of his writing has been about children’s residential care. His book Challenging the Conventional Wisdom About Residential Care for Children and Youth A Good Place to Grow is a critical appraisal of the research on residential care and a defence of high quality residential care for children who need it. For over 35 years, bruce has been involved with the Black Mountain Home for Children, youth and Families, an organisation that provides residential care but also has foster care and adoption services, transitional and independent living programs for older youth and works to unite children with their families of origin whenever possible. Bruce lives with his wife, judy, in the mountains of western North Carolina. Welcome Bruce.

Bruce: 4:14

Thanks for having me, Colby.

Colby: 4:16

Yeah, and you quiped a little bit earlier about speaking to someone in the future, which probably the laugh that it got from me probably would have if we’d been recording. It would have blew out a few eardrums if we included it in the podcast recording. But yes, it’s nice to be here too. It’s Thursday for you and Friday for me.

Bruce: 4:41

And don’t give me the lotto numbers. I don’t need them.

Colby: 4:44

You don’t need them, you’re doing okay. Well, that’s good to know. Yeah, yeah, in my neck of the woods, professor Emeritus means that you’ve retired. Is that the same in America?Bruce: 4:58

Yes, it means I retired from teaching and committee work and you’re given access to your computer and to your email and you can sit on dissertation committees and things like that.

Colby: 5:14

But yeah, I basically retired from teaching in 2020 after 42 years, 42 years, and look, and I was going to uh make the point that it doesn’t really look so much that you, like you, have retired as such my, my brother calls it a faux retirement a faux. Yeah, that’s probably a good yeah, that’s probably a very good term to use yeah anyway, as long as you still enjoy it, why not?

Colby: 5:42

that’s right and that’s right yeah, and particularly brain active yes, yes, I can imagine myself writing, you know, until I can no longer write, I would in fact, I’m looking forward to retiring. I’ll probably do a faux retirement myself, in terms of I’ll retire from certain activities and free up a bit more time for reading and writing in the area.

Bruce: 6:06

Well, my job was at a regional comprehensive university we call them here, not a research university and so when you did research and writing, you had to find bits and pieces of time. So I find it quite a luxury to have a good deal of time to write. It’s been fun.

Colby: 6:26

Yeah, yeah. So, as I read out in your bio, your work activities until relatively recently were very much focused on teaching and training and you were interested in children’s curiosity and memory from a research point of view. But you have also had this longstanding connection to residential childcare, wondering if you’d tell us a little bit more about how that came about.

Bruce: 6:58

Well, my wife talked me into doing that. I didn’t really want to do it, but she had visited the Black Mountain home and at that time in 1989, the home was in a good deal of difficulty. Their leader had died unexpectedly. He had actually fallen back behind the times and really had needed to retire years before he died, and there were lots of problems and I didn’t really like what they were doing there. And so I went on the board and at that time met with other board members trying to find a way to gracefully close the place down. And it had become. It wasn’t serving very many children and it wasn’t, in my opinion, serving them very well. But instead of closing it down, we hired some effective leadership and that turned the place around.

Colby: 7:59

And that was, as you say, 35 years ago, in the early 1990s. Yeah, yeah, as you say, 35 in the early 1990s, yeah, yeah, what was it that you noticed?

Bruce: 8:12

where had it gone? Gone awry? From your perspective, I think, uh, they hadn’t kept up. Come up, uh, come along with new ideas about child care. They, they were still using almost a barracks kind of situation and they didn’t have cottages, they didn’t have enough house parents, the physical facilities had gotten old and dilapidated, they didn’t have a good education support. There were lots of things that needed to be fixed and they didn’t really have good relationships with the children’s families, and all of that needed to change.

Colby: 8:50

Well then, tell us a little bit about how that happened, how it came to be turned around.

Bruce: 8:57

Well, I think it’s almost always leadership, and we hired two leaders. It was a couple and the man had been involved in mental health he was a Presbyterian minister and he’d been involved in mental health and his wife was a child welfare lawyer and so they brought some skills that were really well applied in the child care situation well applied in the in the child care situation, and having having a lawyer around was quite useful in trying to help kids navigate the legal system.

Colby: 9:33

That oftentimes is pretty oppressive, and having that that kind of background really helped a lot and I was impressed to read that not only is Black Mountain these days a therapeutic residential child care facility, but it also has fostering activities associated with it. It has some endeavour around looking after young people who are entering adulthood who have been in out-of-home care, and also reconnection or strengthening connection with birth family.

Bruce: 10:13

Yeah, I think that what you see at Black Mountain is increasingly common with good programs. They often call it a continuum of care. I like to call it an array of services, because I don’t think continuum is an accurate description. But you know, children are complex. They’re as complex as they’ve ever been. Families are as complex as they’ve ever been, and so I think the programs need to have the flexibility to assess what’s going on with a kid or a family and then use whatever services are needed at that time, and you know that can change over time. It’s different for every child and family. Every child and family and we are at Black Mountain, like a lot of places, we’re dealing with kids who’ve had just awful experiences. I think the record that I know of was a young man at the age of 15 had been in 35 different placements, and if you think about what that does to your life, it’s just I mean educationally, socially, every way you can think of that’s insane.

Colby: 11:30

And so those are the kinds of situations we’re often dealing with arises that you see the young people with that level of well, that type of history, largely because of residential care being seen as an option of last resort, so that definitely has an impact.

Bruce: 11:58

So what? What has often happened to these young people is that they’ve been in foster situations that didn’t work, or even even, sometimes, adoption situations that didn’t work, or even, sometimes, adoption situations that didn’t work, and then they’re put in residential care and the pressure and this is not just true in the United States, it’s true all over the world there’s pressure to get the young person out of the residential care as fast as they can and oftentimes it just leads to another bad foster placement that doesn’t work and the kids suffer for it.

Colby: 12:33

So I guess what I wonder with what you’re saying is that sometimes children may even yo-yo in and out of residential care or between foster situations and residential care.

Bruce: 12:46

Some of the histories are amazing. I mean, you look at it and you say how can that happen to any child?

Colby: 12:52

Yeah, well, as it happens, I work therapeutically with children in the out-of-home care sector primarily, and I have a young person that I see at the moment who’s been through 50 5-0 placement that’s unbelievable, unbelievable yeah, yeah. So, um, the option of last resort, um, how does that sit with you?

Bruce: 13:24

Well, you know, I think the issue is a matter of finding a fit between a particular child, that child’s history and an environment that’s going to work for that child, and so the idea that you’ve got a hierarchy of placements makes no sense if you think in terms of fit, because there may be children the very first thing that would be best for them would be in residential care, and I’m not talking about being in residential care the rest of their lives.

Bruce: 13:57

Oftentimes, what they need is a period of time. It may be six months, it may be a year period of time. It may be six months, it may be a year, a year and a half, two years. It varies. And there’s another situation that is common and that is sibling groups.

Bruce: 14:11

And oftentimes sibling groups in the United States and I know other places get broken up because their foster families don’t want to take more than one child, and I think it’s a huge mistake to break up sibling groups when that may be the only part of their family that they’re still in touch with on a regular basis.

Colby: 14:33

Yeah, if you stop and think about it, and this is part of the problem, certainly in many jurisdictions, and what I’ve heard from many people talking on this podcast is that practice is dominated by a set of, I guess, principles or ideals or beliefs, indeed, one of those beliefs being the best place for children to grow up is in a family environment. The best place for children to grow up is in a family environment, and if that’s your paramount decision-making standard, then you get those sorts of situations where children are separated from their siblings, because if it’s a large sibling group, it’s very rare or difficult to find a family-based placement where they can all be together, and it comes with complexities when you do put siblings together as well that I think child welfare authorities often worry about.

Bruce: 15:43

Well, I think you’re right about the concept of family has, I think, been used in an unfortunate way, because sometimes what these kids need is a home. They need a place that is a home, and sometimes your biological family isn’t home, or at least it isn’t for a period of time.

Colby: 16:02

until it can become a home, you need another home yeah, yeah, I often and you made a very good point in there I I think the language we use is really important. I I strongly encourage child welfare authorities to um use the word, use the that’s not a word unless you make it one but use could not, instead of cannot be safely cared for at home. Because you see kids who tally up a huge number of placements over in their teens by the time they reach their teens and they’re still writing that the young person cannot be cared for at home, but no one’s really assessed that for years and years and and so much damage is being done in the meantime with, with, through failed placement endeavors. Uh, in family-based care.

Colby: 16:56

You see, black mountain is interesting for a number of reasons, not least of which is you have those, at least those four streams of endeavour that I talked about children’s residential care, the foster care, the transition from care and the family reconnection. I think. I mean it sounds like an absolutely ideal model service to me From your point of view view. You’ve talked about fitness and I think I think fitness is a a really key concept here, because fit in a struggling child welfare system, fitness goes out the window. They’re just looking for a bed, right, right, yeah, that’s right. But I also wonder about what your thoughts are about the relative standing of residential care alongside family-based foster care or adoptions, which you do in America.

Bruce: 18:02

Well, my view is that what we need are options because of the fit fit question, and I think residential care needs to be one of the options. I don’t think we need to pit different kinds of care against each other. I mean, you can find good and bad versions of every kind of care, and the question, the real question, is quality, the quality of the care, and it comes back to that every single time and, to a large degree, the question of quality is a question of building relationships, and one real problem with the last resort notion is that oftentimes the children are placed with the expectation they will not build relationships because they’re going to get yanked out soon, and that’s, I mean that that’s becomes a self-fulfilling prophecy if you, if you say, well, um, you know that here’s the, here’s the care of last resort. Therefore, don’t build relationships, and then in, in fact, it’s bad care, it’s bad care by circumstance, and you said you talked a little bit earlier.

Colby: 19:12

You mentioned that for some children it may be the first resort, the option of first resort, and this is something that is very much in my mind at the moment and I’ll just just just very quickly. The reason being is that my, my long-held view or observation of children, young people, who find their way into out-of-home care, the trauma that they’ve experienced is relational trauma. It’s happened at the home, it’s happened, you know, with their parents and they come into care with. Well, I would say it’s uh for people, because people don’t easily think of it in this way. I would say it’s akin to a phobia, where the phobic object is there is a relationship, is relationship or relational connection.

Colby: 20:03

Now it’s, I would say it’s more than akin to a phobia. It is a phobia and that phobia has, you know, probably relative degrees of difficulty for the young people, a challenge for the young people and there are, there are probably young people, there are undoubtedly young people who come into care that perhaps the worst place to put them is in the family environment, where they’re really challenged by relational closeness and the expectations of the adults in those environments. And again, I think that comes back to what you were saying about fitness. I wonder have you got any comment you’d like to make about that?

Bruce: 20:48

Well, you know, I think something that goes with that is that we often think in terms of these children who’ve had traumatic experiences in their families, all in terms of parent-child attachment.Bruce: 21:04

But as kids get older, it’s their peer group that’s increasingly important.

Bruce: 21:09

And unfortunately, there has been a mythology that’s built around the idea that if you put kids in residential care, they’re just around other troubled kids and that’s just more trouble, when in fact I don’t think the research supports that.

Bruce: 21:24

And I think that if you have high quality care, as kids get older certainly when they’re by the time they’re 12 or 13, their peers are becoming increasingly important and that peer group can be a powerful form of relationship and, under the guidance of sensitive adults, that can be an important part of their therapy. And the idea that you’ve always got to go back to the infant-child attachment model I think is a mistake. Now, the infant-child attachment model works in the sense that every social relationship is about kids sending off signals and needing to get sensitive responses back from those they send the signals to, but it doesn’t have to be a parent and it doesn’t even have to be an adult yes, in fact, um children will continue to make relationships that we would we would refer to as attachment relationships throughout their throughout their growing years and even as adults as well.

Bruce: 22:30

And I don’t want to, you know, put down the parent-child relationship, because I mean, if it had worked in the first place, the kids would have been a lot better off. But the other thing I know is I’ve rarely met a child who wouldn’t go back to their family if they possibly could. I mean that that that is fundamental, and even when they’ve been mistreated, and even when they know it’s not a good situation in their heads, they would love to be able to go back to that. And so I don’t want to suggest that’s not an important relationship.

Colby: 23:05

it is yeah, and I think it’s something that it should be aspirational in terms of our endeavors, that we, we, we do endeavor to try and return them, and part of the part of my reasoning around this is that children form multiple attachment relationships, but their overall attachment style is a is influenced by all of those relationships.

Colby: 23:31

So one of the reasons why placements, foster placements break down, not least of which is that the children are challenged, potentially overwhelmed, by the expectation of the foster carer around relational closeness, is that they’re carrying around all this attachment baggage for want of a better term from their relationships with their parents and that impacts their capacity to form a new attachment form, an attachment to their current carers, and also it impacts their overall attachment style and those two things interplay with each other.

Colby: 24:12

So you know, I call it the secure ideal. Child protection authorities seem to be relentless in trying to pursue this idea of attachment security, but in the process they often neglect these historical relationships or they may still be contemporary, but they may also be unrepaired, and those relationships do hamper our efforts, I think significantly, to achieve an outcome where children and young people approach life in a well-adjusted way, well, cognitive psychologists would call it mental models or schemas, and that’s how we interpret our worlds, and these kids often have mental models that are distorted in important ways, and partly what therapy is about is working on those mental models and providing new models.

Bruce: 25:09

And uh, and you can’t provide new models.

Colby: 25:12

If kids are changing situations over and over and over again, they, they never get a chance to form them yeah, yeah, and if they’re just putting transference into all of those, there’s a lot of transference going on into all of those new relationships and too often unhelpful counter transference. But one other thing I think you touched on. I just wanted to ask you, before we move on, do you think that residential care, children’s residential care, could be an option of first resort, and under what circumstances do you think Well, I think there are a couple of situations residential care, children’s residential care, could be an option of first resort, and under what circumstances do you think?

Bruce: 25:50

Well, I think there are a couple of situations. You know. If in fact there’s a good chance of going back to the family of origin, residential care is kind of a neutral place to go compared to having to get a brand new family and starting all over again. And residential care under those circumstances might be the best place for kids to be while their family’s getting their act together.

Bruce: 26:17

And so I think that’s one. Another one is the sibling situation, and at Black Mountain I’ve seen situations where we’ve taken in three or four kids at a time and they, for those kids, those sibling relationships, are the most important relationships in their lives, and so that that, I think, is sometimes a good reason to put children in a residential care as a first resort. There may have, you know, there are also, I think, red flags. There are red flags in some kids especially, you know, adolescent, young adolescents, where it’s clear that they don’t want another family and that you’re really putting not only them at risk but the poor foster family at risk. The evidence is that we lose foster care families at a rapid rate and I think it’s oftentimes because of that insensitivity about the nature of that child. And you know, I feel for social workers, social workers around the world they’re too young, they’re too inexperienced, they don’t last think, I think they’re in incredibly difficult situations.

Colby: 27:29

But I think we’ve created some of that difficulty by doing things like saying um, well, residential care is last resort yeah, when indeed it as we’re talking, I mean we’re highlighting some of the, you know, the manifest strengths of residential care, and I know from reading some of the you know the manifest strengths of residential care and I know from reading some of your writing you’ve talked about stability and resources as strengths Wonder if you might tell us a little bit of your thoughts about that.

Bruce: 28:02

Well, you know, this gets complicated because it’s related to what I think has been the stereotype of residential care that has kind of ruled the literature over the last 30 or 40 years. And I think that what they look at is they say that residential care is inherently unstable because the caregivers are coming and going Well in high quality care. That’s not true. In high quality care, where you’re compensating your house parents, for example, well and you’re making their jobs doable and attractive, then you can get long-term stability in relationships. So I think that stereotype has worked against it. If, in fact, the residential care is not providing stability, it is not high quality by definition. It’s not able to provide high quality care Resources.

Bruce: 29:07

I think the most important resource we’ve talked about relationships and those are the most important resources. But I think also there are resources like specific forms of therapy for some kids with particular traumas, but also just basic things like education. One of the things that happens to these young people who’ve been through dozens of placements is they’ve not only changed families, they’ve changed schools, they’ve changed neighborhoods, they’ve changed playgrounds. They with the same group of children and adults is just. For some of them that’s the first time that’s ever happened to them in their lives.

Colby: 29:54

Yeah, yeah, I think you speak compellingly about these aspects of residential care that are strengths and often overlook strengths.

Bruce: 30:07

You’d have to say when the dominant, when the dominant view is that residential care is is the lowest standard of care and the option of last resort well, even related to to foster care, one of the one of the advantages we have at Black Mountain is we we have a campus and we have resources there, and one of the advantages we have at Black Mountain is we have a campus and we have resources there, and one of the things we can do for foster parents is provide them with resources. And one reason that foster care places don’t make it is because the foster parents don’t get enough support. So we’re careful about identifying the parents in the first place, but then we also support them. It may be if it’s very young children.

Bruce: 30:51

it may be something as simple as diapers, providing them with diapers, which are very expensive, or it foster children that they wouldn’t have otherwise, and now they’re getting some of the same experiences as the residential kids are getting and we can also work with them in terms of things like educational planning, vocational planning, and that really helps those foster parents.

Colby: 31:26

Yeah, and what you’re describing is a is a community, a therapeutic community that’s right, that’s right. Yes, that’s that’s right, and you know a lot of, I guess, even just from my own jurisdiction, where I’m most familiar a lot of these things that that we’re talking about just don’t exist in residential care yeah, that’s right, that’s right and so residential. I want to get on to talking a little bit about the research in a moment, but it’s probably worth mentioning beforehand that residential care is a heterogeneous group, just as families are.

Bruce: 32:02

That’s right and worldwide it’s incredibly heterogeneous and some of it’s good and some of it’s bad, and I will say that I have tended to focus on private residential care. I am not in the sense that I’m not sure for profit residential care. I don’t know how you can make a profit in this business. I don’t know how you do it and make a profit, and I haven’t looked closely at for-profit care. I read the newspaper too, and I read the stories about a lot of problems in for-profit residential care, but I just don’t, unless your government is supporting it well or you’re a private, uh organization that has extra support from, from donors. I don’t know how you do it, yeah it’s definitely an.

Colby: 32:59

What we’re talking about is expensive care or at least someone taught me the task about this about whether you call it extensive, sorry, expensive or high cost, though, and no, he was arguing that it’s high. When it’s done well, it’s high cost, expensive kind of has connotations of not being really value for money, but just for image, I guess.

Bruce: 33:26

But yeah, I think the key, key word is value. Uh, I mean, it’s a question of values. Uh, you know, the united states spends billions and billions of dollars on aircraft carriers that float around the the world and in the sea. Uh, we spend enormous amounts of money on betting, on sports activities and lottos and so forth. And it’s a question of you know, where are you putting your money? I don’t think residential care should be the norm for kids who need care. I think it’s going to be relatively rare, but it needs to be one of the options.

Colby: 34:10

And I guess when you say the norm, are you saying that children? Probably it’s not the best place for children to grow to independence so that they spend all their time in care, in residential care.

Bruce: 34:25

Well, again, it depends on the child and the environment, and when we get new youth, when they’re 14 or 15, it may, in fact, be the best place for them to grow to independence. Because we can, we can provide the support in terms of training and support. You know, for years and years in many states in the United States, when a child turned 18 in foster care was basically by it’s been nice knowing you, and for most 18 year olds, the idea that you’re going out on your own without any support, I mean could you have done it? Could I have done it? I mean I can’t imagine it and so that idea was just crazy. So I think the changes in recent years to provide more support for older kids it may be a 15 year old. They need to stay in residential care until they get the skills to be independent. But yes, certainly there are situations where it’s going to be a lot cheaper, more effective, to find a forever home for children, whether it be a really good foster situation that’s going to remain stable or adoption.

Bruce: 35:37

Now I have concerns about adoption. In the United States. We’ve had a tendency to rush to adoption in too many cases and I don’t like the idea that families of origin can be cut off quickly. That shouldn’t happen. If they need to get their act together in order for their child to come back to their house, give them some time for it, because one of the naive aspects of some of the changes that occurred in the last decade was the idea that you can fix families real quick and then send the kids home. I mean that I don’t know who told them that could happen as a psychologist.

Bruce: 36:17

That’s crazy to me yeah, yeah.

Colby: 36:21

So so the issue with residential care, or the I guess the point sorry that we’re that is being made is that, um, there, there needs to be an ongoing, perhaps, assessment of what is the best care arrangement for this person. So, um, so that that can happen at the beginning when children come into care. And what I’m hearing you say is that there shouldn’t be a distinction in relative status between residential care and a family-based care environment. They’re just all part of the care options and they have equal standing and merit because they cater to children who have different needs, the variability of needs, and then, as a child travels through the remaining years of their growing up, their childhood, there can be a continuing assessment of fitness and what is, what is the best placement environment for them. And we need residential care to have the same standing as an option as, uh, as those family-based options.

Bruce: 37:44

That’s what what I’m, I guess, to summarize, yeah the last resort notion came from a belief that residential care was inherently bad for children, and what got me going on and looking at the research was that a law that was passed in the United States in 2018 that said that no federal funds could be used for residential care. And I was the chair of the board of directors at Black Mountain at that time and a reporter called me up and said you know, you’re going to lose significant amount of money here. What are you going to do about it? Now, black Mountain is a faith-based organization and I said we’re a faith-based organization. We’ve been working with kids for a long time. We’re going to find a way to work with these kids and meet their needs.

Bruce: 38:39

Well, I got attacked immediately by a lobbyist in Washington DC who said you people who are spreading this notion about good residential care, that’s phony and I’ve got the research to support it. And he argued that he had three pages of citations of studies that showed that residential care was inherently bad for kids. Well, there I was, a child psychologist and somebody with research background and research methodology and I thought, well, I’m going to take a look at those citations. And that got me in looking at the whole literature. Now it turned out that those three pages of citations didn’t have a single one that supported what he was saying, but it got me into that literature to look at what actually was going on I’m going to come to that in a moment.

Colby: 39:36

But what I would say I mean we, because we’re going to have people who listen to this podcast. Perhaps. Perhaps we’ll get a lot of people who listen who are kind of thinking similarly, but we’re going to have a proportion of people who think that this is nuts. You know, talking positively about residential care. And there is and I know I’ve had, I’ve put, I remember a post I put up about residential care some time ago on LinkedIn and I didn’t get any comments, but one where the person who commented basically said that residential care was basically a repository for adults who engage unlawfully with young people, and they weren’t as vague about it as I just was.

Colby: 40:32

But I think to those people, to those people who are concerned about residential care, I would say that my understanding of what we’re talking about, the message is this that in some instances and for some children, residential care is not a good option. So, in some instances, because residential care is not always the same and there are residential care programs or facilities that do not meet the needs of the children and young people and for other children and young people, that’s not what they need at this time. They need to be, they’re ready and they need to be in a caring family option, or they need to go home to their parents a parent or parents? Yeah, I think so, and I think, think so. It’s a good time to go to the next part of our conversation with the. What does the research actually say about children’s residential care, including in comparison to other care options in out-of-home care?

Bruce: 41:50

Well, you know, I think I started off the book with an early chapter on research methodology, because I think you need to think carefully about this research.

Bruce: 42:03

It’s a messy area and there’s some things that we can’t know, and I think it’s important to keep that in mind.

Bruce: 42:12

I do not think there’s any way to prove that residential care is inherently bad or that it’s good, because of what you were talking about earlier the range of different things we’re talking about, and so definitional issues are really important and I’ll just say up front that I think there’s certain forms of residential care that seem to have consistently been poor, and that’s correctional juvenile justice forms of residential care that seem to have consistently been poor, and that’s that’s correctional, juvenile justice forms of residential care, and I think that’s because they rarely, if ever, use a developmental model, they never really understand the way kids work, and so that all over the world you know juvenile justice interventions in residential care have not worked.

Bruce: 43:03

Now I think that when you look at the research that says residential care is inherently bad, a problem with making that statement is all you have to do is find one, one residential care situation that isn’t bad and then that blows the inherent out of the water, it’s not by its nature, it’s, again, the quality of the care. So, anyway, when I started looking at the literature, it became clear to me that there’s a handful of studies, research studies that have had an enormous impact on the view of residential care, and the single most important one is the study of the so-called Romanian orphans who by?

Bruce: 43:47

the way were not orphans at all. But that study, the Bucharest Early Intervention Project, has just dominated all the talk about residential care for almost 30 years now.

Bruce: 44:06

And it appears over and over and over in the statement, and that was a situation where there was lots of money for research and American researchers, including good researchers from Harvard University, were involved in the research. They’ve published dozens and dozens of journal articles out of it and indeed the care that was given in Bucharest was horrible care and it should never be repeated. But what’s happened is that that research has been generalized. It was, it was research on infants and very young children, and yet it has been generalized to all forms of residential care, for all kinds of different kinds of residential care, for kids of all different ages and backgrounds, and that’s a. That’s a research. No, no ages and backgrounds. And that’s a research? No-no, you don’t generalize from one kind of research to completely different situations, different majors, different kids. I mean it’s just amazing to me that it has been applied so naively. And there are a handful of other studies that have the same problems, have the same problems. There was one that was funded by the Annie Casey Foundation that basically looked for kids or adults who had grown up in bad residential care and interviewed them and said residential care is terrible. I mean it just frankly. It’s researchers not following their own rules.

Bruce: 45:45

Now, on the other hand, I think there’s evidence that it’s not proof. It can’t be proof, but I think there’s strong evidence that good residential care has positive effects. And some of it is just simple survey research, which tends to be. You know, researchers tend to look down their nose at survey research. But if you ask a large number of alumni of residential care about their experiences and they tell you they had good experiences and they never would have preferred foster care, you got to give some attention to that. If you look at simple pre-post studies, kids come in and you look at them when they come in, you look at them when they leave and they get better consistently. Now, that’s not going to prove that it was the program that made them better, but it all suggests that it’s not making them worse. That’s not going to prove that it was the program that made them better, but it all suggests that it’s not making them worse. It’s not.

Bruce: 46:46

So I you know what I did in the book was to was to kind of look at both sides and I looked very critically at both sides and I and I and there is no perfect research. There’s not going to be perfect research, but the evidence is that if you do it well, kids thrive, they do grow. And then in the book I focused on two very different models of residential care the teaching family model, which has behaviorist roots and a lot of people I work with don’t like behaviorist roots but I don’t think the actual application of the behavioral psychology and the teaching family model has been. It’s not Watsonian or Skinnerian, they found out very, very early relationships mattered and that family systems model I think works well.

Bruce: 47:44

And the other is the care model. And, uh, the care model is the out of cornell, out of the uh, uri bronford brother center, and the care model is what fit, uh, what we were doing at black mountain, and so, uh, we adopted that and became one of the care model programs and I think they do a wonderful job. I think they have a very sophisticated theory that combines James Anglin’s work, attachment theory, vygotsky’s work, and they do it in a very sophisticated way and I think that it’s had a power, powerful, positive effect on residential care all around the world, including in australia.

Colby: 48:26

Yeah, yeah, what you were saying there put me in in mind very recent guests, which was, uh, dr laura stickley, who, um you, you would, you would know, who in fact put us together in contact with each other.

Colby: 48:44

And, yeah, she talked about exactly the same thing that when you interview alumni of residential care, more often than not they’ll say that they have a positive opinion of it, and even if they’ve also been in foster care, they’ll report comparatively more positively about their residential care experiences.

Colby: 49:08

It would have to be said, though, that that data may be influenced by the circumstances in which they left foster care and went into residential care, and I think this is it’s that, it’s that level of and I think this is probably what you were, you, you have were saying about just be aware of basic research methodology, and and you had that early in your, you have that early in your book which is that we, we, we need to, to be, we need to be able to critically appraise the research. That um and not not everyone can do that, and that’s why I guess it it’s helpful to have people like you who can do that. To spell it out, um for people, but, um, you know even just what, what I just said, that you’ve got to, you know, understand the circumstance, or turn your mind to the circumstances under which a child might have left foster care to go into residential care, or young person.

Bruce: 50:08

Yeah, you’re really not talking about discrete effects. You’re not talking about what we would call discrete, independent variables. You’re talking about packages. It’s much like studying cultural differences when you’re comparing kids from one culture to another culture. You can’t identify something discrete about those two cultures because you’re dealing with packages. And that’s certainly the case in terms of residential care. And the other thing I think you have to be careful about is the quality issue, because that’s what comes back over and over again is as more important than the site of the care is the quality of the care, and kids can have bad care in every single different situation, and what we need to do is make sure you’re assessing that quality of care is. Make sure you’re assessing that quality of care.

Colby: 51:02

Yeah, yeah, you’ve mentioned your book a number of times. You’ve mentioned I don’t mean that in a bad way, but you’ve mentioned it. It’s one of the reasons why I was really keen to speak to you. What can people expect to get out of reading uh, access and reading the book, and how? How do you think it would influence practice in this space?

Bruce: 51:30

uh, you know I I did not push the book for the first year and a half because the hardback version was ridiculously expensive.

Bruce: 51:38

So I didn’t suggest anybody buy it, and so now it’s in paperback and you can buy it on sale sometimes and it’s more reasonably priced. But I think some of the other things I’ve written in journal articles would get the message across, and I often just give references to open access articles because they can get the basics. James Anglin, who has had a big influence on me, and anybody who knows residential care knows James’ name, and James said that the main purpose for my book should be that anybody writing a grant proposal to get support for residential care should put it in the appendix, and that’s basically why I wrote it. I wrote it because I felt like those who do residential care, those who see it as having a positive impact, were getting a bad press and I wanted to clear that up. And so you know, I think the major purpose of the book was to make that point. Now I do think that and this happened to me when I talked I was giving in Calgary, canada, last year a young woman came up to me and had actually bought the expensive hardback and she said that she she had, she was running a program there in Canada and she said what she had picked up from the book and which I was delighted to hear, was a better idea about what quality care is, and I think if people can can read that book and take that away.

Bruce: 53:21

I’m delighted because I think that’s such an important issue. It is the issue, the issue of providing quality care, and I think the reason you know, I don’t think there’s a mystery here. I think the research shows what high quality care is. It’s a matter of picking the people who are going to provide it carefully. It’s a matter of training them carefully, it’s a matter of supporting them carefully, providing the resources they need and the kids need, and then providing that stability. And I think that if you do that, you can provide quality care. Now it’s easy to provide bad quality care. There’s so many different ways of doing it and you do have to go into it. I think, thinking that this is an expensive form of care. And I say in the book, in the conclusion of the book, one of my conclusions is that residential care is expensive and it should be. We owe it to these kids. Society has not supported these kids well up to now and we’re going to pay for it and we should pay for it.

Colby: 54:30

I think that’s a really good point and it puts me in mind of an earlier guest who came into residential care from economics and who was very interested in human capital, the notions of human capital Graham Kerridge was his name, if you wanted to look back and I think that residential care done well, I think that residential care done well, just as is the case with other forms of out-of-home care, is an investment not only in the future of that young person, but their children and their children’s children. That’s right, and I do think that when you view residential care as an option of last resort, I wonder whether you know, like I wonder, whether a certain amount of that argument comes from the funders. Because of the cost yes, because of the cost they don’t want kids to be in residential care.

Bruce: 55:37

It’s bad for them, which also confounded with with the fact that it is also expensive yeah, there’s no question about that, that that happens, and and I think that, um, one of the reasons they get legislators on board for, uh, pulling the support from residential care is exactly that. And they said you know, it’s cheaper to keep kids in families. Well, no kidding. But the question is what’s the long term impact and what’s it going to cost society in the long term if we’re not careful? One of the things that’s happened because of the last resort thinking is that and the lack of foster care placements is there’s some strong stress on keeping kids in their families of origin, sometimes to the point where that’s dangerous.

Bruce: 56:34

And they’re doing it in situations where that’s dangerous. So there’s a writer, Naomi Riley, who writes about this regularly and what she’s pointed out is that when you increase the number of kids who are going back to their families of origin, abuse and deaths go up. Yeah.

Colby: 56:54

Well, that’s sobering.

Colby: 56:57

As a practitioner myself for 30 years working in child protection and related endeavor, one of the one of the the challenges that practitioners like me have is is that the state is a is a relatively poor carer and it’s a bit of a case of out of the frying pan into the fire for a lot of our young people, unfortunately, and I think you know, our legislators and our services have got a big job ahead of them to address the quality this, the quality of, of all forms of out of home care I mean state care, or the care if you’re in the care of the state. That should be a haven, that should be a sanctuary for the children that should be a safe place to grow up and too often we owe that to them yeah, yeah, have you ever said

Bruce: 57:58

that no, you go well, I, I think you know the foster, foster parent situation is we we don’t give, typically, we do not give nearly enough support to foster parents. Um and and if, if you’re serious about making uh, foster care work, we’ve got to do a better job of supporting foster parents.

Colby: 58:19

Yeah yeah, yeah, bruce, it looks like the sun’s going down where you are, the it’s getting darker and darker. It’s getting dark. You’re right. I don’t know if you wanted to pause for a moment and put a light on I can put, I can put a light on does that help? That’s different. We’ll wait for that. There you go.

Bruce: 58:45

Now the camera is focusing in on you again well, I I was going to do this outside on my, on my deck, overlooking the mountains, but, uh, they were predicting, uh, um, thunderstorms, so I I decided to go inside.

Colby: 58:57

I I well, we talked last time. You, I think you were out on the deck.

Bruce: 59:02

Oh was I.

Colby: 59:02

Yeah, there were thunderstorms predicted then too. You were in a very stormy place, it seems. Yes, yeah, I can predict that, on the basis of N equals 2. Both times I’ve spoken to you.

Bruce: 59:13

Well, we live in what’s known as a temperate rainforest.

Colby: 59:18

Yes.

Bruce: 59:18

And we are in the wettest portion of the United States east of the Mississippi.

Colby: 59:24

Wow, yeah, yeah, well, there you go. Well, there you go. I mean, my prediction was true based on a sample there you go. Sometimes it works. Bruce, if you were sitting down in front of legislators, what would you say to them about residential care?

Bruce: 59:42

in a nutshell, Well, we’ve talked about some of the things I would say to them. In fact, I have written to to as a written witness, to a number of of legislative groups and what I, what I say, is good residential care needs to be available and it needs to be an option, and not an option of last resort, but an option that takes into consideration the child’s needs. And one of the problems we’ve had in the United States and I’ve told legislators this over and over again they use the term family first and I think that’s wrong. I think the Danes have it correct. In Denmark, they don’t say family first, they say children first.

Colby: 1:00:32

And.

Bruce: 1:00:32

I think that’s the attitude that we need to take, and so what we need to do to have children thrive. They’re the ones that don’t have the power, they’re the ones that don’t have the voice, they’re the ones that get pushed around, and when you say family first, and what you really mean is parents, adults first, that’s not a good approach.

Colby: 1:00:55

No, no, yeah, finally, I’ve asked you a lot of questions, bruce. Was there anything that you’d like to ask me before we wrap up?

Bruce: 1:01:06

yeah, um, um. Australia was a place a few years ago that said we’re going to do away with all residential care. That’s the dream, and the dream’s been realized, and then things seem to have turned around pretty quickly. What’s your take on what happened?

Colby: 1:01:27

Well, I can’t really speak authoritatively for what’s happened in other states of South Australia. I’m in South Australia. We had what’s called a Royal Commission in our political environment, which is based on the British one, a Royal Commission and I’m probably not going to give a great description of it, but it’s like a very high level judicial inquiry into an issue. It’s called by the government of the day, it tends to take a period of time and it’s an investigation of an issue of great importance to the body politic, and then recommendations are made and it’s usually around things that have gone wrong. We had one in relation to child protection systems and an outcome of that was that, well, one of the things that flowed on from that was there was this idea reinforced that residential care is inherently bad, excuse me. And so we did have congregate residential care units. They’ve been closed down. Residential care units they’ve been closed down. I think almost all of them have been closed down, at least the state-run ones.

Colby: 1:02:48

And there was pressure in the last few years to move children out of residential care arrangements and, in particular, temporary residential care arrangements, which they were referred to as emergency care.

Colby: 1:03:05

And there remains this um, this idea that that residential care is bad and and that we should have all children out of residential care. And indeed our minister, or her staff has, has, you know, talks in posts on social media about we funded this program or that program and we saved children from residential care. I can’t quote you the figures, but residential care hasn’t gone away, and though the state or the government-run child protection agency tried to divest itself of residential care to independent providers, they have ended up having to maintain their own residential care program. I don’t know if it’s expanding or static. I don’t know if it’s expanding or static, I just know that it’s not been successfully gotten rid of. And I think you won’t. You won’t, and I think there’s very good reasons, as we’ve outlined in this conversation, for why residential care needs to be part of the picture. So it’s almost like the tail wagging the dog, in a way.

Bruce: 1:04:23

Yeah, yeah.

Colby: 1:04:28

The need is right in front of people’s faces. There needs to be this option. You can’t get rid of it. What you, rather, should be focused on is how do you make it better? How do you improve?

Bruce: 1:04:44

it. Quality is the issue. Quality of care is what it’s all about. I know that the people at Cornell in the care model have spent a lot of time in Australia and a lot of Australian programs have adopted the care model and I think that’s a real positive outcome because I think if you really do take the care model seriously, you can provide high quality care. Yeah, yeah.

Colby: 1:05:22

Well, Bruce, it’s been a real privilege to be able to have tracked you down and had this conversation.

Bruce: 1:05:27

Well, I have a low social media presence and that’s intentional, but I’m not hiding from anybody I know.

Colby: 1:05:34

But look to be honest. Last weekend it’s Father’s Day here tomorrow, tomorrow, sunday’s Father’s Day here tomorrow. Tomorrow, sunday, it’s Friday here, but one of my sons is going away tomorrow. So we celebrated. Last weekend. I barely picked up my phone and looked at social media and, gee, it was nice to do that. But thank you for taking the time to speak with us.

Bruce: 1:06:00

I’ve enjoyed talking with you. It’s been a fun conversation, awesome, thank you.

Reimagining Children’s Homes: From Last Resort to Purposeful Healing, with Kevin Gallagher

Not Forever Homes, But Forever Impact

In this insightful episode of the Secure Start podcast, host Colby Pearce engages in a profound conversation with Dr. Kevin Gallagher, a veteran practitioner with nearly 30 years of experience in UK residential care. Their discussion delves into the evolving landscape of residential care, its purpose, and how it can be optimally utilised to support vulnerable young people.

Kevin’s journey into residential care began in his mid-twenties, following personal struggles with identity and finding his authentic self. His early experiences of inequality and exclusion fostered a deep desire to help others, eventually leading him to social work training in the late 1990s. This personal healing journey coupled with professional development highlights how many practitioners in helping professions bring their own lived experiences to their work – what Kevin refers to as the “wounded healer” phenomenon.

What stands out in Kevin’s narrative is the evolution of his practice from an intuitive, heart-driven approach to one that balances authentic connection with evidence-based methodology. In his early career, his approach centred around providing “good parenting” – ensuring children had bedtime stories, proper meals, and a well-maintained environment. While well-intentioned, he acknowledges this approach was “crude and naive” without the underpinning theory to support it. This honest reflection demonstrates the importance of continuous professional development in the residential care sector.

A pivotal aspect of the conversation revolves around the purpose of residential care. Kevin makes a statement that might initially seem controversial: “These are not forever homes.” However, he clarifies that this doesn’t mean these environments should be cold or unfeeling. Rather, it speaks to the purposeful, time-limited nature of therapeutic residential care. The goal is to provide young people with healing, skills, and relationships that enable them to flourish within the parameters of their stay, ultimately preparing them to navigate life more successfully when they move on.

The podcast challenges the prevailing narrative of residential care as an “option of last resort.” Kevin questions why, after a second failed family placement, the conversation doesn’t shift towards trying something different rather than attempting several more family placements. This cycle of placement breakdowns creates additional trauma through repeated rejection. He suggests that in some cases, residential care could be used earlier and more purposefully to do the necessary therapeutic work that would eventually enable young people to successfully transition to family settings.

Kevin also addresses the heterogeneity of residential care, emphasising that just as no two families are the same, no two residential care settings are identical. He describes how his current organisation, Amberleigh Care, operates psychodynamic group therapeutic communities for teenage boys – a model that wouldn’t be suitable for all young people. Meanwhile, other organisations like The Mulberry Bush School use similar therapeutic frameworks but adapt their methodologies for younger children. This diversity is essential for meeting the varied needs of traumatised young people.

The financial aspects of residential care receive thoughtful consideration as well. Kevin makes an important distinction between “high cost” and “expensive” – residential care is undeniably high cost due to the resources required, but it should only be considered expensive if it doesn’t provide value for money. This nuanced perspective challenges simplistic financial comparisons between residential and foster care.

As our care systems continue to face increasing demands with diminishing resources, Kevin’s insights provide valuable guidance for how we might reimagine residential care. His decades of experience suggest that when used purposefully and therapeutically, residential care can be a powerful intervention that changes young lives for the better. The key lies in being intentional, responsive to changing needs, and guided by both heart and evidence-based practice.

You can listen to the podcast here:

You can watch the podcast here:

About Kevin:

Kevin is a qualified social worker, organisational consultant, manager and has just completed his PhD. 

He has worked in residential care and education for almost 30 years (with Amberleigh since 2015), from front line practitioner, through management roles and into leadership in a diverse range of organisational structures, both public and private. 

Kevins passion is for therapeutic residential care and education, promoting the use of quality improvement standards. 

He is an Advisory Group member and Therapeutic Care Specialist at the Royal College of Psychiatrists. 

Kevin has been a trustee of The Consortium for Therapeutic Communities for over a decade, supporting and developing therapeutic practice across the UK, in particular, supporting local authorities to commission specialist provision. 

Additionally, Kevin assists providers in strengthening models and practice. 

Kevin is a very public campaigner for better understanding and use of residential care through a focus on practice evidence.

Related Podcasts:

Listen here:

Watch here:

Listen here:

Watch here:

Transcript:

Colby: 0:00

Welcome to the Secure Start podcast.

Kevin: 0:04

When the second family placement has failed? Where is the conversation that says maybe we should be trying something different rather than carrying on trying another three or four or five? You know you’d like to think that residential care would be used earlier and more purposefully to do the work in order to allow young people to move into family type settings successfully. Therapeutic care as opposed to any other descriptor, it needs to be purposeful, it needs to be deliberate. These are not forever homes. It’s not forever, but whilst they’re with us, it is their home.

Kevin: 0:50

We need to be clear on what are we doing. Why are we doing it? How are we keeping it responsive? How is it responding to changing needs? This idea about them not being forever homes there’s nothing in my mind. There is nothing cold and feeling about that which would be the kind of criticism, and quite the opposite. It’s a much more responsible approach to say how can we make sure that these young people feel loved and welcomed and protected and encouraged and enabled to flourish and given all the opportunities they can within the parameters of the time we’ve got?

Colby: 1:32

Welcome to the Secure Start podcast. I’m Colby Pearce, and joining me for this episode is a highly experienced practitioner and leader in the UK residential care community. Before I introduce my guest, I’d just like to acknowledge the traditional custodians of the lands that I come to you from, the Kaurna people of the Adelaide Plains, and acknowledge the continuing connection the living Kaurna people feel to land, waters, culture and community. I’d also like to pay my respects to their elders, past, present and emerging. My guest this episode is Dr Kevin Gallagher.

Colby: 2:19

Kevin is a qualified social worker, organisational consultant manager and has just completed his PhD. He has worked in residential care and education for almost 30 years the past 10 years with Amberley Care, from frontline practitioner through management roles and into leadership in a diverse range of organisational structures, both public and private. Kevin’s passion is for therapeutic residential care and education, promoting the use of quality improvement standards. He is an advisory group member and therapeutic care specialist at the Royal College of Psychiatrists. Kevin has been a trustee of the Consortium for Therapeutic Communities for over a decade, supporting and developing therapeutic practice across the UK, in particular, supporting local authorities to commission specialist provisions. Additionally, kevin assists providers in strengthening models and practice. He is very public as a campaigner for better understanding and use of residential care through a focus on practice evidence. Welcome, kevin.

Kevin: 3:49

Hi, colby, it’s great to spend some time with you and thank you for that very generous introduction. I feel like I need to, you know, add some personal bits to it. I’m a Gemini, I don’t like football, I’m no good at DIY, and we’re picking up a new puppy tomorrow.

Colby: 4:04

Oh really, I’m no good at DIY and we’re picking up a new puppy tomorrow.

Kevin: 4:06

So I think that just it kind of rounds off a long list of work-related activities. But it’s great to be with you and I’m delighted to have been invited. Thank you.

Colby: 4:15

Well, and thank you for agreeing to come on. I’m not sure when which month covers Gemini. Yeah, we’re a little bit different. I don’t mind the football and building things. In fact, I’ve spent much of today doing renovation work here at my house, but we obviously both have an affection for dogs. There you go. What sort of puppy are you getting?

Kevin: 4:42

tomorrow. So we’re getting an Irish Terrier puppy tomorrow. Oh yeah, yeah, yeah. So that last dog of 16 years sadly passed away about a year ago. So we’ve got the summer holidays out of the way, so that we’re now ready to have a new addition to our home, and actually we’ll be registered as a therapy dog as well, so I can bring him into work with the children yeah, I look, I’m a I’m a massive dog person.

Colby: 5:10

I love dogs, my mine. Last month was two years since our maltese cross poodle passed um and uh. I’d like to tell the story about the, the variation in in uh, the dogs that rebecca and I, about the variation in the dogs that Rebecca and I have had in the course of our marriage. So our first dog early in our marriage was an Alaskan Malamute, and so a very big dog, very big, very strong, shedded a lot. And then we went from there to a Maltese Cross Poodle, or a Moodle as they call them here, and they both used to sleep in our bed. He was small enough to sleep on his daddy’s chest, a bit like the Bubbies did when they were small. So, yeah, dogs really enrich our lives. I wish I could get another one, but my sons feel my pain, and so one of them’s already. He moved out earlier this year into his own house and very closely after that, bought himself a golden retriever puppy.

Kevin: 6:21

Dogs have always been part of my life and actually even at work we have dogs and animals of various descriptions in our two settings. I might talk a little bit about later. But I think that kind of the impact of having dogs around or having animals around and needing to care for them, as well as the kind of the distraction and shared experience that you can have with staff, I mean, yeah, I think it’s. It enriches our lives to have animals around.

Colby: 6:46

And I think there is definitely an evidence base that is emerging around the role that pets slash animals play for the benefits around mental health and wellbeing and the developmental benefits for children and young people as they’re growing up having pets to care for. So, yeah, that’s great. Was there anything else that you wanted to add to the bio that I read before, or just the personal addition was sufficient.

Kevin: 7:25

No, it’s an honour to be invited and I think when you kind of read it out, when you’re in and doing the work, and then the years go by and you learn and your role changes and now I find myself 30 years in being invited to have conversations like this, which is a real privilege. So it’s always useful to be able to reflect on the journey and the different roles and how it’s evolved and how that informs how I practice and you know the views I have around child care, how we run the services, how we campaign. So I think it’s a yeah, it’s a useful starting point in terms of the conversation this morning.

Colby: 8:04

Yeah, yeah, and of course the privilege is also mine as well, having you on, so tell us about how you got involved in residential care.

Kevin: 8:15

I mean, I think, like a lot of people in helping professions, there’s a degree of wounded healer in in the background. I sort of fell into it in my in my mid-20s. I kind of left school at 16 with qualifications. There wasn’t a, there wasn’t an encouragement in my house to kind of work, um, and struggling with my identity as a gay man. I hadn’t come out at that point and I found myself with a house and a girlfriend and a job and responsibilities and living a life that really wasn’t um, authentic um, and there was a kind of a hidden side and the tension and the pressure of managing that culminated in me coming out and having some quite a lot of difficulties during my late teens and early 20s, you know, become a little bit extremely strange for my family for a while. A bit of running with the pack, mixing with some of the wrong crowd, too much partying, um, you know those those sorts of issues, and I was kind of finding myself um and I wasn’t happy during that period. Uh, and then, um, as I began to settle into myself a little bit more, um, I actually went back to night school as it was then, and did my sociology and psychology a levels, um as a stepping stone towards social work. I think the my experiences of being a gay man and coming out and growing up during the the 80s I was born in 69, so um, the kind of the environment, um in the, in the culture at the time around, homosexuality was still um very negative um, and even my first experiences of coming out on on the gay scene there were a handful of quite clandestine venues that you would go to and a real melting pot of people in there in terms of ages and interests and so on and so forth. It’s not like it is today and I think I was very aware of inequality, unfairness, feeling excluded. Some of these thoughts were not properly worked through because I was living them and experiencing them as a young man and that definitely informed a motivation to want to help others. I’d always found that I was fairly gregarious, quite confident in, at least on the surface, quite confident in social situations, and when I left school I ended up working in banking and sales, so a very kind of talking, interacting type profession, and I think that and then this combination of social values and wanting to help people I didn’t recognize it at the time, but some of that was also my own healing that. That took me towards social work training.

Kevin: 11:37

So I did my social work training in the late 90s and that was the beginning of a sort of a turning point in my personal life. I can kind of come out of a difficult period and then now had more of a purpose of where I was going. I’d come out, my family had had some time to adjust to that. The fact that I was now training and on a career path was, you know, was helpful in rebuilding my relationship with my family and so it moved on from there. And then usually at the time when I did my social work training it was a diploma in social work. It’s now a degree in the UK, so it was a two year diploma with quite extensive placements as part of the learning.

Kevin: 12:28

And I did my second year placement, partly attached to um uh, an adult um, mental health hospital, um and partly with a leaving care team, um, working with young people transitioning, and that was the beginning of my hook into working with young people. So when I qualified, everybody else on my course there were about 20 odd of us. Most of them were doing children and family social work or adult social work and wanting to go and work in statutory teams, but I went to work in residential care straight away in the local authority. So even that was quite unusual at the time. So I found myself in a small local authority children’s home in the West Midlands in a very kind of urban setting, working with quite diverse, challenging young people. If I look back on it now, there was no deliberate use of residential care. You know this was a unit, as the language would have been called then, and we were working with whichever young people the senior management in social services were sending through to us.

Kevin: 13:50

And it happened that we were working with a very complicated young person who displayed sexualised behaviours as part of his kind of profile and we were engaging with an independent sector organization that were actually coming out to do some assessment to see whether he would be a suitable match for their service. And I was involved in that and although, as it turned out, that wasn’t the right route for that young person, I made a connection with that service that ultimately then turned into a job offer at a later point. But I found myself fairly quickly as the only qualified member of staff in a mixed staff group and within a few months of being there the registered manager had an accident that injured his back and put him out of work for several months. And as the only qualified member of staff I was asked to step up and hold the team, even though I was newly qualified and really wet behind the ears. So I found myself learning on the job very quickly and that was my springboard then into the, the independent sector and moving into a management role after about two years in the local authority and it moved from there. So I started as a residential social worker um managing a really tiny service initially, then moving into a six bed service for under 12s all boys and that was my first taste of working with therapists. That service used to buy in its therapeutic services from another established provider and, yeah, that was where I cut my teeth. I was in that organization for five years as that organization grew. So I started as a manager of one home, um, and then after about a year I moved into a middle management role and then was overseeing the opening of more homes and that’s when I really, you know, got my my feet into personnel management and staff training and understanding some of the policies and, um, you know the regulatory frameworks in more detail, and it basically moved on, moved on from there, um. So so, yeah, it’s definitely rooted in personal experience. There was definitely a motivation to want to help others.

Kevin: 16:25

When I look back now at my knowledge back then was wafer thin, really wafer thin? I mean a lot of the judgments were quite crude and naive. I mean I remember a phase I mean this would have been, you know, way back at the very end of the 90s, and my thinking was very much about good parenting. It was quite sort of middle class, sharp, elbowed parent type, thinking about manners and looking after our environment and making sure there were bedtime stories and that the house was well maintained and there was abundant food on the table, and so I didn’t have any of the underpinning theory to go with that. It was just based on this kind of strong sense of good parenting to try and make up for what had been missed. Um, you know, reflecting back on it now, it feels very crude, it feels very, very naive, and I certainly remember at one point, you know, three or four years in um, I was very much on my white charger, trying to rescue everybody and trying to lead from the front, and that was definitely my achilles heel.

Kevin: 17:45

I remember one, one period where you know the degree of trauma again, I’ll use the language that I understand now things were uncontained. Um, I wasn’t recognizing the need to contain the staff, to contain the children. I was trying to do all of that myself and you couldn’t fill your own cup quick enough to be able to feed everybody else. So, yeah, there were definite moments where I think I was very fortunate. In the first kind of four or five roles that I had, I had really solid, experienced practitioners as my immediate line manager or mentor, and so those four or five people really. They kind of gave me confidence and support to kind of do what I was good at, but they also kind of challenged and signposted me on the areas where I needed to grow and develop and that, yeah, that put me in really good stead.

Colby: 18:50

People seem to find their way into this area. That kind of need to find their way into this area.

Kevin: 18:57

It’s strange work really, isn’t it? I mean, when I talk to people about over the years and I’ve talked to kind of friends or people that you meet who are outside this work, and people will often say, oh well, it must be so rewarding, or well, I couldn’t do what you do. And it is a strange, it is a very strange situation. I mean even thinking specifically about the idea of a children’s home. Specifically about the idea of a children’s home. You know it’s a place of work for the staff who are coming in, but then it’s a relational and very kind of familial and domestic set-up, but then the young people who are there are not really there by choice. It’s a very odd situation to be in by design.

Kevin: 19:48

And then, in terms of the nature of that kind of relational work, um, you know, I often talk about to staff as well, about you. You need to be open and affected and bothered enough, um, to actually have real connections. You know that you’ve got. You’ve got. You’ve got to feel and want and want to know and want to be with these young people. But, by the same token, you also have to be slightly detached and aloof enough if aloof is the right word, detached enough to be able to think and and see things objectively and be able to apply yourself deliberately, and I suppose that’s the the point.

Kevin: 20:39

I was the thing I was talking about earlier. I suppose that’s the point of distinction. When I was earlier in my career I I wouldn’t have been able to describe it like that because I was driving very much just from the kind of internal um wants and motivations and the kind of internal my own internal working model of how I thought the world works, um, but now I’m able to kind of harness the good part of that but also balance that with something that’s a bit more structured and a bit more evidence-based and informed. You know that the thinking has a much more concrete underpinning now rather than it just being from the just from the heart. You know, you need that.

Colby: 21:26

I mean, I think the word that comes to mind is sophistication Like the approach has become more sophisticated as you’ve had opportunity to reflect on the role that you’ve been performing and delivering over the years. I did think. I must say I did think when you were talking about your initial approach and it being a family by from what I heard, a conventional family trying to provide a conventional family environment, and feel I think, you know, I think that there’s nothing terrible about that. In fact, if we can do that for our young people and provide them with some of those conventional family experiences or relational experiences, I think they’re the foundations.

Colby: 22:26

They’re good foundations to build on.

Kevin: 22:30

Yeah, I suppose at the time I would say it’s yes, and, and at the time I didn’t have the, and I think that’s the thing that I’ve learned. And I think that bit about heart and head and, you know, being authentic and being connected but not but able to um, stay contained and not be overwhelmed and flooded, I think there’s also a parallel when we think about um staff teams because, again, you know, residential settings are an unusual environment with multiple relationships, um, they’re familial and domestic, but then they’re not, in terms of the shape of them, that difference in age and gender and personality type that you have within staff teams. You know, there are some that will be much more thinkers and want the theory and the evidence base and the knowledge and use that as their way in to kind of inform their practice. And then there are others who just seem to be innately able to connect but might equally then struggle with report writing and paperwork. And so this thing about moulding a team and being able to recognise that you need all of those different talents, sometimes they’re contained within individual people, um, sometimes they’re absolutely contained within different people within the team. Um, and I think, again, that’s another thing that over the years I, you know, I’ve been able to have a much deeper understanding of in terms of how you support and shape and develop a team. It’s definitely become more. You know my thoughts around that become more strengthened as I’ve got more and more into therapeutic communities. I mean my therapeutic community interest. That absolutely came by accident.

Kevin: 24:25

20 years ago I took on a director role for an organisation that had 27 small, very small children’s homes spread across North Wales and Shropshire with a couple of small schools that they were servicing, and it had been through some operational difficulties. There was some really great practice happening in pockets and there were some areas where things were chaotic and not good. Um and I can’t take the credit a predecessor in the role had come across these therapeutic service standards and had literally just got them and started an initial email conversation and it had never gone anywhere. So these were sort of almost in the inbox when I arrived and I was looking for some kind of framework to help bring these 27 homes together, some kind of common language or set of principles so that I could start to share what was working well with services that were perhaps struggling and kind of, you know, coordinate it really.

Kevin: 25:34

And the therapeutic community standards were what I discovered and it was like a light bulb moment. I mean, they were to me, they were an off the shelf-to systemic framework that gave a language that we could use consistently. That then, as you got into the detail, talked about some of the how-tos in terms of systems and processes and, yeah, that was my starting point and I’ve worked with those standards, um, in deeper and deeper ways. Uh, ever since it’s, that’s become a complete um, uh, yeah, complete turning point in my, in my kind of practicing and career.

Colby: 26:22

Yeah, yeah, uh. Peter wilson, a very recent guest, said his life has been a series of serendipities. You referred before to you had some mentors that you had when you were getting into the work and I really wanted to ask you, when you mentioned them, what it was that you took from those mentors that helped you in your own practice and career progression um.

Kevin: 26:54

So I think, in in my very first step into, uh, into the independent sector. So when I, after about 18 months, two years of working in the local authority, um, so in the uk, as, as people may know, um, we most children’s services in the UK now are delivered by the independent sector. Most of that is private sector. There’s a small amount of third sector provision and public sector provision has been very, very low for a long period of time and when I was first joining the profession it was right at the beginning of that journey. So the independent sector was relatively new. It was probably a decade. We’ve been around for about a decade but it was growing, growing, growing. So my career has been lived through the experience of public sector shutting everything and a new market of private provision and how that market has evolved and matured, which we can talk about later. So in that very early stage I was working with two experienced local authority child protection social workers who were and this this was very common in terms of how those early services were set up it was predominantly experienced local authority practitioners who were, you know, disappointed or frustrated with the way that services were organized, who decided to go out and set up on their own to do things differently. And so I worked with these two guys who were, um very well established in their own reputations. They knew what they were doing. The service was, you know, solid in terms of um its understanding. You know it wasn’t yes, it was a for-profit organization, but back in those early days this wasn’t set up as a money-making venture. That wasn’t the, that wasn’t the kind of way it was positioned. This was like new innovation. So being around them and having their support was, um just very reinforcing in those early days. And then I moved to um a larger organization. I took a sort of immediate middle, sort of middle senior management role in a larger organization that was already working therapeutically in different ways, and I had a there was a female managing director there, again very, very long in the tooth established local authority child protection social worker who’d been managing these services for a number of years and had that mix of the kind of operational leadership in a space where the services are being purchased by local authorities but still needing then to operate, from a practice perspective, quite a diverse portfolio of different provisions. Um. So again, there was a bit of troubleshooting to be done there, um, so it was good experience and she was um, as I touched on earlier. She was somebody who appreciated what I was able to do and gave me space to just crack on with it but was an absolutely amazing backstop and mentor. So in terms of if I was hesitant about something, that sounding board, but it really felt like a peer relationship rather than it being a line management relationship, it felt very kind of creative and that then was a stepping stone then into the organisation.

Kevin: 30:37

I think a mutual colleague, patrick Tomlinson. I joined SACS so there was a bit of full circle there. So SACS was a very, very reputable therapeutic childcare organisation in Shropshire in the Midlands and the first independent sector role that I had where there was the bought-in therapy, the bought-in therapy was being provided by SACS. So I began to have a sort of an awareness and a working relationship with them and three or four years later I then joined as a director when that organization was expanding and that was one of the most significant periods in my kind of, you know, middle part of my career, the the expertise. There was a lot of commitment in that organization to really developing the evidence base of what they were doing. They developed a body of work. They had a very clear treatment and intervention and assessment process. The systems were very structured. The people that they had had recruited into that kind of senior team.

Kevin: 31:46

There was a lot of thinking going on. They were writing, you know, publishing articles um, supporting the writing of books, um, it was. Yeah, it was a really fertile um period in terms of being exposed to thinking. I mean, that’s when I started to get more exposed to psychodynamic thinking. First came across the Tavistock. It’s through that organisation that I uh, alongside that, as part of that kind of reflective work, which was not something that I’d done earlier in my life, um, so it was a. It was really interesting to come at personal therapy under the auspices of a work and a qualification, um, but it was. It was really that point where I properly got to understand that you’re using yourself in the work, um, in a very explicit. My understanding became much more explicit, um, and then my understanding of the theoretical underpinnings of that and what that looked like in terms of organisational structures and systems and the idea of anxiety in organisations and containment and how that pertains to leadership. All of those ideas absolutely came through my time at SACS and that and that qualification. Yeah, there was said there were several, several very influential colleagues there and they were also an organization that was very outward facing and networking with other practitioners. So it certainly laid the foundations. It gave me introductions and contacts with other people and into the other networks that I’m still very much in contact with today, 20 years on. So that was definitely very, very significant. And I think the other person I would say would be very significant for very different reasons Before I came to Amberley so I’ve been at Amberley now for 10 years.

Kevin: 34:08

But after I finished that consultation qualification, I uh I started to do some individual consultation work to make it live, you know, to make it a real, a real thing. And uh, I used to, I used to meet up regularly with other providers in our part of the country, kind of networking groups, and the original owner and founder of Amberley was somebody that I used to see regularly in these spaces and we got on well and she needed some role, consultation, because she was a director, a registered manager, a responsible individual, you know she was wearing a lot of hats in quite a small organisation and needed some thinking space, some kind of coaching and thinking space, and that relationship was ongoing for six and a half years, providing that supervision and doing. I did some board strategy days and some team development days at various points and there’d always been a bit of a joke. I was running a much larger service as an employee, um, and there was always a bit of a joke about, oh, when you’re going to come and work for us so I can retire, you know, I could hand over to you, and that conversation became more serious in 2015. And so that’s how I joined Amberley. So Amberley has been around for 20 years and I’ve been connected with the service for almost 17 of those, but employed in the leadership role for the last 10.

Kevin: 35:46

So that relationship with that particular woman uh, you know that that founder um was a, you know provided me with the opportunity that I, that I have today.

Kevin: 35:58

I wouldn’t be, I wouldn’t be in the role I mean now had I not had that, that working relationship. So it’s definitely significant, not always straightforward. I mean the idea. I mean that was a learning in itself, the idea of um, you know, helping to manage the transition of a founder, you know, leaving the thing that they have put their blood, sweat and tears into for a, for a decade, um, and that kind of handing over the service to somebody else, to kind of take it for a very complex process to have lived through, you know, not always easy and uh and learned a lot through that, but, um, but definitely a significant person, um, you know, I wouldn’t be here now without, without that opportunity, so I’m always mindful of that what’s become really uh clear in the expression of people who work in this space and in related endeavors is the role of supervision in, as you put it, providing some thinking space, that opportunity to reflect about the work, because if we’re not thinking about the work, then how are we practicing, is the question.

Colby: 37:11

You mentioned earlier the word containment quite a number of times and I was going to ask you about the kind of theories that particularly influence your practice. I’m very much of the view that the people who do well in this space, they can be quite a diverse group, but the one quality that I think really makes people stand out is that they’re good at containment. Yeah, some people are just naturally good containers, you know they’re just, they are, I think.

Kevin: 37:46

I think in terms of, um, I think there’s a responsibility to the children. And, if I was to use a slightly different perspective, these are paid for services, whether it’s delivered by the state or whether it’s delivered by a private sector organisation. It’s public sector money, it’s a state intervention when we’re looking after children. So I think there is a, I think there’s a moral and uh and an economic um, um responsibility. But to the children, um, they’re with us, not by choice, you know. They’re with us as a result of, you know, these significant early traumas and we owe it to them to work with them and alongside them in the best way that we possibly can.

Kevin: 38:41

And I think, in relation to therapeutic care, as opposed to any other descriptor and we may talk about that in a while it needs to be purposeful, it needs to be deliberate. So I think, the thing about the kind of the learning and the knowledge and what that might mean for containment, for people who are leading a shift if that’s the language that’s used or a registered manager or a senior manager we’ve got to understand the nature of the work on the ground and to play our role in the system to make sure that those young people and those staff are getting the maximum amount of support, relational opportunities and different inputs and supports to be able to, uh, help with healing and recovery. So so, yes, we, we could go along and do that in a very uninformed and just go with what’s natural, but loads of mistakes are going to be made and these young people deserve much better than that. So I think that’s, I think I think sophisticated. You know, having a more deliberate or sophisticated approach I think is absolutely essential, but then it’s a deliberate thing.

Colby: 40:22

Yes, it’s the intentional use of yourself, the intentional use of the self, and so there needs to be a guiding framework, um that so you, so that there is an understanding of the children, of the work of, of relate, the relational environment in which you’re working, so that, um, so that you can be intentional about it. And it needs to be the opportunity to stop and think about the work and how I approach it and use myself in a way that is reflective of good care standards and of the needs of the children.

Kevin: 41:10

I think it’s. What is the work? I mean children’s homes, you know I’ve spoken a little bit recently about which some people can find slightly controversial. These are not forever homes. These young people are coming to us at a point in their life where they need particular types of help. They’re only going to be with us for a relatively short period of time. Maybe that might be a couple of years or three or maybe a bit like, if we’re lucky. I mean, in the uk the average length of stay in residential care is getting shorter um, so it’s not forever, um, but whilst they’re with us it is their home, but it’s. It’s a special home where they’re there to get specific sorts of help from a diverse group of individuals.

Kevin: 42:05

So the purposefulness it’s. You know we can’t afford drift. We need to be clear on what are we doing, why are we doing it, how are we keeping it responsive? How is it responding to changing needs? I mean, I work with teenage boys and if they’re with us for three or four years, they’re growing up as young men, young adults. So their personalities evolve and are shaped by the people and the experiences that we provide. I mean that’s a. You know, I’m not a parent outside work and it’s interesting that I know I’ve spoken with, with family and colleagues along along the way. I think there is a there is a strong parenting motivation within me that gets satisfied through the nature of the work that I do.

Kevin: 42:54

Um, so, yeah, it’s strange when, when you know, when you have, like, a media presentation about children’s homes and and young people can then either be put into these polarised positions of being these poor victims that need to be looked after by the state, and if you start from that position, a whole load of assumptions can unfold or it’s a more demonised view about troublesome individuals that need to be managed away from society, and both of those positions are obviously unrealistic.

Kevin: 43:32

Um, but they, but they both then set up a set of assumptions at a societal level about what a children’s home is or what it’s for. Um, and, yeah, this idea about them not being forever homes. There’s nothing in my mind, there is nothing cold or unfeeling about that which would, which would be the kind of criticism, and quite the opposite, it’s a much more responsible um approach to say how can we make sure that these young people feel loved and welcomed and protected and encouraged and um enabled to flourish and given all the opportunities they can within the parameters of the time that we’ve got, with an understanding of their starting point when they arrive with us, with the application of theory and practice, so that by the time that they’re moving on they are healthier on all levels healthier, more rounded, more confident human beings to be able to go on and navigate life more successfully under their own steam. I mean, that’s the outcome from my perspective.

Colby: 44:46

I think yeah it’s not so controversial with me, kevin, I’ve been thinking a lot about the best way to use residential care, in a sense, because I do think it has strengths. It has really clear strengths in a number of areas. So, yeah, the idea is that we should be very much aware of those strengths and we should be very much aware of the populations of children and young people who can benefit from it. I’m interested to hear more about you know how you view residential care as, as compared with um, foster care, for example yeah, well, again across my career.

Kevin: 45:39

So again, this is where the understanding evolves over a career. So I now have a much more, a much clearer understanding of the um, the wider societal roles about um. You know economic policy for argument’s sake in a country and how that translates to the funding of services. So if we look in the in across my 30 years in the uk system, um, it’s moved from massive decline in public sector provision into the private sector and then that sector not very well managed, given that we’ve only got local authorities who are commissioning services. Then, if I look at the last 10 or 15 years in particular, because there are some extreme pressures in the UK, as there are in many systems, we’ve had 15 years of real cuts in public funding. So our local authorities, in terms of all of those early help, help for families, early intervention, youth clubs we had Sure Starts centers in the uk, a lot of these initiatives that were helping children and families to have the best start in life and ultimately reducing some of the numbers that would be coming into care they all got stripped away.

Kevin: 47:03

Um, at the same time we’re on a societal level. We’ve had real economic pressures, a more unstable labour market, a more unstable housing market, fuel pressures, et cetera, et cetera, et cetera. So all of the societal pressures that are going to drive demand into a kind of a looked after system have risen at the same time when a lot of those preventative and protective structures were being taken away. So it’s been a perfect storm. We’ve seen rise, rise, rise in terms of the numbers of of children and families coming into the system, um, and then it’s a bit of a crude analogy. But if, if we were to look at that a bit like a funnel in terms of, you know, greater numbers coming in um and greater complexity within that, where that kind of filters all the way through, um, you know you’re thinking we’ve now got a situation where about 90 percent of children who are in care are in foster-type settings in the UK, foster-type settings or sometimes kinship care, and about 10% in residential care.

Kevin: 48:18

But that line between, you know, the line between moving from fostering to residential care, has moved further down that funnel. So, you know, you’ve got young people who 20 years ago might have been in residential provision now absolutely in foster care, and a lot of that is driven by economics, not by practice, um, so fostering gets talked about like it’s a single thing, and of course it isn’t. It’s a spectrum of different types of provision. So we’ve got therapeutic foster placements and solo foster placements and you know those for siblings and so on and so forth. And then when you get to that point where you know if you’re a young person where the local authority is deciding that a family is not right for you, authority is deciding that a family is not right for you or quite often multiple foster families have been tried and failed and that and children need to go through that, sadly, before they’re able to start accessing the resources of residential care.

Colby: 49:22

That that’s um the line and distinction when that change is made has moved more and more as they kind of down that funnel, sorry, there’s something that you just said there that I want to just jump in on because I think it’s really important to hear more about and talk more about you. You mentioned that some it’s almost as if some children have to go through a succession of foster placements before they get they. They end up in residential care. Yeah, yeah, and and it can’t be really understated what the impact on the children is of those, those successive breakdowns in foster placements before they Multiple rejections yeah.

Colby: 50:12

And that also then feeds into this idea of residential care being an option of last resort, last resort, and I wonder what you thought of that. I wonder what you think about this idea of it being an option of last resort.

Kevin: 50:29

Yeah, I mean that’s been the kind of narrative in the background across pretty much the entirety of my career. You see it at policy level. I mean we just had in the UK a couple of years ago we had a big independent inquiry into children’s social care by Josh McAllister, who’s now an MP, kind of putting forward a number of reforms, and it was interesting in that in terms of who they spoke to and what the kind of narrative was guiding that kind of that kind of inquiry, because residential care was hardly even included in it. And you know, you look at it and think, well, yes, it’s a, it’s a relatively small part in terms of the numbers of young people, um, but they’re the young people who are the most diverse and they have the most, um, you know, complex lives in terms of competing needs and it’s also the highest cost interventions. It’s where the system is spending the most of its limited resources. And yeah, the whole narrative is almost about we don’t want it. I mean I get it.

Kevin: 51:47

When the Children Act was introduced, that kind of reinforced this idea of residential care as last resource.

Kevin: 51:53

And I I get it because you know, I absolutely subscribe the best place for a young person to grow is in their family or in a family setting where that’s possible.

Kevin: 52:04

Um, but the way our laws and our systems were created, it almost had a systems level thinking that was that’s what we should be focusing on at all costs.

Kevin: 52:22

And so, inevitably, residential care becomes, yeah, absolutely the end of the line. Care becomes, yeah, and absolutely the end of the line. So you end up with processes where children do need, you know, do end up having lots of failed placements and you kind of you sit there sometimes as a social worker and kind of think what, why is nobody, you know, in terms of the decision makers who were kind of managing this young person’s care planning, when the second family placement has failed? Where is the conversation that says maybe we should be trying something different rather than carrying on and trying another three or four or five? But then, you know, by the same token, I’m not in the position of sitting in those resource meetings where those local authorities are trying to manage. You know, you’d like to think that residential care would be used earlier and more purposefully to do the work in order to allow young people to move into family-type settings successfully.

Kevin: 53:41

And that definitely is what happens in some of the countries. I think some of the Scandinavian think some of the scandinavian models work like that, but their whole welfare system and how that’s funded is entirely different to a uk context. So we’ve had experiments in the uk when people have looked at um, you know, social pedagogy models from scandinavia or germany and tried to kind of bring them in and they haven’t really worked because the wider system around them isn’t geared up to embrace that way of working, because it’s like turning the UK system on its head and we’re not set up for that.

Colby: 54:21

It’s too culturally different, but it’s interesting. On this question of option of last resort and, by the way, I agree that there are compelling reasons for it to be the option of first resort, but the people who would keel over at their desks, of course, are the chief financial officers of the commissioning organisations, because you wonder whether it is expensive to do it. To do it compared to foster care, residential care, High cost.

Kevin: 54:58

Just to put it in language there I say you know, I make a distinction between something being high cost and something being expensive. High cost is realistic in terms of the amount of resource that needs to go in. I think something’s only expensive if you don’t get very much for your money, because there’s a conversation about the cost of things and about value for money and how you determine that. So they are absolutely high costs. There’s a sensitivity to that in the UK because we have examples of profiteering, which is something that’s become quite a you know, a political and a media element in the kind of wider narrative. That’s why my ears pricked in that language.

Colby: 55:43

Again, I think you raise a very, very good and very interesting point around and and that is around value for money and um, I want to get into talking to you, about talking with you a little bit about the heterogeneity of residential care, that it’s not all the same, just in the same way that not all families are the same and not all not all foster and and there and there seems to be a relentless pursuit to try and make and I’ve been part of it to try and make all care experiences as same as possible. But reality defies us. The reality is that there is always going to be diversity. But just getting back this idea of the option of last resort, but just getting back this idea of the option of last resort, I mean you do, I am turning my mind to whether that’s is it the option of last resort for financial reasons, or is it the option of last resort because it’s a lower standard of care?

Kevin: 56:49

No. What are your thoughts about?

Colby: 56:50

that.

Kevin: 56:51

Yeah, yeah, interesting point. I think the financial drive is very, very significant within that and, as I say, over an extended period of time when the financial imperatives for local authorities have changed in points, when they’re under dire cuts, that financial motivation becomes much more to the fore. But I think, before that, I think, going back to the comments I made about the Children Act, I think there’s something rooted in our systems thinking, in our cultural thoughts about, you know, what is the proper place for children to be brought up in, what is the environment? So this idea of the family and the family home and for children to grow up in that environment, and what we might think of as ideas of normality and childhood and so on and so forth, there’s something deeply ingrained at a cultural and systems level, and even in terms of our legislative framework. That means that we are prioritising family and in many instances I absolutely agree with that, you know, I completely agree with that. But I think that needs to be balanced with and, yes, and sometimes a family has been the place where trauma has been created to such an extent that that young person needs something different for a period of time, to such an extent that that young person needs something different for a period of time.

Kevin: 58:30

When we go back to kind of you know, thinkers and writers, somebody whose work is absolutely as relevant now as the day that it was written, adrian Ward, who was writing back in the 1980s about, you know, leadership and and residential care, and in relation to therapeutic care he was well, residential care. He was kind of saying, well, if it’s not therapeutic, what is it? And I think he was speaking to a point that I I certainly make loud and clear now when we look at the profile of need of young people who are being referred into residential services in the UK I’m sure this is true elsewhere. By definition, by default, those young people come with significant underpinning trauma needs in all kinds of ways that express themselves in all kinds of risks and behaviors. So so all residential care must surely be therapeutic and planned and purposeful. How can it be anything else, like I, given the nature of the task.

Kevin: 59:43

But then that’s where there’s a disconnect. When you look at the way that um, and there are some changes emerging in the UK, but broadly speaking for a long time, when you look at the way local authorities describe, specify, commission, purchase residential care, standard places and and and core provision and and somehow other things are then enhanced and bolted on, like the. There’s a, there’s a. There’s a difference in thinking um, and I think some of that is informed by procurement and commissioning language rather than about social work language. I think it’s two different mechanisms trying to talk about the same thing in the middle, um, but we are, we are definitely beginning to see some change there.

Kevin: 1:00:41

I think um and that goes back to this idea that you know, children’s homes need to come in all different shapes and sizes, both in terms of their locations, the size of the building. Are they going to be single gender or mixed gender? There are definitely different cohorts of needs for young people, some of which can be clustered together and overlap, some of which you need to work quite distinctly with, and a good example I give to bring that to light. I mean, we’re in amberley, we’re working, um, in a psychodynamic group therapeutic community. So it’s unusual, um, in the uk residential settings where we have up to 19 boys, uh, on one of our sites and one of our communities in two buildings and up to 13 boys in the other.

Kevin: 1:01:34

Now, most children’s homes in the UK are two or three, maybe four places, so they’re unusual in their size and we work with a very specific cohort of young people. So we’re very clear who we don’t work with, our environment and that operating model of using the power of a group and using relational practice in that context would not work for certain types of risk profile um. And yet we’ve got the mulberry bush school, which is a very, very long established, you know well-renowned therapeutic community. So they operate to the same set of therapeutic standards that we do, but they have. They’re working with primary age children whereas I’m working with teenagers, and they have a campus model of five small homes around a school, all on one site. Now, same set of standards, same psychodynamic thinking, a lot of the same structures and practices, but the but the way that is delivered in the day-to-day um and some of the kind of the theories and structures, like their approach to assessment, for example, and intervention is rooted in the needs of younger children. So it’s a way of having the same framework of practice in terms of governance, but the methodology that you’re then hanging on to that framework is bespoke to the nature of the children that you’re working with, and I think that speaks to this idea that we need diversity of provision.

Kevin: 1:03:17

You can have some standard frameworks to help create some common language, but that allows local authorities when they’re more confident in engaging with that. It allows local authorities to be able to make more of a comparison between apples and pears, because if they think that residential care is all the same and they’re presented with a plethora of models and descriptions and acronyms and the reality is, is that some of those are robust, some of those are well-meaning but maybe a bit thin. Some of them are just marketing BS. I mean, that’s that’s the reality of the kind of diverse system that we have in the UK and local authorities are in a really difficult position in terms of how to navigate that and knowing what questions to ask. So you have a real experience on the ground of.

Kevin: 1:04:12

You know, they know the quality services they’re working with. They also are in their hamstrung at the moment because there isn’t enough provision. You know volume coming through the door is huge, complexity is huge. They haven’t got access to enough diverse services that meet need. So there’s all kinds of failing arrangements um, you know, unsatisfactory arrangements for children, um, overly expensive, certainly not delivering value for money. You know we’ve got, we’ve got a lot of that, uh, in our system in the uk, but it’s, but it’s not the whole by any stretch of the imagination. But where it would have been a frayed edge to our system maybe a decade ago, those are now big tears.

Colby: 1:05:05

But there are some challenges. It’s definitely expanding, there’s no question. No question.

Kevin: 1:05:09

You know it’s definitely. It’s definitely expanding. Yeah, there’s no question. Yeah, no question. And now we, we’re now beginning to see the kind of over the last, you know, I’d say the last half a dozen years maybe we’re beginning to see an increasing focus now on wanting more diversity, focusing more on practice. Therapeutic community standards, therapeutic child care standards they’ve always been around, but now they’re starting to be rediscovered and re-engaged with, which is it’s great. It’s also a little bit frustrating at the same time, because there’s been lots of people and lots of government reports over the years that have been pointing to these things, but somehow the system just wasn’t in a place to be able to make that shift. So there’s still a lot of work to go, but there’s definitely promising green sheets.

Colby: 1:06:00

Well, listen, kevin, it’s been an absolute pleasure to speak to you about these issues related to the work. I feel like, just kind of, this is a bit of a press pause, because there are some things that already that I’d like you know. Time permitting, I would like to follow up with you and, if you’re game, I’d love to have you back, you know, in in a little while on the podcast. But thank you for for making the time and um contributing, uh, to what’s been, for me, quite a very enjoyable and, uh, informative conversation well, no, thank you so much.

Kevin: 1:06:43

I mean, it’s been, it’s been looking to spend time with you and, yeah, I, I, you know I’ve happily unpack, unpack more of these issues in more detail, I suppose by way of apology. Uh, you know, you know, sometimes, um, the ideas link from one to another and maybe some of these points could have been put across more, more succinctly for you. Um, but no, I really really appreciate the opportunity to, to speak to you this morning and I hope that you know, viewers and listeners find, uh, find, some of that interesting and helpful.

Thanks, kevin.

Challenging Last Resort Thinking: Why Some Children Thrive in Residential Care, with Dr Laura Steckley

Reimagining Residential Childcare: Insights from Dr. Laura Steckley

The latest episode of the Secure Start podcast features Dr. Laura Steckley, a leading academic and researcher in therapeutic residential childcare from the University of Strathclyde. With over three decades of experience spanning practice, teaching, and research, Dr. Steckley brings profound insights into an often misunderstood area of child welfare. Throughout the conversation, she challenges the prevailing ideology that residential care should be viewed merely as a “last resort” option for vulnerable children.

One of the most compelling arguments Dr. Steckley presents is that high-quality residential childcare can be the optimal choice for certain children in specific circumstances. She points to research showing that many children who have experienced both foster care and residential settings actually express a preference for residential care. This flies in the face of conventional wisdom that family-based care is universally superior. Dr. Steckley explains that for children who have experienced relational trauma, the intensity of a family environment can be overwhelming and even threatening. The pressure of intimate family relationships can trigger loyalties to birth families or activate unprocessed trauma, making foster placements difficult to sustain.

Residential care offers unique advantages that Dr. Steckley illuminates throughout the discussion. The presence of multiple carers provides children with diverse relationship opportunities – increasing the likelihood that a child will connect meaningfully with at least one adult who, in the words of Urie Bronfenbrenner, is “irrationally crazy about them.” The structure also allows both children and carers to have necessary breaks from one another, preventing the relationship burnout that can occur in family settings. Additionally, the power of the peer group in residential care provides therapeutic opportunities that simply aren’t available in foster homes.

The conversation takes a particularly fascinating turn when Dr. Steckley discusses her extensive research on physical restraint in residential settings. Rather than viewing restraint as universally negative, her research reveals nuance – some children report that certain restraint experiences actually improved their relationships with staff. Dr. Steckley introduces containment theory as a framework for understanding how adults can help make “the unmanageable manageable” and “the unthinkable thinkable” for distressed children. Physical restraint, when done as an act of care and protection rather than control, can sometimes provide the physical containment that helps a child regulate overwhelming emotions.

Throughout the discussion, Dr. Steckley emphasizes the importance of understanding shame in children’s behaviour. She suggests that shame may be the most “uncontainable” emotion, often manifesting as rage or shutdown. This connects to her point about the importance of staff receiving adequate containment themselves through supervision and support. Without this, staff cannot effectively attune to children during escalating situations – precisely when attunement is most difficult but most crucial.

Perhaps most powerful is Dr. Steckley’s assertion that “in the daily minutiae of good care is where healing and developmental ground is regained.” This simple yet profound statement emphasizes that the day-to-day interactions, the consistent care, and the accumulated positive experiences are what ultimately help children recover from trauma – not just specialized therapeutic interventions. This perspective elevates the importance of residential childcare workers and recognizes the complexity and value of their work.

The conversation concludes with a discussion of the famous “still face” experiment, highlighting how children become dysregulated when adults fail to provide emotional attunement. This serves as a powerful metaphor for how professionals must remain emotionally present and responsive, even during challenging interactions with traumatized children. The insight that children escalate their behaviour when seeking attunement offers a radical reframing of how we might respond to difficult behaviours in care settings.

You can listen to the podcast here:

You can watch here:

About Laura:

Dr Laura Steckley leads up the MSc in Advanced Residential Child Care at the University of Strathclyde and so has the very good fortune of doing teaching and learning with residential child care practitioners.  She has worked in direct and indirect practice in both the United States of America and Scotland. Her teaching, research and knowledge mobilisation are mostly addressed to residential child care practice and education, with a particular focus on physical restraint.  

Related Podcasts:

Listen here:

Watch here:

Listen here:

Watch here:

Transcript:

Colby: 0:00

Welcome to the Secure Start podcast.

Laura: 0:03

The world needs people who care about these kids and are finding their passion for how they can make a difference in their lives, working in a place that is kind of the receptacle of last resort. I have been attentive to evidence to the contrary Good, high quality residential child care is the best choice for a very small number of children in very specific circumstances. So even for kids who don’t end up going back home or back to foster care, some of them go on to build a healthier, more rewarding family life in their adulthood as a result of the residential child care experiences they’ve had. I think multiple placements is one of the most damaging things that care systems do to children and young people. But to be able to have breaks from each other as part of an alternative experience of care, I think is really valuable.

Laura: 1:08

Also, having such a range of people with whom that child can have different kinds of connections or there’s at least one person there who can start to see the beauty in the child. That Bronfenbrenner quote of one at least one adult who’s irrationally crazy about them. We’re creating the conditions for children to experience themselves differently, and activities are about the best way to do that. Physical restraint is the most extreme form of containing physically containing then it may also be like therapeutically containing, and that also came through in the data the research did. There were kids who talked about purposely orchestrating events, such so they knew they would get restrained to either let anger out or to be held while they cried In. The daily minutiae of good care is where healing and developmental ground is regained.

Colby: 2:13

Welcome to the Secure Start podcast. I’m Colby Pearce, and joining me for this episode is a highly experienced academic and researcher in therapeutic residential child care. Before I introduce my guests, I’d just like to acknowledge the traditional custodians of the land that I’m coming to you from the Kaurna people of the Adelaide Plains, and then acknowledge the continuing connection the living Kaurna people feel to land, waters, culture and community. I’d also like to pay my respects to their elders, past, present and emerging. My guest this episode is Dr Laura Steckley. Laura leads the MSc in Advanced Residential Child Care at the University of Strathclyde and so has the very good fortune of teaching and learning with residential child care practitioners. She has worked in direct and indirect practice in both the United States of America and Scotland America and Scotland. Her teaching, research and knowledge mobilisation are mostly addressed to residential childcare practice and education, with a particular focus on physical restraint. Welcome, laura.

Laura: 3:38

Thanks, Colby.

Colby: 3:41

Now I always like to ask people was there anything else that you’d like to add to that short bio?

Laura: 3:52

Yeah, I wanted to keep it short and snappy. Direct care, um, training management, um, all of that, um, some of the bureaucratic admin stuff, um. And then came to teach and do research at the university of strathclyde in 2003. So I started working in resi in 1990. It’s been at it for quite a while. Hopefully there’s a kind filter on the Zoom today, but yeah, I’ve been at it for a while, but it’s yeah, it’s still been my main focus and passion really as an adult, you know in my professional from from pretty much the start yeah, yeah, and a concept that we concept or construct, that we spoke about during a pre-meet a few weeks ago was that of pracademic.

Colby: 4:56

So you, yeah, you fit, you fit the the profile in terms of having significant practice experience and having the good fortune to be able to research, and yeah, further study work and I’m interested in practice Like that would be another way of saying what my research and teaching interests are.

Laura: 5:18

And yeah, I’m really interested in practice and I think it’s a forever rich, complex, rewarding area to support, to study, to try and and develop in terms of workforce in Scotland, and Scotland’s been a good place to be doing that for sure yeah, yeah, yeah, I mean people will Scotland, and I did mention that you’d worked in the US as well, but you obviously don’t have a Scottish accent.

Laura: 5:49

Yeah, yeah, no, scotland’s been a good landing place for me, so I was already working in residential when I moved here, but I moved here in 1999. So I’ve been in Scotland. For what is that then? In?

Colby: 6:04

the beginning of 99.

Laura: 6:06

So that’s 26 years, yeah so. But as I just mentioned a little bit ago, scotland has pretty high aspirations around care more generally the the alternative care, you might say, of children and young people, including residential child care, and I suspect we’ll be getting into some of the challenges around that coming forward. But, um, it’s not perfect here, most definitely not, but um, but the aspiration is there, which has been a really good landing place for me. It felt like the stars aligned.

Colby: 6:43

Yeah, speaking to other guests, it sounds very similar. Yeah, yeah, so residential childcare. Tell us about how you came to be working in this really important and, at times, controversial area of childcare practice.

Laura: 7:03

Actually, before I answer that, I’m going to give a little anecdote On the MSc in residential child care. It’s primarily managers but some frontline practitioners, and because there’s a big component of the use of self and who you bring to the encounter with a child, or who it is of yourself that you bring um to the class, to the studies, um, we start the whole year with this um activity called river of life um and people choose what they want to share, but they chart what, the key things that have happened in their life that brought them to this day where they’re embarking on a master’s level.

Laura: 7:44

For some, like they haven’t had good experiences of education in their past, whatever, but what’s brought them to have that level of commitment, to be working in residential child care and to be doing this work, this educational work in relation to that, and for many years. Well, we’ve been doing this for now 20, 22 years maybe it’ll be this september. Um, it’s extremely rare and most years no one says. I wanted to be a resi worker when I was a kid, right, and many people didn’t even know what residential child care was myself included, or residential, didn’t know anything about it and, like so many others, I fell into it almost accidentally. And this is a common theme across that and what that does to our workforce in terms of how it shapes professional identity, which we may or may not get into. There’s so much we could talk about today, but, um, so I, I thought I was going to be a lawyer, that was going to be an attorney, and I, I like arguments, not like hostile argument. I like building a strong argument. Um, from a young age and I was interested in courtroom dramas as a kid.

Laura: 9:05

So I did an undergraduate degree and in the United States you do four years undergraduate and three years law school. So I did my undergraduate degree focusing on what would get me into law school, and I did a degree in political science, or a major as we call them, and I found it really just just despairing, actually, the grimness of the political realities of the world, which are only getting worse, I think. But I also took an ethics class that I loved, and so that was in philosophy, and so I took another to get my humanities requirements out of the way. But I just kept taking more and more, and so I did a second major in philosophy and I have to tell you that equipped me more for residential child care than any of the psychology I took, maybe because of the type of psychology that was being taught at my university.

Laura: 9:59

And when I finished the four years I knew I wasn’t mature enough to go to law school like self-discipline and all that and so I thought I need to just go be in the world and work, and a friend of mine had gotten a job in a residential treatment center and she’s like we need staff, as you do, and she’s like maybe you’d be good at it. And so I’m like I don’t even know what that is Like. So I went along and she had told me a bit about the work before I went. So I kind of thought about you know what that might be like and what, how I might approach things. And I did well enough in the interview to get a job, although maybe they just needed a warm body, I don’t know.

Laura: 10:41

And I swallowed the hook, man. I just it was so frightening and intense. But every day was different and it was meaningful and I loved the teenagers. They were difficult and didn’t always feel love for them, but overall I loved working with teenagers. I loved working as part of a team and it didn’t take long before I realized the world didn’t need another lawyer, do you know? But the world needs people who care about these kids and are finding their passion for how they can make a difference in their lives.

Colby: 11:16

So that was that was the path for me into this work so when you, when you were working initially in residential child care, um, cast your mind back, what, what influenced the way in which you went about the work, would you say. Were they, what? Were there people that had influenced you? Were there? Was there um particular theories or bodies of work that um that you came across that were of influence to the way you went about being a residential child care practitioner?

Laura: 11:52

It was a bit more theoretical. In the States At least they espoused or claimed to follow, positive peer culture was the first place I was in and I learned about the power of the group and that has influenced me ever since. And Scotland, maybe the UK more widely, is a bit afraid of the group. It feels like afraid of groups of children, especially teenagers, and we don’t harness and we’ve also become much more individualized collectively, I think, at least in western society since my, since the early 1990s. So it’s not just the UK probably, but yeah, so we struggle to harness the power of the group, I think now, but it’s still there and I still kind of push against it.

Laura: 12:36

Ruth Eman’s work who would be another great person to have on the podcast is brilliant. She um for her phd. She lived in a residential child’s home as an adult. She didn’t pretend she was a kid, but she also was very clear I’m not a member of staff, I don’t have keys. She had a bedroom like the other kids had bedrooms and did an ethnographic study of um the children’s culture outside of the staff gaze. She couldn’t do it outside of the children’s culture outside of the staff gaze. She couldn’t do it outside of the adult gaze because she’s an adult right and they tested her. You should get her on because she talks about how they tested her to see if she was going to like take things back to the staff. And she was really clear like if it’s serious imminent harm kind of stuff, we got to take that back, but otherwise so they would test her and stuff. But she did a brilliant and she’s done brilliant work ever since then.

Laura: 13:29

So, I’ll talk more about her with you, maybe after, but anyway. So the power of the group. I think the other big thing was the move from the United States and a treatment focus which was more deficit based, more medicalized orientation to the work. That was so pervasive that I didn’t recognize it as such because that’s just how we all thought. And that was the wider culture to residential child care in Scotland which felt sorely lacking in theory, not that we were actually using theory as well as we should have, but really understood care well, understood care better than in the United States. And I think care is the way to go. Not that there isn’t a place for a treatment orientation, but I think it’s where, in the daily minutia of good care, is where healing and developmental ground is regained. And that relationship within which that care takes place and those relationships even John Toronto’s work as a political philosopher about the marginalization care and the fact that we need to bring it to the center of society’s concerns all have played a big part. And that’s just a little bit.

Colby: 15:25

When you were talking about the difference between what happened in the US and what you were observing in Scotland. It made me think about treatment as being something that you do, too, and care as being something that you do with.

Laura: 15:38

Yeah, if you’re doing good care. Yes, and we didn’t always. Even once I got to scotland in 99 and I didn’t get a job for about six months and and I think when I had um submitted applications and even did an interview, they were like, they were like I’m not sure about her, you know, because I was coming from it’s such a different orientation but a place took a chance on me and um and you know, I worked then in scotland in care um for a few years four years, something like that before then going on to work at the university.

Colby: 16:16

So yeah, yeah, and and I recall from our conversation, um, during our pre-meet, that you have some things to say about what children say about their experiences in residential care. I wonder if you’d be happy to share some of that.

Laura: 16:34

Sure, so yeah, so in both the United States and in Scotland and I’m aware from the literature, many places in the world residential child care is very much treated as a last resort and there’s this underlying belief that sometimes not even adults are not even aware of, or that they don’t scrutinize if they are aware of it, that like that’s the worst thing for a child, and so working in a place that is kind of the receptacle of last resort.

Laura: 17:11

I have been attentive to evidence to the contrary and and there have been some interesting studies, none of which that I’m aware of have focused in on which is better and under what circumstances, and maybe I’ll put my cards on the table, to use a poker metaphor I believe residential child care is the best.

Laura: 17:35

Good, high quality residential child care is the is the best choice for a very small number of children in very specific circumstances, and so, um, in 1998, barry Jim Brody did a really significant study and that wasn’t their focus, but that was kind of, and that’s how it seems to be coming through in the research. That was kind of a side thing that they included. Jim Anglin, who’s a North American, his seminal grounded theory study has a batch of and what’s happening in these studies is kids who’ve experienced both foster care and residential child care have had things to say and often it’s been a majority have had a preference for residential child care. Um duncalf in the uk. Um is a care leaver herself and she did a big um quanta or a big um questionnaire type study and quite a lot of people responding had had experience of both and a high proportion preferred residential child care to to nearly half experience. The placement is very positive and 78 preferred residential, 78 percent preferred residential child care and 5% indicated they preferred foster care.

Colby: 19:11

Why do you think that is the case?

Laura: 19:14

There’s more recent ones, but I’m less on top of them anyway. So I think again, if it’s good quality residential childcare and it’s the right child’s circumstances, certainly the pressure of the more intimate familial relational demands that we naturally make of one another as part of being in relationship with one another would be experienced by some children in a foster home as even potentially intolerable because of the loyalties or ambivalence the loyalties to their family of origin or their ambivalence about these kind of relationships, because of the damaging experiences they might have had in similar type of relationships that haven’t yet been cognitively processed, digested, um, and so that’s, I think, why foster care goes wrong a lot. I also think foster carers are often put in horrible situations, you know as well, and I think we do damage to adults with this as well as damage to kids by placing them on for ideological reasons that foster care is better because it mimics family more.

Laura: 20:33

But I think residential child care has more resources, even though it’s poorly resourced in most countries, has more resources just in the sheer number of adults. And if there’s a good culture or there’s good training and ongoing as well as entry-level training, then I think as well as just like activities, the power of the group, all of that kind of stuff, and sometimes it can be a bridge back to either family of origin or back to and I’ve worked with kids where we provided bridging experiences which England I don’t know if he coined the term, but uses that very well in a seminal study experiences that then enable them to access the kind of normal experiences of either going back to their family or of origin and and or foster family and being able to have more normal family life. Um, but I don’t think there’s enough recognition of what some kids need to be able to do that. And then there are other kids who either aren’t able or don’t want to have that as part of their childhood. They might go on to have that in adulthood, to have that as part of their childhood. They might go on to have that in adulthood.

Laura: 21:47

I’ve had a student who looked at outcomes of the placement that he had worked in, but these people were in their late 20s and early 30s and one of the most significant outcomes that they identified this whole dialogue around the whole way we use outcomes. They were defining outcomes themselves, which was a really powerful but small study, and they said you know, I parent my children differently because of the way that I experienced relationships with the adults in this home and the reparenting they didn’t call it that as compared to how my parents parented me Like. So even for kids who don’t end up going back home or back to foster care, some of them go on to build a healthier, more rewarding family life in their adulthood as a result of the residential child care experiences they’ve had. We have some small bits of evidence from small scale study and anecdotal evidence as well, and the reason why we don’t have more evidence is because we’re not designing research. That’s asking the right questions and that’s a funding issue, but yeah, anyway. Yeah, I’m not good at short answers, sorry.

Colby: 23:04

No, no, that’s okay. It has often been said of me as well. I can write succinctly. When I used to do a lot of court work, I had a bit of a reputation for giving long answers, but amongst the lawyers, that is, I’m glad I’m not with a kindred then yeah, yeah, so, um, but yeah, you said a couple of things there of of interest to me.

Colby: 23:31

Um, I’ve long also felt that there are there are young people who find being in a family, young people in the out-of-home care system who find being in a family emotionally unsafe and threatening.

Colby: 23:48

They just the level of closeness that we expect of people, and it’s tragic to think that they might go through any number of family-based foster placements before, at some stage, someone decides well, they’re not really getting on at all in foster care, so we’ll have to invoke the option of last resort, as you say. Whereas if you actually thought about the experience of the young person, thought about the experience of the young person, so, rather than making an ideological decision that the best place for children to grow up is in a family environment and that’s a general ideology, as you say if you actually just treated each child on a case-by-case basis and thought about the particular characteristics of each child and what their needs might be, there are likely to be a proportion of young people that you would, from the outset, choose residential care for. Yep, and what I also heard you say and I often think of the impact of relational trauma as being like a phobia. Yeah, and what’s the best treatment for phobias? Graded exposure. The thing that they’re phobic of is relational closeness.

Laura: 25:16

And so we put them in situations where it’s too intense, too fast and we actually deepen the phobia or we deepen the hurt, and I think multiple placements is one of the most damaging things that care systems do to children and young people. Yeah, we’re totally in agreement about this. I would add. For that to be possible, though, people who are making placement decisions need to understand what residential child care can offer, understand what can happen or what does happen in good residential child care, and then residential child care needs to be supported to do what it can do so well, and those two things are really precarious at best when they’re when both of those things are kind of functioning, but often people have no idea, and so all they have is that ideological thing to fall back on, because they just don’t know.

Colby: 26:14

Yeah, yeah, I am concerned that if we maintain the idea that residential care is the care option of last resort, then it’s hard. It’s difficult for me to conceive of that. Policymakers would fund it well yeah, exactly so.

Laura: 26:32

It’s this vicious or vicious circle or self-fulfilling prophecy, like it’s and, and, yet and. And. This is why, in Scotland, it’s a good place to be, because the current Scottish government does have an investment. It can’t back up that investment with the kind of resources that are actually required, or it? I mean, there’s always money, but who has the money? Like it’s not, like they’re swimming in it. They have it. They have to make decisions, and I certainly don’t think residential child care is the only thing deserving of resources, right, so I wouldn’t want to have to be the person making those kind of budgetary decisions, but there is that aspiration in the Scottish government. There is an awareness of residential child care and of care more generally. This has been one of the great things about living in Scotland, especially as compared to the United States, is the Scottish government, and Scotland is small enough that policymakers do really listen and you have access.

Laura: 27:37

I’m part of CELCIS and the Department of Social Work and Social Policy, and CELCIS has changed its name, so it’s no longer the Center of Excellence for Looked After Children, but I can’t remember the exact bits now, but CELCIS is one of the many ways that Scottish government communicates, and then I’m part of CELCIS, and so I’ve watched the Children’s Act get influenced by care experienced activists and CELCIS was a bit a part of that in the background experienced activists and CELCIS was a bit a part of that in the background, and that activism informed some of what came out of the Children’s Act 2013, I think, such that children’s age of leaving care got extended to 21, with support of through care to 26. And there was a very much relational face-to-face impact between the then head, Nicola Sturgeon of the Scottish government and care experience people that you know, and the promise also came out of all of that too. So, yeah, yeah, small is better sometimes.

Colby: 28:50

Yeah, I think so, and you also mentioned before about children going back to birth family, and you mentioned bridging and spoke about James Anglin. There’s a name I’d like to get on my podcast as well.

Laura: 29:08

Oh yeah, wouldn’t that be great.

Colby: 29:10

So we’ve talked a little bit about how residential care if you think about trauma creating a phobia where the phobic object is relational connection, that’s where children feel most unsafe and the best treatment for that is graded exposure. So you gradually re-expose them to relational connection. With birth, family connection. I often think that residential care has the opportunity to lead the way in terms of birth family reconnection, because there’s less agendas when you’ve got a professional workforce working with children. It’s much more vexed if it’s family-based care, if it’s foster care or, you know, if it’s kin as well, where oftentimes the kinship carers are quite negative in their disposition towards the parent on the other side of the family, so to speak. But even foster carers can be very unforgiving of birth parents. So I think so birth family reconnection, I think is something that residential childcare can lead the way. And I guess this kind of leads me into wondering about what you’ve discovered, about what else you’ve discovered about how residential childcare can offer things better things or offer things in a better way than other forms of out-of-home care.

Laura: 30:52

Well, right on that point that you’re making, I think sometimes the care that they give to families as well, and helping families make sense of their child’s behaviour, for example, creating spaces where children and their family members can start to have that graduated kind of reconnection, so, and I think you know, often it’s less threatening for the family too that these, especially if there’s a school on site, then oh, my child’s at school and they’re just the staff at the school. I think that makes it even easier. But even in a care home or they refer to them as houses in a lot of places here because of the negative stigma attached to care home but so in houses here, like it’s still a house, that is kind of professional versus the foster care, so kinship care, so yeah, I definitely think there’s that. I think I think the power of the group, as I’ve mentioned having, I can remember, being able to endure and actually be really present and, um, really tolerant and creative and bear quite a lot of rage or difficulty, sometimes into three or four in the morning, having worked a double, you know, having started the morning before whatever, or just the energy of like camping and like many days because I knew I was going to go home and go right, and so I think there’s something about. And for kids too to have a fresh face, like with all the shame. I think shame’s a part. So I think there’s phobia, but I think shame’s an interesting part. We talked about that earlier and I haven’t read the thing you sent me, I just remembered. But um, but to be able to have breaks from each other as part of um, as part of an alternative experience of care, I think is really valuable. That’s just not structurally possible in a foster home or in kinship care. I mean, the break is from the family of origin and sometimes there’s to-ing and fro-ing that happens there. That can be helpful but often isn’t. So yeah, I think there’s that.

Laura: 33:22

And also having such a range of people with whom that child can have different kinds of connections, or there’s at least one person there who can start to see like the beauty in that child that Bram from Brunner quote of one, at least one adult who’s irrationally crazy about them. And for some kids, what’s happened to them and their way of coping and defending themselves has become such a rejection of the world and ways of please reject me, kind of to keep you away from me that it can be really hard to see that child’s beauty or wonderfulness in whatever form that it manifests. And the large you have a large enough group of people and once that starts, then that can spread to other people and so, while we all sometimes have to try to look for it and have to pretend isn’t the right word, but when it’s difficult you kind of have to shift to where there’s this really genuine, authentic reflecting back a child’s goodness to him. The bigger the, and we all need that experience in our lives, not just as children, but we need a lot of it as children.

Laura: 34:38

And then, if you’ve had really hurtful experiences, you need more of that and I think I think that’s something that isn’t really talked about, but I was very aware of it in practice when I had those moments where that happened and I was able to do it. It sort of just happened at first and then I became aware of it, was able to do it, and I think like that would be an example of like people who don’t understand residential child care wouldn’t even be able to muster that up. But that happens within good teams and really good teams who are cooking on gas. They talk about it and like who is connecting with with this kid just now? Who is able to reflect back to this kid? His goodness? Um, it’s probably not happening all over, but there’s.

Colby: 35:21

So there’s so much in what you say I mean um.

Colby: 35:24

It puts me in mind of the my own observation, across 30 years of practice in child protection, out-of-home care and related endeavours, which is that our children don’t just.

Colby: 35:39

I often think about the one good adult research and I think, yes, absolutely we need to have. As Yuri Brompton Brenner said, you know you have to have one of those adults in your life, but I do think the more good relationships that children have, the better. So I think you know our child protection system is very much focused on whether you’ve had a bad experience with parents here. So what we’re going to do is line you up with some new parents and you’ll have experiences with them that will, that will remediate, that will repair the the damage that is done there. And you mentioned earlier about how foster carers often get um hurt themselves through in in this um system and and largely that’s because, from my point of view, that they’re sold. They’re sold a bit of a dummy really, about what, what, what is possible, what, what, they, what they can, what can be achieved um and what will be demanded of them.

Colby: 36:52

Yeah, yeah. The reality is that there’s so much more that needs to happen to help a child or young person recover from that early relational adversity.

Laura: 37:09

Yeah.

Colby: 37:10

I’m not particularly au fait with the power of the group that you know when you’re yeah, and I wondered if you might just uh say a few words about that and what you mean for my benefit. If not, you know other other listeners as well okay, gosh, where to begin?

Laura: 37:27

I think I’ll start by saying, like, anytime you have a group of people, or even just two people, and probably intrapersonally as well, there’s always dynamics that are happening within a group, and I think being able to channel some of that is useful. But I also think so my first experience was with a model called positive peer culture. Experience was with a model called positive peer culture. So and this is about the power of peer relationships to foster positive change, so much so that, like we were encouraged and sometimes even corrected to, if we didn’t do this, instead of, like, directly confronting a kid’s behavior, you would sidle up to a different kid and say I’m interested in the fact that you’re noticing so-and-so, struggling with this authority problem and you haven’t yet called a group. And the whole day, even in education, like if something was happening, any child could call a group or adult could call a group, but ideally you want the kids calling group and then they circle, they stand up and they circle up and they’re like I’m calling this group, Colby, because I see that you’re struggling with your authority problem with Mrs Smith and I think we can help you with that. And there’s this whole list of problems. That, on the one hand, is good because it gives kids a way to identify things and a language for it. It’s pretty deficit based because it’s all problem based. But, um, and then they talk and they swear at each other and they fall. But do you know, and these kids were so insightful and so, and they would listen to each other in a way that they don’t listen to adults, right. So there’s that like, and that happens anyway.

Laura: 39:15

I mean, that was a very structured, facilitative approach. That was sometimes amazing and sometimes it felt a bit dodgy. No required qualification for us to be doing that and like the power of that. You really had to be good at it and you had to have an understanding and a value base because, yeah, you could use a book group to bully a kid, for example, a kid who’s given you problems or whatever. So there was all that, plus I would and I’m going to draw on Jack Phelan He’d be another great person to have. By the way.

Laura: 39:56

He wrote this really small article a while back and he’s now got a book out that I haven’t read yet but is on my list. But this little nugget was this thing called experience arranging and he was like child and youth care work isn’t all the things we think, it is, it’s experience arranging. That’s what we’re doing. We’re creating the conditions for children to experience themselves differently and activities are about the best way to do that. Especially if the activity is fun enough or engrossing enough, then it drowns out that background narrative of I’m a bad kid or I’m too cool for this or all of the stuff that gets kids in the way of being able to experience, say the restorative foster parents that you mentioned before.

Laura: 40:45

So group activities if and again it requires skill and fortitude to do well can really enable children and, like for my master’s dissertation, which was the school football team that played against other special schools, and the way these boys some of them had already got aged out, as we used to call it the way they talked about those transformative experiences of the school football team and they never at that time would have been able to access a normal mainstream school or league.

Laura: 41:21

You know, football team because of the behavioral difficulties was like life-changing for them and um, they, they could have that as part of a group and um, like, they could remember Colby, like remember that game where we played against and then they named the other school and I was coming down the line and like this was a few years prior and and then he just knew I was going to pass it to him and he was right there and and the excitement and everything. It was just amazing. So I guess that is what I mean about the power of the group and for a lot of our kids they don’t have the normal experiences of group that kids, which I think is reducing for all kids right now. To be honest with you, Sports and band and all of that. The funding for all that is is not good, but, um, yeah, that’s what I mean yeah, thank you, that’s.

Colby: 42:17

That’s a wonderful description and, um, it put me in mind of sports teams yeah, as you, as you were talking about it and then. So it was nice that you you finished up the talk giving a sports example and I love what you’re saying, what you’re attributing to Phelan. I totally you will never talk a child out of believing that they’re bad.

Laura: 42:45

Yeah, you’ll never talk them out of it. They have to experience themselves.

Colby: 42:48

They have to experience themselves in a different way. Never talk about it. They have to experience themselves in a different way. They also.

Laura: 42:56

You’ll never, you’ll never talk them into trusting people right until they can until they have the experience, and that’s the minutiae of care of really good care the little drips of care that that that’s where the restoration happens. Not that the therapy hour doesn’t have its place, but yeah.

Colby: 43:16

Yeah, recent guest, Adela Holmes, who set up Hurstbridge Farm, a residential therapeutic community here in Australia. She was talking about getting the you know what comes first the cart or the horse, in this sense that we often expect children to behave and as a reward for that, we will give them good relationship.

Laura: 43:42

Yes, yes.

Colby: 43:44

Yeah, and it’s outrageous, isn’t it? And it has to be the other way around. Yeah.

Laura: 43:49

Yeah.

Colby: 43:51

Now I want to. People are going to wonder a bit about this little segue. Your research interest has been in restraint. One of your great I know this, I’m not sure if you’ve mentioned it already, but one of your great theoretical passions is containment theory, containment and restraint yeah, yeah, so I can remember, because I I did have to restrain children, um, young people really.

Laura: 44:28

I’ve mostly worked with young people. I remember like something is going on here that is powerful and I don’t understand what it is and I need ways of understanding this. And it really troubled me, like, and I became the in-house trainer in in one of the places in Colorado for for crisis, for you know, restraint and all of the stuff that went around trying to avoid getting into restraint, um and so. So physical restraint for anybody who’s watching that doesn’t know exactly about residential child care and physical restraint it it doesn’t just happen in residential Chicago, it happens across a lot of strata of society. But in residential child care if a child poses serious, imminent harm to themselves or someone else, um, and the adults responding have no other way of of making it safe. They sometimes have to hold a child against his or her will and it can be really horrible for everybody. People can get really hurt.

Laura: 45:39

So I did a study in 2000. It probably started in 2003, and it went on for a long time, partly because I collected so much data. I had to do justice to all of that. So I published from that data for a really long time, and it took a good few years to collect the data around people’s experiences of restraint. And I also then came to be aware of containment theory as a way of, first, of a way of understanding what was happening in the data, what I had experienced, as a way of understanding what people were saying about their experiences adults and young people and children and then containment theory just has become an organizing frame and a way of seeing the world generally. For me it’s not the only way, but it is a big one and the end of seeing residential child care practice more widely. So, um, so I’ve done some other research in relation to physical restraint and it’s recently been announced, so I can say here, that the Scottish government is funding a 30-month project that I’m a part of, leading up around mainly research but also some knowledge mobilization, and it’s not just we research and then we give the knowledge, like we’re mobilizing knowledge from the residential child care sector while at the same time giving knowledge back. So there’s this flow of knowledge between us that’s being mobilized in the best interest of children, young people, around reducing, where possible, eliminating, restraint. But here’s the other thing, and again I’ll put my cards on the table, but also ensuring that when not ensuring because we can’t raising the likelihood to the greatest extent possible that when restraints do happen they are experienced as an act of care and protection by the child or young person.

Laura: 47:41

And actually that first study, there were children and young people who said some restraint. So I asked a question like how did the restraint affect your relationship with the people who restrained you? And then adults, how did it affect your relationship with the kid that you restrained? And adults all said either it damages it or they’re kind of neutral about it. But children and young people over a third said in some cases it improved the relationship. Okay, and I was doing the interviews both at the same time.

Laura: 48:19

I didn’t do like children first and then adults or vice versa. So I started asking adults, once they had exhausted what they wanted, to tell me what about the other side of the coin? Is there ever a time that it’s had a positive effect and a really high proportion once, given the question and maybe some permission where, well, with some kids like, there’s a relief or you know so, um, so I think when kids are at their most extreme states of distress, rage, um, all of the things that happen in the lead up to a restraint can be understood. And now I’m going to shift to containment theory. So I’m going to give the very boiled down version. So containment theory is really about what makes the unmanageable, unbearable, intolerable, uncontainable, containable, manageable, bearable, tolerable and that like and that like. That’s the way in, that’s a boil down and most people can recognize states of being uncontained and that’s another way in. So if you’ve ever yourself been so such strong feelings that you can’t think straight, feelings that you can’t think straight, um, then that would be an example of being uncontained.

Laura: 49:44

And beyond, who’s the father containment theory? Um, so it’s actually a developmental theory that we develop the capacity now here’s the other little boiled down way and to use thinking to manage raw experience and emotion. Right, so, to be able to use thinking to make it containable, manageable, um, and we all have moments or periods of time, individually and groups, have this, where it where we lose that or where it’s lost a bit and we’re not thinking very clearly as a team and we become punitive. There’s lots of ways we can identify this in our own lives, and so physical restraint is the most extreme form of containing, physically containing. But if there is all the other things, the relational part, it’s handled in the most child-centered way possible up to and during the restraint and then post the restraint, then it may also be therapeutically containing and that also came through in the data.

Laura: 51:01

So containment theory will be very much a part of the the um study that’s about to start. That it’s more than a study because it’s also got some knowledge mobilization in it. But um, but there will be others other elements to that as well. But certainly there are a lot of things that happen for kids that are uncontainable, right, but also for the adults. So if adults are going to be able to buy and also talked about, like the mother absorbs the child’s uncontainable empty stomach, uncontainable empty stomach or just dysregulation, we’ll use dysregulation because that’s identifiable For Brian it was.

Laura: 51:44

The mother would absorb that and give it back in a more containable form the clean nappy, the full stomach, the rocking, and there is something very physical, I think, about our needs for containment. That’s very challenging. So staff do their version of absorbing it and then giving it back in a more manageable form, which could be something as simple. As you seem really upset about that, let’s go for a walk. There’s a bit of containment in there. But they need contain because there’s a lot of things that happen in the work that raise anxiety, that are hard to manage, that, things that are frightening or concerning or um, and not just the children’s behavior but the fact that you work in a field that’s last resort and stigma that can go with that, organizational policies and practices that aren’t so helpful.

Laura: 52:40

There’s all sorts of things that can cause scandals and history of institutional abuse.

Laura: 52:47

All of that stuff can in a very unconscious way create anxiety that then compromise adults’ ability to be good containers for kids through their relationships. If we can help that and if that containment gets stronger, that therapeutic relational containment and the rhythms and routines and positive symbolism and all that stuff symbolic communication then I truly believe in. There’s some anecdotal evidence and another project I’m a part of is beginning to produce other kinds of evidence that it can reduce restraints through because that stuff is being contained earlier in whatever process of escalation might’ve occurred, that sort of thing. So that is a very messy attempt to offer an introduction to like what the two are and what they have to do with each other. Yeah, we’ll start there, or we could even end there when I first started getting excited about containment theory, I kind of felt like I was not a sole voice but one of a very few voices and you know banging on about this, and I knew that most people were hearing something different than what I was intending, because of Restrictive practices.

Laura: 54:08

yeah, Exactly of the negative connotation and I’m like well, holding environments Winnicott’s holding environments is kindred like. They’re very and beyond containment. They’re very, very close and I often use the two almost interchangeably um, but holding therapies, especially like um, the, the attachment holding therapies that foster klein was doing in the united states. I just didn’t want that to get conflated, because that’s very contentious work, that um, kids were deliberately provoked and then held, and because I was like, yeah, with physical restraint I thought I can’t go that way. So I just kept banging on about it and I I have to say in scotland containment theory is getting traction. It’s becoming part of people’s vocabulary in a way that is useful in helping them understand their own needs to be able to meet the needs of children. It’s not uniform across the whole country or anything, but it is definitely getting traction and it’s exciting when students are like, oh, like anything that has explanatory power, and people are like, oh, this helps me make sense of stuff, and then they start using it in very enthusiastic ways. We’re that and that’s.

Colby: 55:22

That’s been very rewarding, for sure yeah, previous podcast guest, lisa etherson, has um. She’s the person I was telling you about, who, who has developed shame containment theory yes, yes, that’s the thing I need to read that you said yeah, yeah well, yeah, yeah, read it. Uh, it is. It’s very interesting. I hope to have her back on shortly. You know, before we move on from that.

Laura: 55:50

Sorry, just it just occurs to me that shame is probably the most uncontainable emotion, and so I immediately can see a link there, like shame is so intolerable of all of our emotions that we usually shift it into rage or we shut down. And so being and part of containment theory is about making the unthinkable thinkable and the unfeelable feelable, and so, and I think shame is one of the most important unacknowledged, unaddressed aspects of what’s going on in practice. So, from my practice interest, um one of the projects I’m working on, we’re beginning to look at shame and how we can make that more recognizable and dealable with um, so the fact that she’s linked that with containment actually sparked something for me, in a way that when we talked about it before it hadn’t, it hadn’t set legs in.

Colby: 56:53

So that’s yeah, that’s really interesting what you interesting what you said could have came out of Lisa’s mouth, then Really, yeah, based on my experience of listening to Lisa talk about it, yeah, absolutely that it does get shifted into rage, and you do. You then do think about some of of our you know our significant social problems in society, in society that are anger and rage based, and, um, and the importance of understand for me, the importance of understanding where that comes from. I think it’s probably just misattributed to as just being to do with toxic masculinity, for example, or you know one’s own, you know cultural factors around male aggression and so on, when male aggression, a significant component of it, for example, is this uncontained or can be uncontained shame related to that and until we get to grips with that yeah, until we get to grips with it, we won’t fully get.

Colby: 58:11

we won’t get as far with dealing with some of those social ills that revolve around male aggression in particular.Laura: 58:19

Yeah, and understanding it.

Laura: 58:23

Yeah, understanding it isn’t justifying it in any way. Understanding it can lead us to better solutions, yeah, and it’s in everybody’s interest. The other thing about containment containment doesn’t just make it go away, and so, like the previous ways that term has been used, I think there isn’t much thought about what happens after you contain it, like that’s it done, happening at work, and you have a really good containing supervision. You don’t come out of that supervision with your anxiety taken away. You come out of that supervision with greater clarity of thinking. You come out of that supervision with a greater sense that you can manage what previously felt more unmanageable, and you come out of that supervision maybe with a bit more hope and and um things that you can do. And so, yeah, I think that’s the other thing I wanted to say about containment theory it doesn’t make it go away, it just shifts it to something more manageable, clear thinking, all that kind of stuff. But boy don’t we need that in society. Or, after a really difficult shift, the whole range yeah and and, uh and super.

Colby: 59:41

I love what you said a little bit earlier when you were talking about it, about the need for staff to be contained to, and it’s been a it’s been a consistent theme that’s come up in this podcast over the past 19 odd guess 19 guests that I’ve had on um, most of them talking about the need for a containing supervision arrangement in order to yeah, yeah, the other thing, just talking about restraint and some children, I can, you know, looking back at my own practice over the past 30 years, I can easily think of the kids who actually sought out physical contact, part of safe care, and safe care practice in out-of-home care not just, I guess, in therapeutic residential childcare but in foster and kinship care has perhaps led us away from the role of touch, the role of holding, and we have children who haven’t been held.Laura: 1:01:00

Right Physically.

Colby: 1:01:01

Physically held for years and years and not everybody.

Laura: 1:01:06

Sorry, I’m getting excited.

Colby: 1:01:08

No, that’s okay, I was just going to say 1995, I had a paper published in the Journal of the American Academy of Child and Adolescent Psychiatry about the importance of physical touch on mental health and wellbeing.

Laura: 1:01:22

Yeah, yeah, you know, not everybody needs health when they’re at their most uncontained or when they’re uncontained generally, but a lot of us do, and a lot of kids do. You add to that, though, that being touched and held like you might need it, but you also need for it not to happen, or you’re, whether it’s phobic or what meaning it has for you after um, after people have have um been exploitative around that or hurtful around that, so, um, so that’s this whole another layer of further anxiety that staff are um undergoing and the the research did um there were kids who talked about purposely um orchestrating events such so they knew they would get restrained to either let anger out or to be held while they cried they were a minority, but they were, it’s still significant and or witnessing that and thinking that’s what was happening for another kid. And there are people who have really had a problem with that being in my findings, or with kids having anything positive to say about it. You know, like the positive impacts on relationship being in my findings, um, and I think you got to create a space for all of people’s truths to come forth and then try to make sense of that truth in a way that doesn’t distort it. But um, yeah, but here’s the.

Laura: 1:02:53

The other thing is catharsis, like our bodies have a somatic reaction to the emotional dimension and we haven’t really dealt with the fact that a child’s body will have needs during that, not just this abstract emotional need through talk dealt through talking but adults as well.

Laura: 1:03:17

And so what’s going on there that we might be brave but also really careful about to try to better meet kids needs? So again, so that either restraints aren’t needed or when they do happen, it’s experienced as an act of care and protection. Do you know, and I think the thing I’ve become very interested in very recently is that attunement, so that achievement and the ability to reflect back what you’re tuning in on when you’re in that escalating phase, maybe going up to a restraint, like how capable are most people of doing that when actually they’re either shutting down or having to manage their natural desire to either shut down or their natural defense, or to shift to rage or whatever it is that’s happening for them, but to actually be there for the child and be attuned to that child, and yet I think that might be emotional availability and attunement in those peak moments are the hardest thing.

Colby: 1:04:40

But maybe the most powerful thing to avoid it going to the kind of brutalizing restraint that kids have described in my research and in many other places.

Colby: 1:04:45

Other research and the promise and that sort of thing, boy, that’s advanced practice, isn’t it? You know, laura, there is so much we could talk about. I know, I’m sorry, just what you were saying. Then a couple of things, though that I reflect a couple of my own reflections on that. And it goes back to what you were saying right at the beginning of this talk, which is that for for a cert, for for certain children, resident residential care is the best option for for certain children, it aligns with their needs, but in order and and then, and at that time I reflected, you reflected, and I reflected too, that we need to get away from these kind of ideological approaches to the care of the children and actually understand what each child actually needs. Yeah, yeah. And similarly, you’re not saying that restraint is a good experience, far from it. You’re not saying that restraint is a good experience for all children, but there are children who will seek out that physical contact, that physical containment, because it meets a need for them.

Laura: 1:06:00

Yeah, and we have to figure out how to deal with that, or we’ll do much greater damage to those kids. Even though they’re a small minority, they matter, you know, and people aren’t making that up.

Colby: 1:06:12

No, and we need to. So again. I mean one of the I think the broad messages of this conversation has been that we need to understand our subject more, more and more. And it’s through understanding our subject that we can tailor our responses better and more therapeutically to them.

Laura: 1:06:37

Yeah, and I, when I first started working in that first residential treatment center, I knew very quickly I did not know enough to be doing that work and I didn’t get the sense that people around about me knew enough either. Like, yeah, and I now I feel that even more so. Do you know? Like, the more you know, the more you know you don’t know, kind of thing Like there’s and it’s such complex work, it’s such complex work, yeah.

Colby: 1:07:06

Yeah Well, I better let you go. You’ve got your day ahead of you, I’ve got my evening ahead of me. But one last thing I would love to speak to you again, and I would love to speak about the topic of attunement, and me too.

Colby: 1:07:24

Let’s do that I I thought I would just leave you with one one thought, one reflection. You know the, the um, the still face experiments, yeah, you’re familiar with, yeah, and there’s the famous that there’s a, there’s kind of like a famous video that you can lift off of the internet yes, I use it in my teaching yeah, yeah, yeah. So, um, at where it’s what’s one, it’s the all one of the authors of it. Um, he’s kind of narrating the, the video, you know the one yeah, I mean everyone.

Laura: 1:07:57

I can’t think of his name.

Colby: 1:07:58

No, I’m having a mental blank. Now everyone, um, when I because I use I use it in my training as well I get, I get people to. I’ve warned people, it’s very distressing, bloody blah. But what I want you to do is notice what is the mum’s first response to the baby yeah, so that what when she comes out of still face? So, um, if people are don’t know what we’re talking about, you can go. If you, if you go onto youtube and do and type in still face experiment, you’re likely to get the video we’re talking about anyway. So you know mum, mum’s playing and interacting with her child, and and and they’re, you know they’re in sync, they’re attuned to each other, and then mum looks away, as you know, and she looks and she looks back and she’s um, still face. Now, this is, this was advice that was doled out, you know, and maybe still is that you know when a child is escalating, what you should do is just give them no emotional reaction at all.

Laura: 1:09:10

Yes, and that probably has caused some restraints, even in my own practice, and you know, and some people then maybe even become more wooden as part of their coping because they don’t want counter-aggression to be coming through, or they naturally shut down when they’re feeling threatened.

Laura: 1:09:29

Right, and at those moments that child becomes, we are, we are so much on the same wavelength with this because I teach about this in my and that child is like I need you and reaching that baby, right, and the baby becomes completely uncontained, so much so that she loses her physical posture, she even becomes contained, uncontained physically, and that it.

Laura: 1:09:58

And then you could link it with shame too, in terms of like being cast out and like the deep, fundamental, like sociological understanding of shame, and that a relational repair or the minute, the because you said but what does the mom do as soon as she’s allowed to come out of still face? It’s that relational repair or that connection that she immediately connects to that child. So if we can stay connected to that child during that escalation, we may have a much better chance of it, of that child not becoming more uncontained, rather than and our uncontainment may look different as we become more wooden, trying to be professional, and certainly when I start working in the field, it was like being professional meant being detached, especially in provocative situations, whereas it actually might help to say, god, I’m really frustrated right now and I don’t know how to help you, absolutely so the child.

Colby: 1:10:54

The child will be when you, when you give them nothing, they will escalate, because they’re looking for you to feel what they feel Exactly. They’re looking for attunement. And you give them nothing and they just keep escalating. And the poor baby in the still face, she’s just escalating. But then I think about mum. What’s mum likely to be thinking at that time? So, mum’s, as you watch her, and it gets closer to when she can come out of still face, she just starts blinking really rapidly.

Laura: 1:11:25

Does she, she does, she blinks a lot Nice observation.

Colby: 1:11:28

And then she comes out and I say to everyone in the talks that I give you know what’s mum’s first reaction? And they say say she’s happy, and I, and so I play it back and I play it again and her first reaction is well, starts with the blinking of the eyes before she even comes out, and her first one reaction she comes out is oh my baby.

Laura: 1:12:09

Out is oh my baby my baby, there you are, ah, mommy’s here, yes, yes, but she starts at attunement. She’s because it’s not hard for her, because she feels terrible. The baby feels terrible, and so does she yeah, because she she becomes more uncontained or more dysregulated. Um, as the baby goes up, she has a similar and yeah, and it’s like, oh, and then they both and the baby goes whoop straight back.

Colby: 1:12:30

As soon as mom sounds her self-distressed, baby goes whoosh.

Laura: 1:12:36

It’s before she even goes into that little bit and their bodies are having this dance of attunement and this relief almost. I always think of it as she’s relieved to be able to get out of that still face and stuff. Yeah, yeah isn’t that interesting. We both use that um and had similar things that we see, because that’s not what they were. They were studying baby sociability but, you know, whatever lens you’re looking at it through, you might see and have different ways of understanding what’s happening there.

Colby: 1:13:07

Yeah, yeah, well, I like looking at theories and coming up with a different theory about the theory, and we all have them right like yeah yeah, and people who are a theoretical.

Laura: 1:13:20

They still have theories about like what this child needs a swift kick up the backside. That is their working theory.

Colby: 1:13:27

They might not be aware of it, but we all have them yeah yeah, we might as well get better and better at good ones and using them yeah, it took us a while to talk about containment theory and people that know you might think well that you did well there, but we didn’t talk about attachment and, uh, people might think that’s remarkable of me in the, in the circumstances, um, I’ll leave you with this. There’s a pro, there’s a prologue to each of my editions of um, of the attachment books, the, the. There’s only two editions, but the first one, it’s a tale of three mice. The second one it’s a tale of four mice and they’re both attachment stories but they’re both skinner’s operant condition paradigm and I’ve been waiting for someone to take me to task for the last 15 years or 16 years.

Colby: 1:14:22

But because our children are very much like the intermittently reinforced rats in Skinner’s experiment. So anyway, I’ll leave it with you to have a bit of a look at what I’m talking about. But again, me, everyone you know, looked at Skinner’s work and it was all about, you know, consistent reinforcement and you know, and optimal for learning. And I looked at it and thought, no, I want to know about those kids that couldn’t rely on the. You know, those rats that couldn’t rely on the rat.

Laura: 1:14:52

Yeah, yeah, that was a more powerful memory was the inconsistent yeah, yeah, that’s like our kids.

Colby: 1:14:59

Yeah, that’s like our kids, it’s like our kids. Yeah, anyway, it was lovely to speak to you. Let’s do it again another time.

Laura: 1:15:08

Yep, I’m happy to follow up with some of those things we talked about and connect you with ruth, maybe yeah, yes, yes, I want send me the, send me the names, please. Okay.

Colby: 1:15:19

Okay, thank you, bye-bye, bye.

The Science of Prevention: How We Can End Child Maltreatment, with Benjamin Perks

The Importance of Attachment and the Science of Prevention in Child Development

In a recent podcast episode, Benjamin Perks, Head of Campaigns and Advocacy at UNICEF, shared profound insights about child development, attachment theory, and the global effort to end child maltreatment. His personal journey from growing up in residential care to becoming a leader in child protection provides a powerful narrative that underscores the importance of positive relationships in childhood development.

Ben emphasizes the concept of the “Four S’s” – secure, safe, seen, and soothed – as essential elements that every child needs to flourish. When children receive these four elements from their family, they develop resilience that protects them from adverse experiences in other environments. When family support is lacking, schools become the critical secondary buffer. The ideal situation, according to Ben, is having all three systems – family, school, and community – committed to ensuring every child experiences these four essential elements. What makes this particularly significant is that we are the first generation in history with the knowledge and resources to ensure universal access to these developmental necessities.

The podcast highlights the alarming prevalence of Adverse Childhood Experiences (ACEs) and their long-term impact. According to the Center for Disease Control in the United States, each adverse childhood experience significantly increases the risk of negative outcomes across 40 different well-being indicators, from addiction to poor mental health to involvement in crime. This intergenerational cycle of trauma creates what Ben refers to as “relational poverty” – the inability to form healthy relationships due to lack of early relational skills development. This pattern is observable not just in humans but across species, where similar patterns of attachment and development have been documented.

One of the most compelling arguments Ben presents is that child maltreatment can be ended through a public health approach similar to how child mortality was dramatically reduced globally. In the 1980s, when 14-15 million children died annually from preventable diseases, a targeted approach implementing four simple interventions (vaccinations, oral rehydration salts, growth monitoring, and breastfeeding promotion) reduced child mortality by 61% over a decade. Ben proposes that with similar determination and a few key interventions, we could achieve comparable results in reducing child maltreatment.

These key interventions include universal access to evidence-based parenting programs, extended parental leave, universal preschool from age three, and widespread public education about child development and trauma. According to the UN Special Representative on violence against children, while child maltreatment costs societies up to 12% of GDP through various social costs, implementing these preventative measures would cost less than 1% of GDP – making it not just a moral imperative but an economic one as well.

The podcast also explores the complex nature of intergenerational trauma, including collective trauma experienced by communities that have faced historical oppression. As Resmaa Menakem notes, people maladapt to contexts that are passed through generations; the context is forgotten, but the adaptations become culture. This perspective helps explain how trauma patterns persist in communities long after the original traumatic conditions have changed.

Ben’s’ own healing journey demonstrates that recovery is possible at any age. After recognizing the impact of his childhood experiences on his adult life, he underwent therapy that transformed his world “from black and white to color.” This personal transformation enabled him to break the cycle of insecure attachment with his own son, demonstrating that with appropriate intervention, intergenerational patterns can be disrupted. His book, “Trauma Proof: Healing, Attachment and the Science of Prevention,” combines scientific research with personal narratives of healing from around the world, offering both inspiration and practical approaches to addressing childhood trauma.

You can listen to the podcast here:

You can watch here:

About Ben:

Benjamin Perks is the Head of Campaigns and Advocacy in the Division of Global Communications and Advocacy at the United Nations Children’s Fund, based in New York. He leads public and policy advocacy on the development and protection of children. He previously served in human rights diplomacy roles as the UNICEF Representative and UN Resident Coordinator ad interim to both the Republic of North Macedonia and the Republic of Montenegro. In both capacities he advocated for reforms to fulfil international human rights commitments and realization of the Sustainable Development Goals. He has served in Georgia, Kosovo, Afghanistan, India and Albania. He coordinated the Back-to-School campaign in the Northern Afghanistan which brought 3 million children, including 1 million girls, into school-most of them for the first times in their lives. He has led work on demobilization of child solders, deinstitutionalization of children in state care, addressing child poverty, pre-school expansion and disability inclusion.

Related Podcast Episodes:

Professor Julie Taylor:

Listen here:

Watch here:

Transcript:

Colby: 0:01

Welcome to the Secure Start podcast.

Ben: 0:04

This teacher took me under her wing and made a connection with me, and I say in the book that she’s the first adult that I think I really had a proper conversation with. If you grew up without family, your relational skill you have relational poverty. Your relational skills are poor often. Poverty, relational skills are poor often. So family is the primary buffer in that, when family is not able to provide that buffer, school is the next best option.

Ben: 0:34

And what’s really important in relation to my work is that we got the first generation history that can ensure that every parent is able to give the child the four S’s and that every school is able to do that too. But we now know that with three or four, similarly, with three or four simple interventions, we could dramatically reduce child trauma, child maltreatment, risk of trauma. I also think that child maltreatment is something that drives a number of social costs. According to the special representative of the Secretary General of the UN on violence against children, he says it costs us up to 12% of GDP, but the interventions I’m suggesting we make globally available will be less than 1% of GDP. We must be the last generation to see violence against children, maltreatment and trauma as being insurmountable social problems.

Colby: 1:33

Welcome to the Secure Start podcast. I’m Colby Pearce, and my guest for this episode is a global leader in child development and protection. Before I introduce my guests, I’d just like to acknowledge the Ngarrindjeri people of the Lower Murray Lakes and Coorong, on whose land that I’m coming to this podcast from, and I’d like to acknowledge the continuing connection the living Ngarrindjeri people feel to land, waters, culture and community. I’d also like to pay my respects to their elders, past, present and emerging. My guest this episode is Benjamin Perks, benjamin Perks.

Colby: 2:28

Ben is Head of Campaigns and Advocacy in the Division of Global Communication and Advocacy at the United Nations Children Fund, based in New York. He leads public and policy advocacy on the development and protection of children. Ben previously served in human rights diplomacy roles as the UNICEF representative and UN resident coordinator at interim to both the Republic of North Macedonia and the Republic of Montenegro. In both capacities he advocated for reforms to fulfil international human rights commitments and realisation of the Sustainable Development Goals. Ben has served in Georgia, kosovo, afghanistan, india and Albania. He coordinated the Back to School campaign in northern Afghanistan, which brought three million children, including 1 million girls, into school, most of them for the first time in their lives. He has led work on demobilisation of child soldiers, deinstitutionalisation of children in state care, addressing child poverty, addressing child poverty, preschool expansion and disability inclusion.

Colby: 3:47

Ben is Senior Fellow at the Jubilee Centre at the University of Birmingham in the UK, which researches education policy on character, social and emotional development of children, and he is an Associate Faculty Member at Oxford University Department of Social Policy and Innovation. Ben is recognised as a public speaker and campaigner on child development and protection. His book Trauma Proof Healing, attachment and the Science of Prevention is out now.

Ben: 4:22

Welcome, ben. Thank you very much, colby. It’s great to be with you, connecting from New York to you in Australia. I’m very glad to be on your podcast.

Colby: 4:34

Yeah, thank you, owen. Thank you very much for agreeing to be on, and I was just wondering and I give all my guests this opportunity is there anything that you’d like to add to that bio of your work?Ben: 4:48

yeah, a couple of other things. I I lead globally for the un on international day of play, which is a new ua, the outcome of a new un resolution, and obviously play is central to child development and child protection. So I’ll be talking about that, I guess, a little bit in the conversation today. But also just to add that everything I talk about today and everything that I’ve written in my book is in a personal capacity. I’m not speaking on behalf of the UN or UNICEF or anybody apart from myself today, so I just wanted to to be clear on that as well. Yeah, excellent.

Colby: 5:23

Terrific. So, ben, tell us how you got into this work that you’re, this really important work that you’re doing and have done across your career.

Ben: 5:34

I think there are three kind of major turning points. I think the first one is that I was in. I grew up the second half of my childhood in residential care in children’s homes. I was in. I grew up the second half of my childhood in residential care in children’s homes. I was in Birmingham and in London. I lived a lot on the streets, I ran away a lot, I was involved with gangs and other kinds of kinds of activities. And then suddenly at 16, I had the opportunity to become an activist in London for the rights of young people in care. And that’s my first job, my first serious job at the age of 16, a full-time activist. Um, so, so that was how I became a campaigner. That’s how a campaigner was born, I think.

Ben: 6:15

And then, secondly, a few years later, when I was at university, it was very rare for somebody from a children’s home to go to university in the UK. Uh, in those days it’s still quite rare, but it’s uh, the prospects are a little bit better now than they were back in my day. But I was really passionate at university about Martin Luther King and the civil rights movement and Gandhi. I read endlessly about their work to change the situation of segregation and structural racism in the United States. Also the effort of Gandhi to build a movement against colonialism, the passive resistance and all of this very well-disciplined campaign work, and that made me really think that I want to dedicate my life to real change, not performative work but real change that delivers outcomes. And one of my heroes in the civil rights history of the United States was a guy called Ralph Bunch who was a big figure, an African-American guy who became a big figure in the early days of the United Nations and he became kind of a hero to me and I then thought about a career in the UN.

Ben: 7:29

So at the end of my first year at university I somehow managed to organise to go to Croatia and there was a middle of a conflict Croatia and Bosnia and Croatia. I somehow went on the bus to Croatia and kind of talked my way in to a role, a temporary role, in UNICEF, and took a year out and worked on that and I was hooked. So I I had very much of like a bog standard UNICEF kind of career. I I did very well I, when I finished my master’s degree a few years later I went back to the organization and, you know, worked my way up towards being a head of office and all of that.

Ben: 8:12

But finally when, when I became a head of office, you know, in a formal diplomatic UN role I was at a meeting where there was a conversation about deinstitutionalization and somebody was talking about attachment research and I heard it for the first time. I was sitting there and I realized the guy who was talking, the professor, was talking about the outcome, the adult outcomes, of insecure attachment in childhood relationships. All of that and I saw myself in everything that he was saying. So I went into a period of therapy for a year and then I became a passionate campaigner on issues like child trauma, attachment, and that’s the journey that brought me to write the book and that added another very personal stream of work to the work I’d already been doing on children’s rights. Very long-winded answer, but those three points were crucial in bringing me to where I am now.

Colby: 9:13

Yeah, that’s awesome and I also am a little bit interested in attachment as well and written a bit about it. But do you remember the name of the fellow who who, um, first introduced you to attachment?

Ben: 9:28

but that’s yes, you know, I’m getting to an age where I think that I forget things, so it’s uh, it’s uh, it’s professor from uh university of nottingham, and it will come back to me during the course of the conversation and I’ll probably blurt it out when it comes back to me okay, awesome, so I’m just queuing your recall for that, perhaps at a later date.

Colby: 9:50

You’ve talked a bit about influences in terms of your circumstances and the roles that you’ve gotten into. Are there any people that really stand out for you as having played a role and been a big influence over your career development? And you’ve mentioned attachment. Maybe you can tell us why you think attachment is so important in your work as well so well in terms of, um, in terms of people that have influenced me.

Ben: 10:23

I write a lot in my book. My book tells lots of stories of different people, but I write a bit about my own as well, and one of the things that was transformative for me was I had a teacher when I was 15. I’d been thrown out of school. I had a best friend who’d been killed in a knife fight. I I had, uh, I was in a very tense inner city poverty care, you know situation, no parents or anything like that. But this teacher, um, somehow, in this, in his school for kids that have been kicked out of school, this teacher took me under under her wing and made a connection with me, and I say in the book that she’s the first adult that I think I really had a proper conversation with as a child.

Ben: 11:08

I was 15. And her name is Jan Report. And when I had this moment, when I listened to this professor from Nottingham giving this talk about attachment, at the end of it I went into this process of therapy. But I also tracked down my teacher in that process, because I wanted to go back and tell her what I’d done with my life and I would have done none of it without her. And so I went back and met her, having not seen her since childhood, and that was incredible. And now now every year when we go back to the UK, we go and see her. I took my son to meet her last year and so so that’s a really pivotal person.

Ben: 11:52

I also had a great social worker. At one point there was a good residential social worker in the children’s home. I had a couple of good friendships when I was young and also eventually also became kind of connected to a family that had reached out over some campaigning work that I was doing. I think that makes all the difference, because if you grow up in a without family, your relational skill you have relational poverty. Your relational skills are poor often and so you know, because you just don’t. It’s like a muscle. You have to grow relational skills and I hadn’t so many things that people learn in a family. I hadn’t really learned them.

Colby: 12:35

I grew up in a, in a survival mode, um, but somehow I managed to have these friendships and uh, attract this support and engagement, and I think all of it meant the world to me and I wouldn’t be here today without those people yeah, that’s an awesome story and it puts me in mind of two things the, the idea that comes from the one good adult research, that that all the child needs is one adult who believes in them, who’s’s there for them, who truly listens to them and helps them. And then there’s the other idea, which is that it takes a village. Now, I think both of those concepts they may be seen as being mutually exclusive, but I think that they sit comfortably alongside each other. The one helps the other, particularly the one good adult helps the other. I do think that when children grow up in adversity relational adversity the more good relationships they have, the better the outcomes.

Colby: 13:40

And I was speaking to someone relatively recently and apologies if you’re listening, and it was you and I can’t remember who it was, but he talked about that it takes a village. The construct at the very beginning was referring to, or at least meant to take into account, peer relationships, so that the important role of peers in children’s up, children growing up and and and I can see how that fits with with social learning theory, for example. So I guess, attachment theory what is it about attachment theory that has influenced your, your career since that introduction?

Ben: 14:24

I want to come back to what you were just saying about peers, community, trusted adult and then lead that into the conversation about attachment and how that influences my work. So I think that you know Dr Daniel Segal and Tina Penny Bryson have this brilliant expression of I think it comes from them the four A’s, sorry, the four S’s. So it’s to be secure, safe, seen and soothed. And the idea is that for children to flourish they need to have those four S’s. If a child has them at home with the family, that’s really important, particularly for early development, uh, early childhood development, to set that secure base and safe haven. We know that early experiences we don’t remember things that happened to us before the age of two, but they are disproportionately and massively influential on the way we see the world for the rest of our life and for the opportunities that we will have and the constraints that we will have.

Ben: 15:32

So that’s really important in the family.Ben: 15:34

But if a child is not safe, seen, soothed and secure in the family, then if they have the four S’s in school, that can help to some extent to heal and prevent them going on a trajectory that is driven by trauma and toxic stress and help them to build relationships and so on.

Ben: 15:58

That’s why the teacher was so important to me by reverse, if children are safe, seen, secure and suited at home and then they go to a rough school, that resilience that they get from the forest is at home will protect them from the trauma of the school or a war zone or a gang infested neighborhood. So family is the primary buffer um in that when family is not um able to provide that buffer, school is the next best option. Certainly it’s the community um. But the idea, the ideal world is you want to have all three of those things family, school, community, committed to, intentional about ensuring that every child is secure, safe, safe, seen and soothed. And what’s really important in relation to my work is that we are the first generation in history that can ensure that every parent is able to give the child, the four S’s, and that every school is able to do that too, and we know that that can be achieved for a fraction of what is lost by not doing it. That’s how it influences my work, yeah.

Colby: 17:12

Awesome. I understand from your work you have a powerful belief that we can end child maltreatment. Tell us a little bit more about why you think that to be the case.

Ben: 17:27

Let me tell you another story that brings me back to this. In 1980, and I talk about this in the book in 1980, in University of Birmingham in the UK, an American public health professional delivered a paper in which he argued that we could I think 14 or 15 million children die every year from preventable disease that if we could just do four things if we could vaccinate every child globally, if we could provide oral rehydration salts to treat diarrheal diseases which can be deadly, if we could monitor the growth of children and if we could promote breastfeeding, then we could dramatically reduce that. Unicef and WHO got hold of that paper and had a really complex internal conversation with many people against the idea, but some of them championed the idea of making this a reality. And over the next 10 years they mobilized a coalition of royals, of heads of state, of community organizations, of religious leaders all around the world and they increased vaccine coverage, for example, from 15% of the world’s children to around 85% of the world’s children and in the decade that followed, child mortality under five mortality reduced by 61%. Everybody thought they were crazy in the beginning. Everybody thought that this was insurmountable, but they did it. And if you look back on every single um global achievement, whether it’s a massive expansion of education, whether it’s massive expansion of availability to um, to to clean water, or prevention of child labor or child marriage. There has been a really audacious drive to do that.

Ben: 19:21

Um, child maltreatment is something that is a problem everywhere. It’s not just in the global south, it’s a problem everywhere. But we now know that with three or four, similarly, with three or four simple interventions, we could dramatically reduce child trauma, child maltreatment, risk of trauma, toxic stress, all of that. Things like universal access to evidence-based parenting programs, a minimum package of parenting programs that we now know, through systematic review, can improve child outcomes, reduce risk and maltreatment and even improve parental mental health outcomes. Secondly, parental leave making parental leave a universal norm, dramatically increasing parental leave, recognising it as a public good. Thirdly, ensuring that children from the age of three in preschool are in schools where they are safe and secure and seen and soothed.

Ben: 20:22

And fourthly, making people aware. If you think about it, people are aware of influenza or the common cold or how to manage a knee injury. Right, they know this stuff. It’s part of family conversation, it’s something that’s common knowledge. Really, child maltreatment, trauma and all of that is no more complex than the transmission of influenza. It’s not more complex. It is shrouded in taboo and stigma and shame and myth. But we can break all of those myths. We can break all of those constraints and make it something where everybody’s aware of the basics to underpin those changes.

Ben: 21:01

With those interventions, I believe we could dramatically reduce child maltreatment. I also think that child maltreatment is something that drives a number of social costs, right From addiction to poor mental health, to risk of being a perpetrator or victim of all kinds of violence, from gang violence to political violence to domestic violence. It puts us at risk of poor health and poor learning outcomes. And all of that, according to the special representative of the Secretary General of the UN on violence against children, says it costs us up to 12% of GDP, but the interventions that I’m suggesting we make globally available will be less than 1% of GDP. So we lose trillions by not addressing problems before they occur at scale, and that’s something I think we’re the first generation to be able to do that, and I think, because of that, we must be the last generation to see violence against children, maltreatment and trauma as being insurmountable social problems.

Colby: 22:09

Yeah, yeah, that’s terrific. While you were speaking there, my mind was going to what the universal parental education would look like, what the intervention into schools might look like. I wonder if you would comment on each of those things.

Ben: 22:39

Sure. So in terms of the parental parenting programs, they can be delivered in a number of ways In some countries because they already are available in about 25% of countries targeted not universal Right and what? The most common format is a home visit. That home visit often it’s bundled with a health visit, and so a home visitor comes and talks to you about health things like vaccines and nutrition, but also talks to you about play, engagement, positive discipline and all of that, and often a minimum package of that. A few visits in early childhood and then, like booster sessions, critical milestones like before adolescence can make all the difference. You know as an attachment expert that Bowlby and Ainsworth said that when a parent is able to either process their own insecure attachment or come up with a strategy for parenting, they’re much less likely to transmit it. And who and oxford university and unicef and others have done a vast systematic review with um hundreds of random I think 460 randomized controlled trials all over the world and found that parenting programs really make a difference. So there should be a minimum package of visits, but then progressive, in the sense that those that need more support can get more visits. This can also be backed up by things like group sessions. In South Africa, for example, they have group sessions for parents, but also grandparents, to talk about how they can ensure the best outcomes for their children. Also, apps are beginning to show real breakthroughs. There are some apps. I think there’s an app in India that reaches 20 million people. Unicef has an app called Bebo. There are many different apps which are actually really helpful for parents who are trying to access evidence based information. So I think you can have an ecosystem that has all of these things, with quality control supported by organizations like UNICEF, who and others.

Ben: 25:11

In terms of parental leave, I think every country in the world should be having a very minimum WHO standard of six months for the birth parent and four months for the other parent, but it could be all foster parents as well, or adoptive parents. I think it should be much more. The Scandinavian countries are showing a really good model for that um. I think that’s really important. Then, having family-friendly workplaces attached to that is also a part of that, that package.

Ben: 25:29

And then schools really having um systems in place where teachers would create a system where where where children are seen and safe and secure, and where teachers are aware of trauma. They’re aware of the prevalence of trauma, because in an average classroom of 30 kids, half of the kids have experienced an adverse childhood experience, a risk factor for trauma and toxic stress. So you know, this idea from the past that you know it’s one or two kids in a class that are in touch with the social work system that are the really vulnerable kids is wrong, recognising that it is across the board and what we need to do is make sure that kids have a strong sense of belonging and uh, um and you know uh, connection with a teacher and, as you mentioned earlier, peers.

Colby: 26:28

the peers thing is really important in adolescence because, of course, in adolescence, it’s peer relationships that are the most important thing for children yeah, yeah, thank you, and um, have you had an opportunity to observe or otherwise get a sense of what the uptake of these measures might be across Western and non-Western countries, jurisdictions, western and non-Western?

Ben: 27:01

countries, jurisdictions. Yeah, I think there’s a lot of enthusiasm, very little resistance to parenting programs, which is interesting because a parenting program often is like going into the house, going into the home, but there’s a lot of hunger for parenting skills. You know, I think increasingly the world is talking about the fact that many of us grow up with intergenerational issues of trauma or or neglect at home. Um, and then even people that haven’t got that want to know what’s the best way of securing the best future for their kid. So I see a lot of um support and interest and very little resistance. I I speak to people that I interview, people in the book that are receiving parenting programmes, people that deliver them, for example, and there’s a lot of interest and I think it’s just a question of making it a normal thing, normal part of childhood, a normal part of parenting, the way that vaccines is or the way that schools are.

Colby: 28:02

Yeah, sometimes I talk about how birds don’t have bird parenting experts that teach them how to raise their birds, and neither do wolves or, you know, even the other great apes. So there is that view that parental advice and guidance is really not necessary, that we are meant to be the most sophisticated, uh, of at least of the great apes, if not of the whole entire animal kingdom, on this. How, why, why can’t, why do we need parenting experts? We, we’ve, you know, we’ve been parented ourselves. We’ve learned from the things that our parents do well and the things that our parents don’t do so well. Um, and we, we must have a, an inbred instinct, just like other members of the animal kingdom. Do what? What would you say to that?

Ben: 29:14

well, they do research on rats I think it’s. My community does research on rats and what they do is they see the same patterns of poor attachment in other animals and they see that those that are licked and groomed by their parent have much better outcomes, are much more likely to go out into the world and be a success by rat standards, right, and so it’s the same as humans. You know it’s the same as humans. We know that humans that don’t grow up with a strong sense of being safe and loved are more likely to have poorer interpersonal relationships, are more likely to do poorly in school, to be addicted, to have all of these problems.

Ben: 30:03

You know the Center for Disease Control in the United States, the major public health institution, has an index of 40 different well-being indicators, from suicide to osteoporosis to addiction, everything, everything, and there’s almost a step increase every risk of negative outcome for every adverse childhood experience a person has had. So somebody that has been suffered emotional neglect emotional via verbal violence, for example, and physical violence and witness domestic violence, for example these are four things quite common, all of them very common is multiple times more likely to have a poor outcome across all of those 40 well-being indicators. So that’s why really I think we do have an instinct, that’s why really I think we do have an instinct, but for maybe at least 40% of us, that instinct is driven by intergenerational trauma, toxic stress, neglect and violence.

Colby: 31:18

And we, now that we know because we didn’t know throughout history, now that we we know, we should be able to stop that cycle and make people you know, ensure that people can flourish yeah, it put me in mind of when you were talking about the rats, because when I’m delivering training, I’ll uh, I will talk also about another group of rats, the rats that were in skinner’s operant conditioning experiments. And people go oh, aren’t you supposed to be an attachment person rather than a behavioural person, when, in actual fact, there should be a lot. In my view, and this is what Bowlby did there should be a lot more cross-fertilisation of ideas and theories and knowledge, rather than siloing of ideas and theories and knowledge, rather than siloing Skinner with his rat experiments and the operant conditioning paradigm. It was really quite interesting because, though he didn’t go down that path at least not that I’m aware of there is a group of rats and pigeons in his research that are very much like our children, who’ve experienced grossly inadequate care, and they’re the rats and pigeons who are in an inconsistent reinforcement paradigm. They got their needs met inconsistently in response to a gesture, and the gesture was to either peck a button or push down on a lever, and the operant conditionings paradigm teaches us a lot about learning and adjustment in those circumstances. So and I also, while you were talking, I was thinking about a conversation I had with a previous guest. It may actually have been a YouTube video, I’m not sure which.

Colby: 33:07

But talking about these now, I’m hoping I’m not going to butcher it, but I think they were mosquitoes. You can put mosquitoes into a jar and they try to get out of the jar. You put all these, but if you, and if you so, they kind of go up and down in the jar. Now, if you put some clear film halfway up the jar, that prevents them going all the way to the top and and getting out after a while, you can take the clear film away and they’ll never try and jump out of the jar. They just go up and down, and that’s really interesting, I guess, until and you think, well, you know, they’ve just learnt that that’s as high as they can go.

Colby: 33:58

Well, this is where it gets really interesting, which is that their offspring also only jump as high. So their offspring don’t go out of the, notwithstanding that there’s no longer a clear film to stop them from getting out. They only go as high as their parents do, and I think that’s. You’ve spoken a little bit about the cost of child maltreatment, but that seems to bear quite significantly. Uh as well. Uh, on that, that issue, that, um. You know, what are we transmitting down through the generations?

Ben: 34:39

the, the positive psychologists, I think, would describe what you’ve just described as learned helplessness, seligman would. That’s what happens. I think that happens often with communities already beaten down. Yeah, I think that. Yeah, I guess that it’s obvious now from psychology, from neuroscience, from population level data, that a lot of these things are intergenerational, that you know they are acquired characteristics from you know that are transmitted through the culture of families.

Ben: 35:28

And, of course, resmei Mannequin, who’s a leading scholar on mental health and race in the United States, says it really well. He says that you know that people respond. He’s talking often about racism and slavery in the United States, but people respond. He’s talking often about racism and slavery in the United States, but people respond they maladapt to a context that’s passed on through generations. The context is forgotten and it becomes the culture, and I think that’s something that is often seen in communities that have been oppressed and affected by collective trauma, if they don’t have the, the holocaust and slavery and also the situation of the native American Indians and the boarding schools, which would have a lot in common with um, with with the um, aboriginal, uh and Torres Strait Islander community in Australia I hope I’m saying that correctly in Australia, um, I think, I think there’s a there’s also. We think, as well as thinking about individual, um trauma, we also need to think about communal trauma.

Colby: 36:48

Yeah, yeah, and I think the the other thing that was, I guess. Well, the thing that was going through my mind as well in relation to the, the mosquito story is I is that we can’t do nothing If we do nothing. It just gets, as you say, transmitted, transmitted through the generations. But if we can but it might be too simplistic to say this but if you can change the course or the trajectory of one generation, then you end up with perhaps a multi-generational change of trajectory. So when you talk about we had the opportunity to end child maltreatment, and the impact of doing that and the importance of that endeavour really is not just for those children and young people who otherwise would have had quite an adverse experience growing up, but you’re changing the trajectory for their life partners, their children and their grandchildren. So yeah.

Ben: 38:06

So if you look at an issue like crime, if you go to most juvenile justice facilities, the young people that are involved in crime continuously, and serious crime, over 90% have four or more adverse childhood experiences.

Ben: 38:29

If you could, um prevent adverse childhood experiences before they occur, um, from what we can see, it would have a dramatic increase on propensity to commit crime, to be involved in violence, to take risk, because risk is related to the adolescent brain.

Ben: 38:49

You know it’s adolescent brain development, right? So you have. If you have this toxic combination of poor attachment and trauma in early childhood crashing against the really complex process of adolescent brain development, you have this really high risk and almost all children at very serious risk of being exploited or being involved in crime or violence are coming from those kind of backgrounds. If you speak to people that dealt with the Epstein case the girls that were targeted or if you look at radicalisation, or look at the kind of people that end up in far right groups or people that end up addicted or victims of grooming, almost exclusively coming from very high ace backgrounds, if you could eradicate most forms of adversity by ensuring that children have the four S’s in both the family and school and community early on, then you’re going to completely transform all of those risks across society, making society a much better place for the future and for future generations.

Colby: 40:08

Yes, yeah, and one of my earlier guests was Graeme Kerridge, who has had perhaps a not dissimilar career history, as you have, except in other organisations, but he was very interesting. We’ve had a number of people who have an economics background on this on this podcast, who, um, who moved into the, this social care, uh, into the social care arena and but anyway he, graham carriage, was very interested in human capital as part of his economic background and again, this really ties in with what we’re talking about. This idea of human capital is the human capital gains of reducing or eliminating the prevalence of adverse childhood experiences is significant. Yeah, yeah, you’ve mentioned your book. Well, I mentioned it first, but then you mentioned your book a few times Trauma proof, and let me read the healing attachment and the science of prevention. And let me read the Healing Attachment and the Science of Prevention.

Colby: 41:33

I think I’ve butchered it every single time. I’ve tried to say it. But tell us about your book. Tell us. You’ve mentioned stories. I’m getting really excited about reading it now. So there you go. I haven’t read it yet, but I only just recently learned that it was already out, so I’m looking forward to it. But tell us a bit about your book and who you think it would be of most interest and usefulness to.

Ben: 42:07

Well, the first thing is I probably need a new title if it doesn’t slip off the tongue so easily, because it won’t get that kind of contagion, don’t worry about it.

Colby: 42:18

It’s not unusual for me to struggle with verbal fluency. It’s pretty, it’s a bit embarrassing being both verbose and not particularly verbally fluent.

Ben: 42:34

Oh, you’re doing fine, yeah. So I wanted to write a book that would present this argument that you could end child maltreatment, and you bring all the data together, the economics of it and all of that and all the science. So I talk about the history of attachment theory and, and, uh, the evolution of aces and our understanding of toxic stress, um, some of the economic arguments about return on investment. That comes from james james heckman at university of chicago. Loads and loads of science, but I also do lots of storytelling. Um, when I went to the agent and the publisher and said I want to do a book about how you end child maltreatment, they said that’s great, but you need to include something else as well, which is you’ve got something to say about how people heal, right, how you healed and how others heal. So it has to be about healing and prevention and attachment. So the book, in addition to putting forward the idea that we can end child maltreatment, it also argues the case that we can heal at any age. Almost everybody can go through some kind of healing process and, as a result of that um have a much better quality of life. So every chapter tells a story of somebody and the stories are from all over the world, um. So the first part of the book is really focused on kind of the, the, the, the prevalence of uh, child maltreatment, the parameters of it, what we know about it. The second part is really focused on parenting and talks about parenting programs and parental leave, but through stories. So, for example, the one on parental leave. I do a comparison between two different families, one in Alabama in the United States, where they have really harsh policies on parental leave, and one in Estonia where they have the most progressive policies in the world, and looks at what happened to the parents through both different processes. Then there’s a part about schools and community and crime. And then there’s a part about collective trauma, societal issues like myth and stigma and taboo. And the final part is really my call to action on what we should be doing about all of this. And it tells something of my own story as well.

Ben: 45:06

My own story about intergenerational the issue of healing and intergenerational trauma is kind of this you know, I lived most of my life as an outwardly successful person who was really not having um. You know the quality of life I would have because of the way that I felt inside, which is completely normal if you grow up without parents. You know, viol, the quality of life I would have because of the way that I felt inside, which is completely normal if you grow up without parents. You know Viola Davis says you grow up with this sense that you’re wrong Not that you’ve done something wrong, but that you are wrong and living with that inside me the whole time, while being outwardly successful and doing well and suppressing it. You know, it was something that I kind of thought was normal and then, when I realized that I lived with all of that trauma inside of me, um, I went through a transformation, through healing, uh, seeing a therapist and changing my life. It felt like the world went from black and white to color, and then when to colour. And then when I got married and we had our son, I held my son in my arms and I just instinctively knew or felt that what happened to me as a child was completely unimaginable to myself. The cycle had just broken. I got what you experts would call an insecure attachment, like I would walk to the end of the earth to protect, love, nurture my son. And that’s something that I thought very consciously of because I’d had to go through a lot of work to become, to become the kind of person that could instinctively feel that um.

Ben: 46:56

So that’s my healing journey, but I talk about lots of other people’s healing journeys as well. There’s a guy that was a gang member in Glasgow who was in prison and went through a process of change. There was a, a woman here from new york that was born into um to a crack affected family. Her parents died, which is very young, um, and she had a teacher that helped her and now she’s a big-time campaigner in washington dc for disadvantaged kids.

Ben: 47:23

All these amazing people, scottish member of parliament, um, who had post-natal depression, who talks publicly about it. All these different, amazing people. I got to interview them also on the Holocaust and slavery and other things, all of that. There’s a famous saying by the writer James Baldwin and I can’t quote it exactly, I’ll probably butt-tread. But you think your suffering and pain is personal, pervasive, pervasive, permanent, personal to you. But then you read dostoevsky or tolstoy and you realize that a couple of hundred years ago elsewhere in the world, people going through the same thing and like putting together these different stories of healing and trauma from all around the world, completely different cultures, but people going through broadly the same thing, I think was really cathartic for me and I think for the people I interviewed as well, and hopefully it’s uplifting for people that would read it.

Colby: 48:21

Awesome. Where can you get a copy most easily?

Ben: 48:26

Well, you know, it’s on uh. It’s on uh kindle audible audio and a hard copy. It’s available, I think, through most good bookshops where you are in australia. I get feedback from people that read in australia and in most places there is a different version in North America because there’s a different publisher. There’s a different audible audiobook in North America and the one in North America went through a second round of editing, came out a bit later, so it’s slightly different, but they’re probably the same thing. So it’s available everywhere, I think.

Colby: 49:07

I hope yeah, if it’s not, let me know you haven’t gone on done what I did. I mean, not long after my first book came out, I was on the internet to look where it was coming out and what people were saying about it.

Ben: 49:20

Yeah, yeah, I do do that. You know it generally had good reviews so far. This has been a very busy year in my regular job with the UN. You know the UN’s gone through a lot of changes and so I haven’t had as much time as I wish to promote it. But I’m going to be doing a bit more of that now. I hope it just came out at the beginning of this year. It came out in April in North America, so it’s relatively new, yeah, yeah terrific.

Colby: 49:51

It’s been awesome to have you on and have a chat to you, Ben, about your life and work. I’ve asked you a lot of questions. Is there anything you’d like to ask me before we wrap up?

Ben: 50:03

What do you think about? You’re an attachment expert. What do you think about the idea that we could be the first generation to end child maltreatment if we have a public health approach to it?

Colby: 50:18

I think, in considering my response, I think we live in slightly different worlds, and what I mean by that by saying that, is that I think where I live and work and I’m not talking about here in Adelaide, south Australia, I’m talking about the level of where I sit in terms of exposure to child maltreatment I think it can be really hard for people to think and believe or even consider that what we’re dealing with every day, what we’re seeing, what we’re immersed in, I would say, can be ended or at least significantly reduced in some way. I think we all believe that if that happened and that happened and that happened, you know we’ve all got ideas about how you could end it. I think the benefit of the argument that you’re making is that it’s a bit like the difference between thinking and metacognition. So thinking is just thinking, as we always do, the thoughts that come into our head, and those thoughts are very much linked to what’s happening, you know, to our experience of ourselves, of our surroundings, of our life, that our thoughts are very much linked to emotion. Metacognition is thinking, about thinking, and it’s that higher order thinking where we’re noticing what we’re thinking, where we’re noticing what we’re experiencing, and at that level, we are less emotionally attached to what we’re noticing as such, and this is the foundation of certain therapeutic traditions that exist now, the foundation of certain therapeutic traditions that that exist now. And so I think the benefit of what you are advocating and talking about is perhaps, um, you’ve had, you you’ve had direct personal experience and I think direct parent personal experiences is very important but you’re able, you, you’ve risen above in a way. You’ve risen above and been able to take that more, that meta view, um, and I think so, I think probably a lot of people in who work in it, in this, in those systems, I think if they had time to be able to go to a metacognitive place, to be able to, and maybe your book will help, maybe your book will be a source of tremendous comfort and inspiration for the workers on the ground.

Colby: 53:32

That’s who I’m really referring to and who I count myself one amongst, is the workers on the ground. I think the book, as you describe it, perhaps will present some hope that there are things that can be done at a systems level or a government level, a country level, an international level, that can make a meaningful impact on child protection. So that’s how I would say it is that I think. I think it’s. It’s probably hard for the people at the coalface to, but uh, but necessary for them to feel like something can be done, because when you’re at the coalface you just think, oh, it’s very hard, yeah that’s a brilliant point.

Ben: 54:31

I gave a talk recently at oxford and do a lot of practitioners there and I was describing this public health approach that I’m promoting. They said, well, what about the family that doesn’t respond to parenting? Or what about this? You know this or that, and they won’t get it? And I think it’s not.

Ben: 54:49

I think what you’re doing with the public health approach is a long-term process. Yes, right, like you, you started off in like 1980 where people thought it was normal, insurmountable, that millions of children died and then, gradually, as pieces were built on the audacity of saying that we can end this, there was a whole system, a public health system in place. Uh, that could protect you, I think. I think it’s like that. I think that you’re, you’re gonna, you know you’re gonna have, with a kind of really public health approach, you can have improvements across the board over time, but you’re always going to have those hard to reach kind of parts of the community that need more work. And I think it’s a long-term process where you change the whole culture of society around the issue over a generation. Yeah, I think that’s the approach, but we have to start the work.

Colby: 55:41

Yeah, look, and I think that in my own jurisdiction here and many jurisdictions, people at the coalface who are on the ground doing child protection work all the time. Morale is often compromised and there is a risk of people becoming quite cynical about the work, and I think it’s and that’s a shame. It’s a shame for them, but it’s also a shame for the people who come into contact with them and you know the families that are struggling, the children who can’t, for a period of time, be safely cared for at home, and I think everyone gets involved in this, wanting to make a difference. We all want it, but sometimes there’s a risk that it can seem like it will never end and there’s a degree of hopelessness.

Colby: 56:49

I think one of the power, powerful thing, messages of what you’re talking about is we’ve done it, we’ve done it before, we’ve done it in other, in other ways, in another, in other areas.

Colby: 57:02

Of course, we haven’t reduced it to zero, we haven’t eradicated all diseases, but we have had a. We have had a good and sustained crack at a number of things and seen a global, a significant global reduction, if not elimination, of um certain ills that that beset us in this life and why not? Child protection as well. And the other thing I think about that message and I often ask guests this later in the podcast I’ve avoided asking you any questions that might come hard up against your role in the UN and not wanting to be seen as speaking on behalf of the UN and not wanting to be seen as speaking on behalf of the UN. But I think a book like yours should be inspirational at multiple levels of the work and in particular, I would say, at the level of the policymakers, the level of government, the level of the policy makers, the level of government. So I think, hope, hope in a direction to get us out of, away from and towards a better future for our children, their children and grandchildren as well.

Ben: 58:27

Thank you very much and, on the back of what you just said, can I just end by saying massive gratitude to all the people that work in the child protection workforce, both in Australia and all around the world. Yeah, terrific.

Colby: 58:43

Thanks, ben, and hope to speak to you again at another time.

Ben: 58:49

Absolutely Thank you. It’s been a real pleasure. Thank you very much, Colby.

From Winnicott’s Piano to Adolescent Minds: Peter Wilson’s Journey

Uncertainty as Strength: Why Not Knowing Matters

Peter Wilson’s journey into the world of child and adolescent psychotherapy is a testament to the power of serendipity and openness to unexpected opportunities. From his initial degree in industrial economics to becoming a founder of Young Minds and working with some of the most influential figures in psychoanalysis, Peter’s career trajectory defies conventional planning and instead follows a path of meaningful coincidences.

What stands out most prominently in Peter’s narrative is his formative experience training at the Anna Freud Centre in London during the 1960s. This period represented something of a golden age for psychoanalytic thinking, with Anna Freud herself still actively involved in the training program. The immersive four-year experience provided Peter with a thorough grounding in psychoanalytic theory, requiring him to deeply engage with Freud’s concepts and apply them in clinical practice with children and adolescents. This foundation shaped his entire professional identity, giving him a lens through which to understand the complexity of human experience and emotional development.

Peter’s reflections on his time at the Pepper Harrow therapeutic community offer a fascinating glimpse into an approach to working with deeply troubled young people that would be nearly impossible to replicate in today’s safeguarding-conscious environment. The therapeutic community model, with its emphasis on communal living, shared responsibility, and psychological understanding, provided a holding environment for young people whose emotional lives were profoundly disrupted. The fact that staff would physically prevent young people from running away—something unthinkable in today’s practice—speaks to how dramatically the landscape of child welfare has shifted over the decades.

Perhaps most thought-provoking is Peter’s upcoming book with its intriguing title, “The Adolescent and the Psychotherapist: Why I Don’t Know Matters.” His celebration of uncertainty represents a powerful counterpoint to the current evidence-based practice paradigm that dominates mental health services. Peter argues persuasively that the adolescent’s “I don’t know” response in therapy is not merely resistance but a genuine reflection of uncertainty that deserves respect rather than frustration. Similarly, he challenges the certainty with which cognitive behavioral therapy is promoted as the treatment of choice, suggesting that such confidence is not justified by the evidence and may in fact represent a dishonesty about the limitations of our knowledge.

Peter’s critique of current mental health service delivery models cuts to the heart of contemporary debates about efficiency, evidence, and effectiveness. His concerns about the Improving Access to Psychological Therapies (IAPT) program and the Health and Social Care Act of 2012 reflect a broader disquiet about how market-based thinking has fragmented services and created competition rather than collaboration between different professional disciplines. Most poignantly, he suggests that young people themselves don’t respond well to CBT, preferring the relational, play-oriented approaches that take longer but may address their needs more effectively.

As Peter reflects on his career, his wish that he had been more assertive and authoritative as a younger man reveals a fascinating tension. While he values the humility of “not knowing” as a therapeutic stance, he also recognizes that sometimes more forceful advocacy is needed to challenge dominant narratives and protect valuable approaches to understanding human distress. This balancing act between openness to uncertainty and confidence in one’s perspective represents a profound challenge for all who work in the helping professions.

You can listen to the podcast here:

You can watch here:

About Peter:

Peter Wilson is a Consultant Child and Adolescent Psychotherapist. He qualified in 1971, having completed his training with Anna Freud in her Centre. Since then, he has worked in a variety of organisations, holding senior positions in all of them. These included three Child Guidance Clinics ( now known as CAMHS), two walk- in Centres for young people, a therapeutic community ( the Peper Harow Community) and the Institute of Psychiatry. Peter founded a national charity, called YoungMinds, the purpose of which was to raise public awareness of children’s mental health and to improve multi- discipline services. Peter later became Clinical Adviser at ThePlace2Be, a national organisation providing counselling services in schools. Peter has maintained a small private child and adolescent psychotherapy practice, and now teaches and provides supervision. He is publishing a book in the autumn, entitled ‘ The Adolescent and the Psychotherapist: why ‘ I don’t’ know’ matters’.

Related Podcast Episodes:

Coming soon.

Transcript:

Colby: 0:00

Welcome to the Secure Start podcast.

Peter: 0:04

Life is really a bunch of serendipities. It really is. And I went where I was wanted and I spent three extraordinary years working as an unattached youth worker walking around the streets of the city that I was in, getting to know young people At that time. Psychoanalysis was kosher. Psychoanalysis was the way you thought Winnicott and I was doing a social work training at the London School of Economics, but he was just mesmerizing. So we come back to England and I then do the four-year course at the Anna Freud Center in London, which was, if you like, like the kind of turning point of my life, because it was a thorough psychoanalytic training and a Freud was still alive and it was in a kind of heyday, really, by saying I don’t know. That opens up our dialogue. People don’t believe in psychoanalysis by and large they don’t. They believe in what’s obvious, what’s said on top. We’re always looking underneath what’s really going on, and I play piano and I played his piano, but I was good, I played Willie Goldspierre.

Colby: 1:28

Welcome to the Secure Start podcast. I’m Colby Pearce, and joining me for this episode is a founder and trailblazer in children’s mental health. Before I introduce my guest, I’d like to acknowledge the traditional custodians of the land that I’m meeting on, the Kaurna people of the Adelaide Plains, and acknowledge the continuing connection the living Kaurna people feel to land, waters, culture and community. I’d also like to pay my respects to their elders, past, present and emerging. My guest this episode is Peter Wilson.

Colby: 2:07

Peter is a consultant child and adolescent psychotherapist. He qualified in 1971, having completed his training with Anna Freud in her centre. Since then, he has worked in a variety of organisations, holding senior positions in all of them. These include three child guidance clinics, now known as CAMHS, two walk-in centres for young people, a therapeutic community, the Pepper Harrow Community, and the Institute of Psychiatry. Peter founded a national charity called Young Minds, the purpose of which was to raise public awareness of children’s mental health and to improve multidiscipline services. Peter later became clinical advisor at the Place to Be, a national organisation providing counselling services in schools. Peter has maintained a small, private child and adolescent psychotherapy practice and now teaches and provides supervision. He is publishing a book in the autumn for him, spring for Me, entitled the Adolescent and the Psychotherapist, why I Don’t Know Matters, welcome Peter.

Peter: 3:33

Hello, thank you very much.

Colby: 3:38

And I should just say at the outset that you’re being a very good sport, not only being on the podcast, but continuing the podcast today, me having made the cardinal error of not sending you the questions beforehand, or at least beforehand long enough for you to consider them. Anyway, hopefully it won’t be too harrowing an experience for you. And I usually just ask my guests is there anything else? Is there anything that you would like to add to that short bio that I’ve just read?

Peter: 4:19

well, I think it covers pretty well much of my life. I think I think it covers pretty well much of my life. I think We’ll have to see. Perhaps at the end I’ll find there’s something I want to say which I haven’t said I have no idea what’s going to happen. So let’s see what happens.

Colby: 4:35

Well, yeah, let’s see Excellent. So, peter, you’ve had a long and very varied career in young people’s mental health and also with the Pepper Harrow community, with therapeutic communities. So I guess my first question to you is how did you get into this line of work? That has been your life’s work.

Peter: 5:06

Oh, completely by accident, I mean pure, pure accident. I mean I knew nothing about psychoanalysis until I was about, I suppose, 20, 21. Um, and I had no aspirations in this direction at all. I mean, I really was quite ignorant. Um, and I had no aspirations in this direction at all. I mean, I really was quite ignorant.

Peter: 5:28

And I went to university and I had my degree in industrial economics, you’ll be pleased to know, of which I knew very little and of which I know very little now. But I did it because I had some kind of ambition to be rich and to be in industry and to be a very grown-up sort of person, as it were. In fact, my life at university was not supremely glorious academically. I spent a lot of time in the drama society. I acted in about 10 different plays, so I was goofing around and very fortunate because in my day only about 5% of the population, general population, went to university. So I was very, very privileged to be there at all. And this was in the when was I that? 1957 to 1960, so you know it’s a long, long time ago. And I, the facilities were extraordinarily, uh, abundant really for me as a young person. So you know, I danced about I, I had fun, I enjoyed myself and all the rest of it and um, and met my future wife. Can you believe, such a young and delicate age that I was so there? I was a minute.

Peter: 6:50

I came out of university and I applied for jobs in industry and can you believe it? I got nowhere at all. Nobody wanted me at all, and my wife suggested I apply for a job as an unattached youth worker in the youth service. I applied for that and can you believe I was unanimously accepted. So there was a complete change of direction and I went where I was wanted and I spent three extraordinary years working as an unattached youth worker, walking around the streets of the city that I was in, getting to know young people and all the rest of it, and I made use of my enjoyment and skill, I think in the theatre. So I formed a group amongst all these kids who were not. The point of the whole enterprise was why aren’t more young people going to youth clubs? And, of course, more interesting young people didn’t go to youth clubs or the delinquent ones, and so I formed a group where I got to know this bunch of kids by just lolling around, and then we formed a youth group and it was very successful and we, we won prizes and and I was enjoying myself carrying on being in the theater and so on.

Peter: 8:11

So there I am, 21 ish, no, 24, something with my twenties and still not a clue. And then I did. Then again, I’m very much influenced by wife in those days. I mean, my wife told me, advised me to go for this job, and I never would have done otherwise. And then she went off to do a postgraduate diploma in the london school of economics and I followed suit and did a comparable course of study of diploma and applied social studies, I think it was. And there, can you believe, I encountered Winnicott. Winnicott was one of the teachers and a lovely man called oh goodness name, name’s gone now. Anyway, there were psychoanalytic, esteemed people on this course which complete will absolute news to me, finish that.

Peter: 9:08

And then we have two next, and the true story it’s not probably the formal story is that I needed to find Holly Golighty. In other words, I needed to find Audrey Hepburn, who was in Breakfast in Tiflis with all those yellow cabs and all that beautiful. And I had a thing Having been brought up on American movies, I had to go to America to find Holly Golightly. She was a total fantasy. My wife has a different story, but that’s my story.

Peter: 9:46

And so we went to New York and my brother-in-law happened to live in New York for one reason or another, so we stayed with him and then I just looked up the Yellow Pages, basically to find jobs. Looked up the Yellow Pages and looked at all of these various jobs and the usual sort of hustle and this and the other, but managed to get a job with the jewish board of guardians, which is a big, major kind of social service facility in new york, you know, and they ran a residential treatment center, yeah, upstate New York, for crazy kids, and they just had a strike and so they’d lost quite a few of their staff. And so there I was, merrily coming along and they took me on. They took me on, so it was pure pure luck, and that was an amazing job because it was working with very disturbed kids. They had about 200 of these kids on a big campus in different cottages up there in in upstate new york. And it was at that time. Psychoanalysis was kosher.

Peter: 10:58

Psychoanalysis was the way you thought this was before its demise. This, this would be what in the 1963 to 64, I think something like that. And so they were great people and I and they had training in their central office in Manhattan and I learned psychoanalysis. I was introduced to this whole new thing. Here I am, whatever I am, in the middle of my twenties, discovering psychoanalysis. I was introduced to this whole new thing. Here I am, whatever I am, in the middle of my 20s, discovering psychoanalysis really.

Peter: 11:29

And then there was a man there, a man called Fred Evans. He was a psychiatrist and he said why don’t you apply to Anna Freud for her training? And I said well, that sounds a good idea. Turns out Anna Freud’s training was in London, not in New York, and I got interviewed. And I got interviewed by two eminent child psychotherapists, augusta Alpert and Mariana Chris, in New York. I was interviewed in New York and they thought I was married at my time and our first child was there. We went back to London. My wife wanted to get back to England because of the culture. The American culture was very different. So we came back with one child and I got married when I was 21. He, he, long, long time time. I’m 21. Can you believe that? I didn’t know what on earth I was doing, but she was beautiful, so there we go I wasn’t much older, peter there we go and I’m still married to the same woman.

Peter: 12:39

can you believe that? Yeah, 64 years 64 years Congratulations.

Peter: 12:45

Yeah, married in 1960. And went on to university. So we come back to England and I then do the four-year course at the Anna Freud Center in London, which was, if you like, the kind of turning point of my life, because it was a thorough psychoanalytic training. Anna Freud was still alive and it was in a kind of heyday really, and there were about eight of us who were in that year and I’ve most of them were American. So then then, so here I am now a psycho and I’m a child and adolescent psychoanalyst, and I qualified in 1971, as you put, and then I waded off into the world. So that’s how I came to be what I am. Actually. I mean, it’s a total hit and miss story, but they’re the best stories really.

Peter: 13:42

I mean, some people the age of five say I’m going to be an accountant or I’m going to be a lawyer I had no idea what I was going to be, but that’s what I became and have became and have become ever since yes, yes over 50 years in this business.

Colby: 13:58

Wow, that’s there you go yeah that’s an extraordinary story and in fact, uh fact, peter, not uncommon amongst my guests on this podcast. So they will say something very similar about accidents, getting into it by accidents and economics as well, extraordinary. I think there’s been at least a couple of people who’ve talked about who’ve come in from a more an economics background into this space. One of my guests was a fellow by the name of Graham Kerridge and he was interested in he’d also studied economics, was interested in human capital and got a job at the Cotswold community. Yeah, and he’s an Australian. He has moved backwards and forwards. In fact he’s eventually ended up in health management and has worked all across the world in that area. But, yeah, up in health management and has worked all across the world in that area. But, but, yeah, but economics. I’m trying to think if john whitwell, who also was from the cotwell cotswold community, might have mentioned economics yeah, yeah yeah, so there you go.

Colby: 15:16

It’s all these maths. People get into psychotherapy yeah, it’s extraordinary.

Peter: 15:22

Yeah good, never have been any good at economics, but there we go.

Colby: 15:28

Yeah, and Richard Rowlandson from the Mulberry Bush. He also talked about, well, his father. He talked about maths. We had some interesting little backwards and forwards about maths on his conversation. But anyway, you’re in the group of. You are good company in both having something of a maths background and also describing how you got into the work as if by accident.

Peter: 15:58

Yeah, I would add that I was a child, adolescent, in the 50s, the 1950s, and actually people have all kinds of views about that period. But in fact in England following the war there were major changes and the establishment of an education system and health service and so on was phenomenal age and I benefited wildly from it. I mean I happened to do well at school. My own, my background is pretty modest. My father was a tailor and I was pretty modest, you know, but I did well, for some reason or other, with my A levels and then got, but only five percent of us got into university. I mean, if we I was just lucky, frankly, the politics of the time, if I were to set out now I’d probably get lost very, very early. But in those days, I mean, I did prosper very much from a very ordinary background. I mean there was nothing privileged about my life at all. I feel very grateful for all of that and I sometimes think, oh my God, you know I mean everybody’s so critical of the past, but that was a good period.

Peter: 17:14

A lovely man called a politician, called can’t remember his name Anyway, he wrote a book called the Age of Hope, the Age of Hope. Anyway, he wrote a book called the Age of Hope, the Age of Hope, and I don’t think we could say the age that we’re living in is of hope at all.

Colby: 17:34

Yeah, quite the opposite, quite the opposite. Unfortunately, you’ve mentioned a couple of names too. So Donald Winnicott is, you know, obviously still quite influential in our thinking, in child protection circles, and you met him. He was a teacher while you were doing your second part of your education. And, of course, anna Freud is a giant of the psychotherapy world.

Peter: 18:05

Winnicott and I was doing a social work training at the London School of Economics but he was just mesmerizing. I mean I was totally ignorant and this man comes on and doesn’t talk in a particularly eloquent way, but he drew a diagram of two circles and called one a bad breast and another one a good breast and he talked about these circles on the board and I really didn’t know what he was on about. But also the little bit I like to say that he and his wife Claire invited our students to his home in the Rottlosh part part of London and I played piano and I played his piano. I thought I was good. I played Willy Holtz’s piano.

Peter: 18:54

I wasn’t very good in those days but he thought he was very nice about it anyway. So you know I didn’t quite know him and I well he’s been such a presence in my life in all kinds of ways and you know he writes so well, although at times you haven’t got a clue what he’s on about, but at times I was right very well, and those phrases like the good enough mother and the transitional space and um, psychotherapy is two people playing with each other, I mean all those kind of ideas just resonate. It was a remarkable man, frankly, and we lack anybody of that significance these days, I’m afraid yeah, his ideas have definitely stood the test of time.

Colby: 19:44

I just thought of a title for your next book, peter.

Peter: 19:48

Yes.

Colby: 19:50

Winnicott’s Piano.

Peter: 19:52

Yeah, that would be nice, wouldn’t it? Yeah?

Colby: 19:59

I had these moments of inspiration, and then, yeah, and then you spent four years at Anna Freud Centre and she was still alive at that time.

Peter: 20:07

Tell us a little bit about that experience okay, well, I need to say that I was green, young and very beautiful in those days and she was where. She was not a pompous woman, she was not a Melanie Klein. Frankly, she was very different from a client, rather modest woman, but I looked upon her with in awe really and uh, uh and well, I, I, just I. It was such a thorough training in psychoanalysis. I mean, we, we were required to read Freud and it was a theory, the theory group, and it was all looking at Freud in some detail and which I still benefit from, actually the stuff I learned when you’re reading forward. We all, we all took concepts. I took the concept of resistance, I took the concepts of identification and you read Freud all through on those concepts. That was terrific.

Peter: 21:10

Anna Freud’s meta psychological profile, meaning a profile of a diagnostic profile which looks at all the various aspects of a child’s personality. That was part of the breathing. It was called the diagnostic group and we would do, I mean, looking at the complexity of a child’s growth. That was what she was on about and she’s written it in the book called Normality and Pathology in Childhood and it’s there if you want to find out about it. And then I actually became a consultant, which is a rather absurd term, but I was called the consultant of the nursery school because in the center there was a nursery school as part of the center and it was financed for socioeconomically deprived backgrounds. So there was a nursery school and Anna Freud loved the nursery school. She just loved children. She just was a very modest person really and I was somehow the consultant and I used to go down there and be part of the scene.

Peter: 22:21

Every Thursday afternoon two o’clock there was a beer meeting to discuss the children and that was very, that was very, just, very, because we all knew the children and they were. Some were very problematic and some who were very flourishing at such a young age, and Americans who had come to these meetings and the americans love to come and sit at the feet of anna freud and there’s some funny stories about that, but I won’t go into those anyway. So so, and then we had three cases. Five times a week I saw, uh, an adolescent and a latency child, the under five. I didn’t really hit it off with and I don’t think the child or the mother understood what on earth I was doing. That didn’t work out very well. I’m not very good at that, but the other two children and we would write weekly reports of what had happened and that would be reviewed and discussed and so on.

Peter: 23:26

So it was a phenomenal training. It was not the most perfect training. It was not, you know, I could. There were. There were things that didn’t not happen, but by and large it was a psychoanalytic training and it was my turning point. Really it just sort of shaped me. I was now a child and adolescent psychotherapist for the an analyst, but psychotherapy and that’s what I was, and.

Peter: 23:56

I sailed off into the world being one and have been one. Can you believe all my life? Yeah, yeah, yeah it’s very.

Colby: 24:04

It’s definitely a vocation, I think, being one myself. Yeah, if I heard you correctly, you said five times a week you were seeing the young people yeah yeah, five times yeah, that would make you over what sort of period, peter like, how long would you see them at that frequency?

Peter: 24:23

Three years two to three years.

Colby: 24:25

Yeah, and how were endings managed when you’ve had such a significant amount of involvement in a young person’s life?

Peter: 24:39

Yeah, that’s a naughty question because I don’t think endings are ever properly discussed really. I mean there is what you’re supposed to do is to acknowledge what has been done, acknowledge achievements and knowledge limits have happened, and understand the hurt and the anger of something important being terminated. I mean you ought to all do all of that. Truth is probably didn’t do it as well as I should have done really. I mean I was being, I mean all these cases of being supervised and they were very. There was an extraordinary woman called bianca gordon who wasn’t terribly popular but she was a very um particular, looked at detail, was very thorough, and so I did do reasonably well, I think, with the child, the adolescent. I was supervised by a lovely bloke called max goldblatt and I don’t think that was probably handled as strongly as it should have been really. I think I mean, given that I mean I’m not sure, really well, I don’t think. I just know, actually you can’t expect children these days to come five times a week.

Peter: 26:06

It’s just not part of the rush of our society. I think the Anna Freud was still deep in its own history really. It certainly couldn’t be applied now. The psychoanalytic trainings that exist now have three times a week, but very rarely anything more than that.

Peter: 26:26

I think the Institute of Psychoanalysis sees adults maybe four times a week, but anyway but and I think actually, I think, looking back, I think maybe maybe I could have made more of that, we could have made more of that. Maybe it was almost too much, maybe there wasn’t enough analytic scrutiny of what was going on. You get into a kind of lull, you know if it’s every time all the time. So I look back with some kind of reservations about it and I mean I know that Peter Fonagy and his I forgot her name, I forgot it anyway he and his co-worker looked in detail at the work that we had done, all the cases, all the weekly reports, and I think he could see that there were limitations.

Peter: 27:31

I think we did well with the neurotic children, but with the more borderline and the more delinquent I’m not sure we did as well as we might and I think it left Carnegie with a certain sort of questioning about that kind of training, that kind of and of course he has gone ahead now and and spearheaded uh, training which is virtually non-athletic, as I can see anyway, we won’t go into that. But um yeah, but for me it was an extraordinary experience, it really was apologies for the question.

Colby: 28:10

I. I think endings. Endings come into my work quite a lot as well and, um, you can probably tell from oh no, it’s that way from the book title just next to my shoulder. I mean, I’m very interested in bolby’s attachment theory and work very much in consideration of that.

Colby: 28:32

I don’t see children more than once a week but I have seen some children weekly, probably more ordinarily fortnightly, working in a context with young people who come from relational trauma backgrounds and relational disadvantage, and working with them for a long time and I think we become significant parts of their life growing up. And so the question of endings, and therapeutic endings is is quite a vexed one well.

Peter: 29:12

Do you know of any relationship that ends well?

Colby: 29:17

that’s a. That’s actually a very, yeah, a very important point, I think I often think that. So, for example, I observe couples. I don’t work with couples who divorce, but I’ve observed people in my circle who have divorced and observed that they considered that their life would be better away from their partner. Their life would be better away from their, their partner, who and even in circumstances where they they were, they disliked their, their spouse quite a lot. I’ve observed their life. They go through it, definitely go through a period of struggle, and things do go downhill after that because, even if you don’t like someone, there’s still been a significant part of your life, a significant connection. So, yeah, I think you’re right ending well, isn’t it really?

Peter: 30:12

yeah good ending people talk about and I wonder where it is yeah, maybe that’s a another book I don’t mind writing books either.

Colby: 30:23

Actually, I haven’t written one for a while. I I’ve been thinking of.

Peter: 30:26

How many have you written? I mean, that’s really quite something.

Colby: 30:30

I’ve only written these two, but the attachment book. I refer to that as two books because it’s two editions and when I came to update the first edition I liked it so little that I attempted to rewrite it completely and it is very different from the first edition. But my publisher asked me to put respectfully put stuff back in from the first book. So, yeah, so that’s what happened, and I haven’t written anything now for a decade. I should write something again. I’ve got lots of ideas and little time.

Peter: 31:11

yeah it’s not easy writing it’s not easy is it.

Peter: 31:15

Well, I don’t find it easy at all. The only consolation is that people think that I’m easy to read, that I’m you know and that that pleases me. But trying to get it to be like I mean I can only write stuff that I’m you know and that pleases me. But trying to get it to be like I mean I can only write stuff that I understand myself, you know. A lot of stuff I read I don’t understand. I don’t know what they’re talking about. I’m not sure they know what they’re talking about.

Colby: 31:39

I went through a Nietzsche stage reading Nietzsche’s books.

Colby: 31:43

You did I did and you know, and I took a nugget out of, oh, I took a few nuggets out of them, each of them, and and yeah, when you’re reading Nietzsche from my well, when I was reading Nietzsche, I I think, yeah, I probably understood about five percent, particularly as it went on, I think, the last of his books that he well, very close to the end he wrote, thus spake zarathustra, and I loved that book, but he was actually quite unwell when he wrote that book and uh, yeah, so it was quite, it’s quite a challenging book, but so is dostoevsky as well, and notes from the underground. You know, very short book, only about 70 or so pages, but, goodness gracious, is that hard to read. Yeah, what was that?

Peter: 32:29

what was that?

Colby: 32:31

it’s just the field or dossier’s book. Uh, notes from the underground, yeah, yeah, I similarly have a reputation for being easy to read and, um, I just say to people well, I’m just a simple man with a simple message. I don’t like over and, like you, if I don’t understand it, I won’t write it.

Peter: 32:55

No, exactly, exactly Same as me, absolutely.

Colby: 32:58

Yeah.

Peter: 32:59

I mean, I’ve read quite a lot of Freud and he’s not at all easy to read sometimes he isn’t yeah. So yeah, I tried to read.

Colby: 33:09

Interpreting Dreams a few years ago, did you really? And I gave up. Much to my chagrin, I confess, I gave up. I’ll have another go, another time.

Peter: 33:21

It’s 600 pages. That’s an awful lot.

Colby: 33:30

Peter, yeah, like I said there’s this earlier, there’s loads I could speak to you about. I you founded the, the um you founded young minds in in the uk there, um, I I knew about young minds, I think because I I had come across it at a time when there had been some reviews of probably the first edition of my attachment book that was associated in some ways with the young minds, with young minds activities. But tell us a little bit about young minds and how you came to found found it and what. What was its work?

Peter: 34:04

well, it happened in the middle of my life. I think I was in my very early 50s when I got involved with it. Well, you know, it was quite a leading light, and what can I say about it? I mean, I had been practising in the health service and very aware of, uh, poor resources and and people didn’t really understand what it was all about. And um, and there was a. There was a. It was called the interclinic conferences. Um, in england at that time, where are we now? We’re in my 40s. I can’t remember where I’d be now.

Peter: 34:51

There was a lot of concern about child guidance clinics and them being properly managed and who was managing them. Was it the psychiatrists? Who were the managers, or was it other people? But the bottom line was that there was really very inadequate resources and very limited knowledge of what they did, and so a group of us thought you know, something needs to be done, we need to make more of an effort. And at that time I belonged to a funny little group called the Child Guidance Trust and it was spearheaded by a lovely lady called Robina Addis, who was a rather posh lady, who, in the 20s, with her friends I think they were called the Mayflower ladies, and they went over to America and Adler Alfred Adler, who was one of Freud’s early departures had set up child guidance clinics over there and they learned that and they brought it back and so they started the child guidance movement in the 20s and 30s. Then the war came, but then in the 50s and the 60s they really blossomed and I think there was something like 300 or so child guidance clinics in the country and so and that was the body that was coming, that kept coming together and saying we need to have more influence than we do.

Peter: 36:13

So a long, long, long story. A couple of us did it. We started to approach the department of health and, um, and then it’s, it’s just, and then it’s just. Life is really a bunch of serendipities, it really is, for some extraordinary reason.

Peter: 36:37

I got to know the man in the Department of Health whose responsibility was to oversee expenditure or something like that, and he turned out to be an interesting man. Um, who, who, who, was in analysis himself I mean, can you believe, civil servant in analysis and he, he lived in the suburbs and he came into every time he came to London. He was looking at all these young people and an awful lot of them looked pretty hopeless and miserable and disheveled and unhappy and he said what is the department doing about these people? There are a lot of people looking after people with dyslexia, but what about these people, these emotionally? So he became well, he and I got on for some extraordinary reason, and the extraordinary, extraordinary reason was he liked horse racing, as indeed I did at that time it wasn’t the economics connection that was pretty bad economics.

Peter: 37:40

I can do that, but anyway, he he was. So we got on very well and, uh, he managed to be. It’s a long, long story, but he managed to. At that time I was running the Brandon Center, which was a walk-in center for adolescents and so on, and he managed to find some money that was not being properly spent and gave us a grant which was like magic. It was like pure magic, and so we got on with that.

Peter: 38:07

And then he was in the Department of Health and he was used to going to very impressive people. So he wanted to get in touch with a man called Louis Blom Cooper who was a barrister of high repute and sat on various child abuse inquiries. He was a rather dignified man and he got in touch. He tried to get in touch with Louis Blanc-Cooper, but Louis Blanc-Cooper was in the bath. But his wife answered the phone and I happen to know his wife rather well and she said you don’t want to talk to Louis, you want to talk to Peter Wilson.

Peter: 38:50

And that’s how this chap and I got on with each other and that was that pure piece of utter serendipity. It’s just ridiculous. And then on the back he said well, it’s all very well, you’re running this center in the middle of London, but what about all these young people? What are we going to do with that? So with his support his support he managed to get some money together to actually fund the beginning of Young Minds Enough money to pay for my salary, an information officer and a PA for me £150000 pounds or something. And because of that that’s how Young Minds happened and I became the director and it was a really important course. Two things raise awareness of children’s mental health and improve multidisciplinary services for them throughout the lab. They were the two main things, because at that time if you talked about children’s mental health, people thought what are you saying? They’re all crazy, they’re all schizophrenic. What the hell are you talking about? So we had to define what we meant by mental health and then so I built the organization up and I was there for I don’t know, 10 or 11 years or something like that in my 50s and we built it up and we had a budget of about 2 million, I think by the end of

Peter: 40:20

it and we we organized a consultancy service that went across different parts of the country and looked at the way different departments are organizing comprehensive services. Children’s mental health was not just the business of psychiatry or psychotherapists. It was the business of everybody in the voluntary sector and there were some very good reports. It was a good period. This was in the 90s, in the early part of this century, so that’s how that happened and it was going very well indeed. But then there was this whatever it was a bank crisis or something. Suddenly everything was in crisis because of all these dodgy loans in America or whatever. It was a bank crisis or something. Suddenly everything was in crisis because of all these dodgy loans in america, or whatever it was. Yeah, and everything tightened up. Everything tightened up and, as a result of that, things have not gone very well since. I can talk about that later on.

Peter: 41:21

But that’s what young minds was and it was very alive and I had about 30 staff and it was. It was terrific, actually it was very, but it took a hell of a lot out of me, I must say. You know, I worked long hours. I worried about money all the time. Get to christmas and the financial year is march and you can see an almost deficit where you’re going to get the money from. I mean, it was, and I went all over the country talking and this and the other.

Peter: 41:48

I did work terribly hard, um, and it was, it was good and actually, and we ran a parent information service and people, parents, ringing up about their kids, and that was very well in. It was. It was going very well. I was very with it. But then I got to 65, 65 or coming up to it, and I really I thought I’d done enough and I was pretty exhausted, pretty exhausted, and I was ready to retire, you know, carpet slippers in front of the fire, dozing off forever and ever. But then an extraordinary woman called Benita Refsson, who ran an organization called the Place to Be that puts counselling into schools nationally, came and said would I be a clinical advisor to her organization? And I couldn’t resist it really, and so I did that for several years afterwards. But everything is all by chance really. It really is one chance. Yeah, I feel very proud of it. I’m rather sad that I think all of his efforts have pretty well come to nothing as a result of recent political events in this country.

Colby: 43:04

But we’ll come to that later on, if so be yeah, and you were a consultant, I think, at pepper harrow too, or you were you’re involved in paper harrow.

Peter: 43:15

Yes, there was one frenetic period in my life and I’m not entirely sure I’m proud of it. I was working in six different places during the course of every week omnipotence madness, but that’s. I was working in six different places during the course of every week, omnipotence madness. That’s what I was doing. And Pepper Harrow was another extraordinary thing. It’s a therapeutic community in a big house in the country with, about when I first it was 50 kids first of all, now it’s 30 kids and a staff of about 30 or something of that kind, and that was an amazing experience. I mean, really, really disturbed crazy kids, very delinquent, some borderline and uh, and it was a therapeutic community. So you know, every morning there would be a community meeting, everybody, all the staff, all the kids, come together in informed community and and so the staff operated both as teachers and as as therapists.

Peter: 44:35

It was a whole kind of integrated idea yeah and it was amazing place and the man who ran it had a certain kind of extraordinary charisma as a little guy but very, very determined and and he led it with a kind of passion very strong.

Peter: 44:53

And the dining room was was designed so that all the tables were breast like in shape and the children had a delicious, every lovely field that they wanted. I mean it was an amazing place. It closed because and I was the consultant my basic job was being a consultant to the staff to help deal with the pressure at all, but of course I was in the community and I was known and so on.

Peter: 45:22

So that was incredible and I was known and so on. So that was uh incredible that was Pepa Haro. Yeah, that was Pepa Haro. It was amazing and I’m not sure I was. I mean we’re trying to. I mean I loved them.

Peter: 45:34

I always remember he was determined to try and understand the, the psychopathology of these kids and what was in them and he had, and I think he hoped that I really would be able to get there and tell him, and I don’t think I did. I think I was reasonably useful to staff, but to understand the extremity of their misery and their acting out was was just wild. But it was a wonderful place and it couldn’t exist. It couldn’t exist now because you know, for example, for example, if a kid ran away, staff would run after them and bring them back. Can you imagine? And physically bring them back, physically touching them, safeguarding, and what do you mean? Kids have a right to their right to go off.

Peter: 46:21

We had a scandal in this country where men have been exploiting young girls who’ve been run away from their children’s homes, sexually exploiting them. These kids have been allowed to run out and nobody’s come and found them. They do that because you know to find them, them to bring them back physically, is safeguarding, and so it was a great place and it had passion and commitment and care.

Peter: 46:56

it wasn’t just a child minding place, it was a therapeutic place and some of the kids did remarkably well and some of the kids did remarkably hopeless. I mean, it got nowhere, yeah. So there we go. So I’ve been incredibly lucky, frankly, in having that experience, and that’s simply because I happen to know the founder of the place, a play called Melvin Mose, and for some reason he thought I was very good, so I took the job and it was well paid, so I did it.

Colby: 47:25

So I took the job and it was well paid, so I did it. Peter, I want to pick up on something that you said there as a bit of a segue into your soon-to-be-released book, because you were saying how the chap that was running the place really hoped you could answer the questions that he had about what was going on for the young people, and you’ve got this book coming out with a rather intriguing title to it the Adolescent and the Psychotherapist. Why, I Don’t Know Matters, and I wondered if there was just anything that you could, you felt able to share with us about the book and maybe even a little bit about that title yeah, well, it’s going to be published, apparently in December or over the next year.

Peter: 48:17

It’s going to be published being through all the business contract, more than I say. And well, I wanted to call it, I wanted to call it, I don’t know. That’s what, that’s all I wanted to be, I don’t know. But their editors routledge, um, they said I’m not already happy about that, would they put the book what? What section of the bookshop or the library? And I can see their point of view. Um, but I had a thing about, I don’t know anyway, one.

Peter: 48:48

I went, we went barmy, trying to think of a title. The adolescent, the psychotherapist is not a bad title, but in the end I kept it in. Why, I don’t know matters. And the book basically is a collection of papers that I’ve written in the past. I’ve written about 40 or 50 papers or chapters that have been here and there and I’ve got 10 in there and I think that they’re quite pleased with what they’re giving off, I think, and I think it meets the title of the therapist and the adolescent.

Peter: 49:26

But I don’t know how I had a thing about, and there’s two main reasons. The first is clinical. You tell me anybody who sat down done psychotherapy with adolescents and they are confronted with I don’t know, I don’t know. What do you feel, what do you feel? What do you feel? I don’t know, I don’t know. And I think as therapists we’ve become rather cross. I’m here to know and you’re saying you don’t know. That’s resistance, resistance, whereas in fact it’s much more than that. It’s much more uncertainty about what they feel.

Peter: 50:00

Anyway, they’re not sure whether they should say or not say are they being disloyal to their parents? To talk about this? I mean, there are all kinds of reasons. Be it, I don’t know. And so I think it matters that we respect I don’t know. Also, the other thing is political. There’s far too much certainty that having an influence on policy and it’s my crack and the scientists.

Peter: 50:29

Now, I’m not anti-science or all the rest, wonderful things, but the science of psychotherapy not so good, not so good, not so conclusive as they make it out to be, so that they think cbt is the treatment of choice. This is what evidence suggests. The evidence is not good. It’s not good, it’s a lie. They’re lying about it, in my view, and so they are not saying I don’t know If they said I don’t know, but so far this looks as if CBT can be helpful with certain patients, for a certain type of plan maybe, but they don’t it’s either. They know, and they’ve set up a whole kind of service delivery now which is based on we know, and we will do it this way.

Peter: 51:22

So do it this way, so I, I don’t know matters, and I. A great virtue If I, if you and I. I mean the paradox is I’m telling you what I think I know, but you know if, if we leave it and I say I know everything, then you haven’t got a question to answer because I’ve known it all by saying I don’t know. That opens up our dialogue for for something, and so I think there’s a, there is a, there is a virtue, virtue not knowing. And through not knowing we discover. If you say no, you’re not opening your mind. That’s right. So that’s what that book’s all about.

Colby: 52:12

I was hoping that you would say something along those lines. I remember John Whitwell talking about using I don’t know as a way of opening up reflective thinking about things, and I was also thinking with teenagers that I don’t know. Is there a way sometimes of setting some boundaries around themselves? And if that is possibly what they’re doing, then that’s something we should respect rather than get frustrated with yeah, yeah, no, that’s wonderful.

Peter: 52:58

Talking about Australia, I did a series of seminars organised by Peter Blake, who you presumably know no, I don’t, you don’t, no, really. Organised by Peter Blake, who you presumably know no, I don’t, you don’t, no, really. He’s in Sydney and he’s written an enormous book on child psychotherapy, peter Blake. Anyway, at these seminars, people will present me with these impossible cases and I will say I don’t know and I’m worried that actually that wasn’t the right approach. People want you to have omnipotent answers and I just don’t see it.

Peter: 53:34

I think we have to live with the uncertainty in order to find out a bit more.

Colby: 53:42

So there we are is there any advice that you would give your younger self as a, as a early career psychotherapist, um, from from the position that you’re, you’re in now, or that you would give, indeed, to other, uh, early career um psychotherapists? Child and adolescent psychotherapists?

Peter: 54:05

very. It’s a very, very good question and therefore a very difficult question. Yes, I have been thinking about that. I’m going to give an answer, thinking about myself and maybe particularly psychotherapies. The advice I would give young Peter Wilson is to do something to enable him to be more assertive and confident in what he, uh was doing, and you could say my analysis should have done that, but it didn’t. I mean to speak with more authority, to to be more, um, to be less inclined to let things pass, to basically recognize the wrongness of what other people are talking about and to express my disagreement.

Peter: 55:10

I think, I’m not putting this very well, but I wish I’d had more authority to some deeper sense of authority within myself that I think I have now, which I’ve gleaned from my my life’s experience. But as a young person I don’t think, and I think it’s something about psychoanalytic training, um, that it makes you reflective and thoughtful and all the rest of it, but doesn’t really engineer you to to speak up. I had a farcical experience a long, long time ago, uh, with a man called wallace hamilton and we were involved in um trying to establish a salary structure in the national health service for child psychotherapists, which in fact, we did an amazing piece of work. But as part of that, we were involved with a trade union I forget what it was called now the trade union and they organized some training sessions in how to negotiate.

Peter: 56:24

And we had an ex coal miner I think it was a unionist coma and he was a rough truss sort of bloke and we were videoed in in negotiating relationships. We were pathetic we were. We were leaning back, saying, oh, yes, yes, yes, yes, and just leaning further back, almost a disappearance, whereas we should have been much more assertive, confrontational, authoritative and so on, and I really I would. And I say I mean I don’t have too much to do now with young child psychotherapy, but I encounter them every day and they’re very nice young men but they’ve got no balls, if I can put it that way. They need a bit of punch and they’re also understanding.

Peter: 57:15

It’s that balance between understanding and assertion. And so and I think we do ourselves it’s that balance between understanding and assertion and I think we do ourselves a great disservice as a child psychotherapy profession. The psychiatrists have sort of bred with it. They are the people who know about mental health, they know about mental illness and the psychologists are very, very pushy and very uptight and so on, but the psychotherapists, I think, are a pushover. Frankly, I wish I’d had greater authority as a young man, even at Young Minds, when I was pushing for child mental health. I found my psychoanalytic background. Psychoanalytic understanding was too understanding. People don’t believe in psychoanalysis background.

Peter: 57:59

Psychoanalytic understanding was to understanding people don’t believe in psychoanalysis by and large they don’t. They believe in what’s obvious, what’s said on top. We all looking underneath what’s what’s what’s really going on, but they don’t get there. You need to operate at that kind of level, yeah it is, I is hard it’s the worst of my life. I think I wished I would like that would be something. I mean it’s a good answer, I think, to a good question really, because it’s an honest one, and I do feel I rue that I didn’t have more of that in my life.

Colby: 58:34

But there’s also a wisdom in humility in a sense. I know that sounds a wisdom in humility. I know humility. I know that sounds a bit corny, but it’s as we were talking about in relation to, I don’t know, maintaining a stance of curiosity, yeah. Yeah, not jumping in with the answer straight away. Yeah, maintaining an open space of inquiry, which I think is very much. I don’t describe myself as a psychoanalyst in the same way that you do, but I think that’s really a cornerstone of psychoanalytic work is that it creates space for inquiry and exploration.

Peter: 59:31

Some people just assume that they are to be heard and I don’t think I’ve had that assumption. I mean not that I’ve been effective. I mean you’ve highlighted a conundrum. Frankly, you know that I do believe in not knowing and humility and so on. At the same time, I wish I had been something other than what I’ve been. Not that I’ve been lacking in any assertion, but I could have made more of a difference. I could have made more of a noise.

Peter: 1:00:03

People make an awful lot of noise and people sort of keel over under the weight of the noise.

Colby: 1:00:10

There’s a proverb, isn’t it the rusty? What is it? The rusty gate gets the oil, or something like that. Though, what would you say, peter, if you were sitting in front of the health secretary, and what would you say to them now about child and adolescent mental health and what needs to happen?

Peter: 1:00:34

Well, it’s a bit in my head at the moment because there’s a very good article in the latest edition of the Journal of child psychotherapy and this chap’s written what the state of affairs is in the for a child psychotherapist and basically what he’s actually saying is that two major developments have occurred in the running of mental health services in this country. The one was a the introduction of something called IAPT introduce introduce improving access to psychological therapies.

Colby: 1:01:12

Yeah.

Peter: 1:01:13

And the other one was the children health and social care act of 2012. And he highlights these two things and the two strains which are so important. In the first, in IAPT, it’s all about improving access and apparently improving treatment. Uh, improving access and apparently improving treatment, but it bases the, the, the therapy, on what is called nice, the national institute of clinical excellence. Look at very thoroughly at the end and the evidence from that suggests probably more powerfully, points to cognitive behavioral therapy and that that is the therapy that should be offered for all in all in all, child and adolescent mental health services should be CBT, which is the predominant offer, and that is reinforced by this power of evidence that it works. They’re interested in outcomes. And there’s a whole history about IAPT. It was basically introduced by the Minister of Economics, funnily enough.

Colby: 1:02:35

Again.

Peter: 1:02:39

Again, he was very concerned that so many men were not going to work because they were depressed. So let’s bring in a treatment which apparently works with depression. Get these poor buggers to work. That was the raison d’etre. And it happened to be he had a close relationship with a cbt specialist in the mausoleum hospital and so cbt was presented and now it put it pervades everything.

Peter: 1:03:07

So as a child psychotherapist working in a health service, by and large in the camps, you won’t be if you won’t see a referral out there. As it comes in cbt, be offered it Maybe three or four attempts before it’s given to a child psychotherapist, and that’s absolutely wrong. And the thing about all this evidence is that it doesn’t really take into account the complexity of people’s problems and it’s just it purports to deal with mild to moderate problems. Anybody can do that. Really, you know, to deal with the kind of real problems that we have in in our society you need much more. So IAPT has entered into the realm. The the other thing is this Health and Social Care Act, which actually is coming from a political view that people, we should be in businesses, we should be in competition with each other, we should be efficient, do outcomes and we should compete with each other.

Peter: 1:04:20

We should, and I’m putting that broad as a broad political view, um, but now being applied to that simply means everything is division, everything’s divided. Yeah, people are fragmented. I have a kid. I’m working with a kid and somebody says, well, this kid’s got a neurodevelopmental problem or something. So therefore the kids should go to that service, not be part of the service I’m doing and anyway.

Peter: 1:04:52

So it’s a long, long story and I’m full of it at the moment because it really pretty well renders irrelevant to all the work I do at Young Marts. I mean, they, they they’re very impressed that everybody has more awareness of child mental health, possibly, but I’m not sure that people understand what mental health is. And, um, as far as my whole attempt to bring together the disciplines to provide a comprehensive service, that every discipline is in competition with each other, yeah, being more competitive, and it just is. And we hear people demoralized and their skills devalued. And so what would I say to the health secretary? Abolish the lot. Yes, a weakness is, cbt is attractive because it’s quick, short term and ding, ding, ding, whereas our psychotherapy is longer, it has to take longer, it has to. And the overwhelming thing is the resources for CAMHS for children’s mental health has been reduced. I mean, posts are not being re-advertised. It’s just an appalling situation.

Peter: 1:06:16

Now I feel for the Secretary, the Health Secretary, a man called Wes, something or other, montgomery. I feel for him because the National Health Service is really in a terribly difficult state and I don’t think child mental health is going to be high up on its priorities. And what would I propose instead? Because it is a factor that there’s an enormous need, an enormous demand, and what can people do effectively to deal with it? I understand all that, but the bottom line is people are getting disillusioned. All the CBT doesn’t work for most of these people and everybody becomes disillusioned and I think it does a major disservice in the long run. But what I would advise I’m moaning more than what I would advise but I would advise not to be so reliant on these two policies, to think about other ways of meeting a need. It’s a very, really serious problem really, and families anyway.

Colby: 1:07:23

So I was just going to say you know as much. If it’s worth anything, what 30 years of delivering psychotherapy to children and young people has taught me is that they don’t like CBT.

Peter: 1:07:37

No, they don’t.

Colby: 1:07:39

They much prefer relational, play-oriented psychotherapy.

Peter: 1:07:46

Yeah, absolutely, they much prefer it, yeah.

Colby: 1:07:49

And I remember when I was training. I remember there was and that’s over 30 years ago now, but I remember a relatively recently retired clinical psychologist here in my home state. I remember her addressing our class and saying that all the CBT practitioners in our professions you know there’s all these people that advocate for CBT and say that CBT is the answer, but when they themselves need a therapeutic service, they find someone who is much more person-centred. Analytical Absolutely yeah, I’ve never forgotten that. Analytical, yeah, absolutely yeah, I’ve never forgotten that. Anyway, yeah absolutely.

Colby: 1:08:45

Peter, yeah, we’ve had a wonderful chat and there’s so much more. I’ve really enjoyed it and there’s so much more I can speak to you about. I wondered if there was any question that you’d like to ask me before we wrap up. I’ve asked you a lot of questions.

Peter: 1:09:01

Yeah, you got me there. On the last one. What would you like me to ask? I think maybe. What do I mean by psychoanalysis, Because I always go on about it and I, yeah, yeah, I think that’s what am I talking about. I think I’m a psychoanalyst you’re asking me well, it’s a question you should ask me, but you can ask yourself.

Peter: 1:09:35

It’s a question you could ask me and I would have liked that would have been a difficult question for me, because there’s two question what you could ask me and I would have liked that would have been a difficult question for me, because there’s a. There are two ways of thinking about that. The Institute of psychoanalysis is basically the, the interpretation of the transference of the unconscious, and it’s on the couch, and you hold your position. For me, I psychoanalysis is much more on a live business, looking at the sheer conflict and struggle and yearning and desires and frustrations and what it does to you and how it affects your mood, and it’s everywhere. It’s everywhere, it’s not just on a couch, and that’s what I mean by psychoanalysis yeah, it’s almost like a science in and of itself.

Colby: 1:10:22

It’s the science of the human condition, the scientific inquiry or you don’t even have to use the word scientific, but it’s the inquiry into the human condition really, and it’s not boundaried in the ways that other approaches or conceptualisations are, it’s not limited. It’s because, you know, probably going right back to free association, it’s about an unboundaried exploration of each human life that you come into contact with.

Peter: 1:11:01

Absolutely absolutely.

Colby: 1:11:03

Peter.

Peter: 1:11:05

Was your question. Do I have a question of you?

Colby: 1:11:10

Yeah, well, I often I say to all the I don’t ask a lot of questions in the way I do therapy with children and young people, but if I do find myself asking them a lot, I’ll say to them well, I’ve asked you a lot of questions in the way I do therapy with children and young people. But if I, if I do find myself asking them a lot, I’ll say to them well, I’ve asked you a lot of questions. Is there a question you’d like to ask me?

Colby: 1:11:27

hey, that’s right yeah, and, and usually I can almost predict. I don’t want to say this with any certainty, but I can almost predict what they’ll ask. The first things they ask is how old I am, and they’re not satisfied with as old as my tongue and a little bit older than my teeth, which is what my grandmother used to always say. For a long time I got away with telling them how old I was in months, and then a couple of kids started to work that out, so now I just do it in doggies. I am in doggies good question.

Peter: 1:12:06

My question would be what are you, what are you learning from these interesting podcasts? What are you going to distill from it? Maybe it’s too soon, but that would be. It’s such an interesting project you’ve got going here Aye, aye. What are you going to learn from it? You don’t have to answer my question.

Colby: 1:12:26

I will say one thing. I’ll say a couple of things. One of those things is that I am learning a lot about a whole range of aspects of practice in um, the in. I call the podcast really a podcast about child protection out of home care and related endeavors. So I’m I’m learning things about you know, for, like you know how to run a good child protection organisation, I’m picking up ideas because I’m speaking to people who’ve run them.

Colby: 1:13:08

But the thing that I would really, that is really coming through for me is is the person reflecting on the person in the role? Because I think for a lot of my career I’ve been really trying to understand the person in front of me and what. And I think and I think part of this is because psychoanalysis is less popular in Australia than it is in the UK and Europe. It still has standing there and I’ve interviewed a lot of people from the UK and some from Europe but what I’m getting out of it that I probably knew but didn’t consider enough, was the person in the role, if I can put it that way.

Peter: 1:14:13

Very good. Yeah, I like that yeah.

Colby: 1:14:18

Well, we’ll finish on that point. As I said, Peter, thank you very much for agreeing to come on and also for being a good sport about my faux pas of not giving you more prior notice about what questions I might ask. But yeah, thank you again and good luck with the book, and I really hope that there might be an opportunity for us to speak again.

Peter: 1:14:45

I hope so. It’s been very good meeting you. Thank you for this podcast.

Colby: 1:14:51

Thank you you.

Relentless Kindness: The Foundation of Therapeutic Care, with Adela Holmes

Trauma-Informed Care: The Power of Relentless Kindness in Therapeutic Residential Settings

In the challenging landscape of therapeutic residential care for traumatised children, a profound approach has been quietly transforming lives for nearly two decades at Hurstbridge Farm in Victoria, Australia. This revolutionary model, developed by Adela Holmes, has consistently demonstrated that relationship-based care grounded in neurobiology can heal even the most severely traumatised children.

What makes this approach stand out from other care models is what Holmes describes as “relentless kindness.” This isn’t just being nice—it’s a deliberate, consistent therapeutic stance that prioritises relationship over traditional behavioural management techniques. The model recognises that traumatised children operate from lower brain functions and cannot access higher cognitive abilities until they feel safe and valued.

Traditional approaches to managing challenging behaviour in out-of-home care settings often rely heavily on cognitive behavioural models—star charts, points systems, and rewards for good behaviour. However, Adela’s experience at Hurstbridge Farm demonstrates why these approaches frequently fail with severely traumatised children. These children typically haven’t developed the capacity to regulate their emotions or delay gratification. They don’t expect adults to follow through on promises, leading them to either demand immediate rewards or sabotage the process entirely.

Adela shares a powerful story about a young boy who requested a star chart upon arrival at Hurstbridge Farm. Rather than implementing the chart, she simply gave him the CD he wanted, explaining: “I want you to have the enjoyment of listening to that person singing on the CD and I want you to feel good about having it.” This approach demonstrated worthiness and deservedness—core experiences these children often lack.

The Hurstbridge model was built on solid foundations, drawing from decades of successful therapeutic residential care approaches. Adela studied established models like the Mulberry Bush School in the UK, Villa Santa Maria in New Mexico, and Chaddock near Chicago. All shared a common thread: relationships as the primary vehicle for healing.

One striking feature of the Hurstbridge approach was the constant presence of caring adults. Children were never left alone except for personal privacy. This consistent presence created a containing environment that allowed for co-regulation—adults helping children manage their emotions until they could develop this capacity themselves. One young boy who initially resisted this approach was later found frantically seeking an adult when he woke up alone, demonstrating how quickly children can adapt to and need this consistent care.

The neurobiology of trauma informs every aspect of this approach. As Bruce Perry, a leading authority on childhood trauma, explains: “Traumatized children tend to have overactive stress responses… Before they can make any lasting change at all in their behaviour, they need to feel safe and loved.” The Hurstbridge model follows Perry’s principle of “going to the lowest part of the brain implicated” to create change, providing countless repetitions of corrective experiences.

Despite its success, implementing this model isn’t easy. Adela describes the doubt she often felt and the criticism she received from colleagues who believed the approach lacked sufficient boundaries. However, the long-term outcomes speak for themselves—many of the children who experienced the Hurstbridge model have gone on to lead stable, fulfilling lives, with many maintaining connections with staff members years later.

In a field often dominated by quick-fix solutions and compliance-based approaches, the Hurstbridge Farm model stands as a testament to the power of relationships, neuroscience, and what Adela beautifully describes as “relentless kindness.” For anyone working with traumatised children, the message is clear: start with relationship, understand the brain, and never underestimate the healing power of consistent, compassionate care.

You can listen to the podcast here:

You can watch here:

About Adela

Adela has a career spanning 52-years, during which she has worked in the child protection, child & family welfare & out of home care fields for both the Victorian state government and the non-government sector. Adela has a well-established track record in designing, developing and delivering complex trauma grounded therapeutic care services for the most complex and challenging children and adolescents, and an expertise for working successfully with and supporting others to work with these children and adolescents.

During her career Adela has designed and been involved in the ‘start up’ leadership and management of significant therapeutic service initiatives funded by the Victorian state government. These include the ‘Take Two” Intensive Therapeutic Service and the Victorian government’s successful pilot therapeutic residential care program, Hurstbridge Farm. 12 other pilot programs were developed using the same model and, in 2011, all 13 were evaluated as being highly effective in producing positive life outcomes.

Adela has been specialising as a trainer in the utilisation of complex trauma frameworks since 2000 and during this time has consolidated an extensive knowledge base and expertise in trauma & attachment informed therapeutic practice, both as a practitioner and a trainer of these skills. Adela also specialises in the facilitation of Reflective Practice Groups and, in her consultancy work, Adela delivers to such groups as a visiting consultant on a regular basis.

In October 2024 Adela was awarded the inaugural Centre for Excellence in Child & Family Welfare Industry Lifetime Achievement Award for Services to Out of Home Care.

Related Podcast Interviews:

Jenna Bollinger

Listen here:

Watch here:

Richard Cross

Listen here:

Watch here:

Transcript:

Colby: 0:00

Welcome to the Secure Start podcast.

Adela: 0:04

But don’t give up and don’t change, because it’s kind of in the hardness that gets success and that requires really strong leadership and what I call relentless kindness towards children. He talks quite clearly about the importance of children learning how to like themselves. One of the experiences that I’ve found quite important in moving into developing a model was the experience that I’d had of observing a model that very clearly did not work. If you’re going to develop a model of care for any group of children, it’s actually got to fit the children for whom you’re providing it. We relentlessly were nice and good and we didn’t try to achieve things with him that he couldn’t possibly achieve being able to use relationships to build safety and trust. Here’s something else that I wonder if you know, but that if you do run off, we run away with you.

Colby: 1:31

Welcome to the Secure Start podcast. I’m Colby Pearce, and returning for this episode is a highly respected figure in residential childcare here in Australia. Child care here in Australia, adela Holmes. Before we begin our conversation, I’d just like to acknowledge the traditional custodians of the lands that we come to you from. For Adela, it is the Wurundjeri people of the Kulin nation and for me, it is the Kaurna people of the Adelaide Plains and I’d like to acknowledge the continuing connection the living Kaurna and Wurundjeri people feel to land, waters, culture and community and pay our respects to their elders past, present and emerging Now. I saw Adela out for a return to the podcast after reading a social media post of hers about trauma-informed, relationship-oriented and neurobiology-informed practices and was keen to talk to her further about this. Welcome, adela.

Adela: 2:39

Thank you. Lovely to be here, Colby.

Colby: 2:42

So, as we just were talking about, and I mentioned in the little intro, what captured my attention was a post on LinkedIn in which you presented some reflections really about trauma-informed practice and relationship-oriented practice in the out-of-home care space and where neurobiology, and I guess in particular, the neurobiology of trauma, sits, with current trends. So that’s what I love to pick your brains about and and I’m sure that people who listen to this podcast will also be very interested to hear your thoughts.

Adela: 3:28

So, in terms of sort of preparing my mind for talking about that today, if I can just reflect what drove me to write that post, on LinkedIn, I’d seen a few posts that worried me in terms of perhaps a growing tendency to shrink from some of the practices that we have been quite successfully using in working with the young people in residential out-of-home care. Because it is fair to acknowledge and I think I’m going to acknowledge that quite a bit during what I’ve got to say today but doing this work in that way, in what I would call the correct way for the client group, is hard work and I would not be surprised by people feeling tired or somewhat daunted by it.

Adela: 4:35

But the role, I think, of people like myself and yourself and others who lead the way in therapeutic residential childcare is to actually keep the motivation up and to encourage and support those who feel like faltering by the wayside by actually acknowledging yes, it is hard, it is really hard, actually acknowledging, yes, it is hard, it is really hard, but don’t give up and don’t change, because it’s kind of in the hardness that gets success and that requires really strong leadership and what I call relentless kindness towards the children and the word relentless tends to have often a negative edge to it, but I’m not talking about any negative edges. I’m talking about an absolutely relentless knowledge of how important it is that we maintain our internal state and our external state as a consequence. So one of the things I thought I’d talk about today is the lead-up and the preparation that I did when I was writing the proposal which later, you know, then morphed into the model for Hurstbridge Farm Therapeutic Residential Care Pilot, which was requested by the Victorian government.

Colby: 6:18

Yep.

Adela: 6:19

And I was already working at Take Two, the intensive therapeutic service that had been secured by Berry Street. I was working with Berry Street in Take Two when they wanted to move to the second recommendation of a report that they had commissioned in the late 90s, which was to initiate a therapeutic residential care pilot where an approach could be trialled to see how successful it would be. And of course that came to me in the role I was in at Take Two to write at the time, and so I thought I’d talk a little bit about that and where my relentlessness came from, and then sort of see where that takes us, if that’s okay with you, Colby.

Colby: 7:18

That sounds awesome. Interestingly, when you talk about that relentlessness, a number of my guests have talked about the importance of stickability. Yeah, I don’t know if they as such and perhaps in the foster care context more so. But stickability, yes, and the other thing that just a question I have, and the other thing, that just a question I have, and perhaps you’ll cover it, but if not, I’d be interested to hear what you think are some of the reasons why it is so hard the work.

Adela: 7:56

Yeah, look, it’ll probably become apparent as I’m talking, but if you don’t think I’ve articulated it clearly enough, ask away. Yeah, sure, but when I was first approached at Tag2 to write this proposal for the pilot, I was very mindful of prior experiences, because I guess my natural inclination had always been somewhat similar in terms of the use of relationship, because that’s something that I learnt when, I think, I talked about starting out in the institutions when I did my last podcast. That was something that I learnt in those settings that, even if you were very limited in what you could achieve because of the environment, you could still demonstrate to those young women what it meant to be there for them, present in the true sense of the word, and to demonstrate that you liked them.

Adela: 9:21

And I had not read Bruce Perry yet, right but, I’m going to read a short paragraph from Bruce Perry during this, because he talks quite clearly about the importance of children learning how to like themselves, and that was something that I did develop when I was working, you know, right at the beginning of my career in the institutions.

Adela: 9:48

But what I also understood was that it wasn’t enough. Right, it was important and it was great, but it wasn’t enough to actually achieve the change that was required, and I don’t know that I understood that completely fully until I’d done all the reading that I’ll talk about in a sec. In terms of putting together the model for Take Two Sorry for Hurstbridge when I was at Take Two, for Take Two sorry for Hurstbridge when I was at Take Two, one of the experiences that I found quite important in moving into developing a model was the experience that I’d had of observing a model that very clearly did not work for young people. Observing a model that very clearly did not work for young people. This was something that the department I think had tried to initiate in I’m just trying to think of the year. It was around 2003, 2004, I think and they wanted to develop a house that they had in the community to work with four young people.

Adela: 11:13

Now I’m not going to use any names but, the person who developed that model selected a very cognitive approach which involved points and things you could gain and lose, and you know it was quite complicated and it didn’t work. And it very clearly didn’t work because there was quite a level of interest in understanding why it didn’t work and that fell to me to explore in my role at take two, in the role that I was in at the time, because that was what I was focusing on, and one of the things that became very, very clear in terms of why that model hadn’t worked was because it was exceptionally cognitive and so for me that was quite important to hold in my mind. And then the more reading that I did, and certainly the more reading of Bruce Perry that I did, I completely understood why that model had not actually worked. And I suppose my starting point then that I developed was if you’re going to develop a model of care for any group of children, it’s actually got to fit the children for whom you’re providing it. Yes, it’s got to fit with their needs.

Adela: 12:50

And of course, the problem with that one was it didn’t fit with their needs, because we were talking about the child protection client group of children who really don’t like themselves and their starting point is lower down in their brains, if you like, and reading the work of Bruce Perry and others really helped to cement that in my mind, so I knew where I had to start. Looking was not in the range of cognitive models that exist out there. Now I’m not saying that cognitive models don’t work at all. I’m just saying that they’re not a good fit for the client group that I was mainly looking at writing a model and developing a model for.

Colby: 13:42

Yes, and if I can just jump in for a moment and just for our listeners as well, when you’re talking about a cognitive model in my parlance, I’m wondering whether you’re talking about a cognitive behavioural model, because you referred to points, and so I’m imagining that the model would require the young people to reflect on themselves and their approach to life in the home particularly, and regulate themselves in consideration of a set of expectations that could achieve them points towards a positive outcome.

Adela: 14:30

And for rewards right. Yes so there’s an implicit belief within that that A they can regulate themselves which you know we’ll talk about a bit more but that they can regulate themselves and that they can do that in a thinking reflective way to achieve a certain outcome, neither of which is actually possible for very traumatised, possible for very traumatised young people who are really not operating from that part of their brains effectively.

Colby: 15:13

No, and nor do they expect adults to follow through on promises. You know, on agreement, I often say where such an approach is tried, the young person I’ve found observed, the young person will go. Well, if you were going to give me that, you can give it to me now.

Adela: 15:34

Yeah.

Colby: 15:34

And if you don’t give it to me now, you are never going to give it to me Exactly, or they’ll sabotage. Yes, yes, because they don’t like uncertainty, so they hate uncertainty, in fact, and so they’ll go. Well, I’m never going to achieve it. You are never going to give it to me, so I might as well just blow it up.

Adela: 15:56

Well, it’s interesting. You make me think about a child who first, once we had the Hurstbridge Farm going. In the very first weeks of coming to the farm, this young man, who was about 13 and a half, said to me in his, I think, first or second week. He said to me can I have a points chart, a star chart? And I said oh, have you had one of those before? He said yes. I said why is it that you want one? He said because I want a CD of CD, and he mentioned some artist. I want a CD at the end of the week and that’s how I’ll get it.

Adela: 16:52

And I said have you always been able to get, you know, the thing you want at the end of the week with a star chart? And he said oh, oh, not always. And I said how many times do you think you might have been successful? He couldn’t really remember. Anyway, I said to him look, we don’t actually do star charts here. But I said let me say right now you can have your CD at the end of the week, no star chart. And let me tell you why I don’t want you to have a star chart. I don’t want you to have a star chart, because I want you to have the CD, because I want you to have the enjoyment of listening to that person singing on the CD and I want you to feel good about having it and listening to it. I said I don’t like setting people up to fail and I don’t know whether you can do it or not, but I really don’t want to start you being here with that experience.

Adela: 18:10

So you can have the CD and we’ll organise for you to go and buy it. You don’t have to wait till the end of the week. You can have it now. Now, what was I demonstrating to him?

Colby: 18:24

His worthiness, his deservedness, All of those things and that he would. He was with people for whom his interests were important.

Adela: 18:37

Yeah, and that I wanted him to feel good and I wanted him to have something that was enjoyable to him, which I would say is probably a thirst, and I wanted him to have something that was enjoyable to him, which I would say is probably a thirst. But that’s no, I’m not saying that he miraculously changed overnight, because of course he didn’t.

Colby: 18:56

That would have been quite inconsistent with his model of relationships and he’s likely to have, yeah, tried to sabotage that approach.

Adela: 19:02

Absolutely, and he did many times. But we relentlessly were nice and good and we didn’t try to achieve things with him that he couldn’t possibly achieve. And, interestingly, he is quite a challenging young person to work with all through the about two and a half years that he was in the program. But, strangely, changes were happening. That became evident when he moved on to the placement that he went to next, evident when he moved on to the placement that he went to next, which was a sort of lead tenant model, because he was by that stage, you know, I think, just over 16 and he could move into that and he’d been in that new program for about six weeks. We got a phone call from the people who ran it and they said, goodness, you know, I don’t know what you did with him out there, but you know we had his whole history and we read his history and he’s just been fantastic here and I was going phew, because I honestly had not thought that we had achieved what I’d hoped we could, but we did.

Colby: 20:32

That’s an important thing. I think that’s a very important experience to have in this area of work. It’s part of the reason why I think it’s really important that we reflect on young people’s journey through our involvement with them, because the changes are often small and gradual.

Adela: 20:54

Indeed.

Colby: 20:55

But I’ve always found that they undoubtedly occur. They just take a while. And also the other thing is that sometimes we’re just not even around to see the full realisation.

Colby: 21:11

And then I also reflect on and this was something that came from an earlier podcast with Graham Kerridge which I might have mentioned to you. In the previous time we chatted about the human capital element and and also the intergeneration you know, like impacts of of turning a life in a in a slightly or largely different direction, and and the impact that has on partners, children, grandchildren yeah well, um yeah.

Adela: 21:41

Well, this young man that I just referred to has just recently got married, and one of the lovely elements of the work that we all did at Hurstbridge Farm is that in almost every case, every case, the various young people have maintained a connection with one or other of the people who worked there throughout the years. So, you know, I only became aware that he’d got married recently because I think he had sent something from Facebook to one of the workers who he had really worked well with, because obviously he wanted us to know that he’d got married and that he was happy. And indeed we were happy that he was happy, and I think I said, you know, at the start of our first podcast, what was I aiming for? People used to ask what was I aiming for?

Colby: 22:55

A great aspiration, an ordinary life? Yeah, you’re reading my mind, adela. I was just about to remind you of that.

Adela: 23:02

Yeah, and he’s got an ordinary life. He’s just got married, you know, his adult life is beginning in another direction and for me that’s enough. That’s actually more than enough, really to see a product and an outcome, which I think is, you know, really it’s really important to be able to say, well, I achieved, or we achieved, that outcome, and that outcome has a tangibility in the real world. And it doesn’t have to be flat. It can be very, very mundane, because ordinary life is pretty mundane, but to be able to be comfortable and happy in it is really important. Yeah, yeah. So you know, it was a nice outcome to hear of.

Adela: 23:57

And I’ve, over the years, heard, you know, some people have struggled more than others, of course, you know some people have struggled more than others, of course, but in terms of their struggle, they have struggled with less dramatic issues than they otherwise, I say, would have. Some people might say might have. I say would have, because we all know, you know, what outcomes can be if interventions don’t succeed. So when I was, you know, asked to write this proposal for a model, where did I go? I went to look at models that worked, yes, look at models that worked, yes. So I think sometimes we in Australia can get a bit sort of startled and stargazy by models from overseas because they’re from overseas.

Colby: 24:57

Mm-hmm.

Adela: 24:58

But because they’re from overseas doesn’t mean anything actually.

Colby: 25:03

That happens overseas as well, when I work overseas as well, does it?

Adela: 25:06

That’s interesting.

Colby: 25:07

Yeah, I’ve never been more highly regarded in my work than in other countries.

Adela: 25:13

There you are. Yeah, I don’t know what that’s about exactly, but it must be something to do with some kind of self-talk that makes us regard people whose work perhaps we don’t know as well more highly or differently, but it is actually something that I think can really get in the way of good work and developing models that work for our culture, in our environment and in a society with our ways of seeing the world, and Australian values are quite different to values in other parts of the world. But our kids, you know that’s the circumstances in which they’re reared. So at the time of course we’re talking about 2005 was when I was asked to put together this proposal and we were all leaning towards, very strongly towards the work of Dr Bruce Perry, bessel, van der Kolk, dan Hughes, the people who really strongly espoused understandings of complex trauma, and lucky that we were, because this was the client group that we were actually designing a model for. We were designing something that had to work for children and young people who had experienced complex trauma, because they don’t cross all the thresholds to come into any sort of out-of-home care. Unless that is the case, they have to cross all the legislative thresholds, all of which imply quite significant harm. So again, you know that’s what I had in my head that we had to actually match the model with the actual needs of the children for whom I was trying to design it.

Adela: 27:35

Now I want to read a paragraph. I often read this paragraph when I’m doing training. You’ll be familiar with it. Anyone who’s familiar with Bruce Perry will be familiar with it. It’s very short.

Colby: 27:46

Go ahead. I’m not monetized, so I don’t think you two can demonetize this.

Adela: 27:54

This is out of the boy who was raised as a dog.

Colby: 27:58

Yeah.

Adela: 27:59

Traumatized children tend to have overactive stress responses and, as we’ve seen, these can make them aggressive, impulsive and needy. These children are difficult. They are easy to upset and hard to calm. They may overreact to the slightest novelty or change and they often don’t know how to think before they act. Hence why star charts don’t work.

Adela: 28:28

Before they can make any kind of lasting change at all in their behaviour, they need to feel safe and loved. Unfortunately, however, many of the treatment programs and other interventions aimed at them get it backwards. So that was a very clear message to me don’t get it backwards. They take a punitive approach and they hope to lure children into good behaviour by restoring love and safety only if the children first start acting better. While such an approach may temporarily threaten children into doing what adults want, they can’t provide the long-term internal motivation that will ultimately help them control themselves better and become more loving towards others. So now I’m just going to share a little bit about what it was like developing a model that had that as its foundational thinking, because it was alien to many people to operate in that way. More services than not hoped to, as Bruce Perry says, lure children into good behaviour. Hence the star chart comment from the book.

Colby: 29:51

Yeah, with rewards as the lure.

Adela: 29:55

And there were times when we had started Hurstbridge Farm, when I used to drive home it was an hour’s drive from Hurstbridge to where I lived at the time and I would sit in my car driving and you know, mulling over the day and what we’d done and I’d be thinking do I know what I’m talking about? Am I bonkers? You know? Am I leading things in the right direction? What are we achieving?

Adela: 30:34

And I had to be brutally honest, I lost good collegiate friendships during that time because people would say really hurtful things to me about how misguided I was and how we were not setting enough limits for the children, and many, many things that demonstrated that people did not understand. And sometimes I’d get home and I’d run in the door and read that paragraph to myself because I wanted to remind myself of what I was doing and what we were doing as a group of carers together in that therapeutic milieu and remind myself that it was okay and we were on the right track. But there were comments made to me that were really hurtful and from colleagues who I’d really valued in the past, and so I suppose that’s part of what I was talking about at the start, about the hardness of doing this work.

Colby: 31:43

Yes and doubt is common. Self-doubt is common as mud.

Adela: 31:55

And the actual, sometimes quite hurtful responses that people would say as if I had no idea what I was doing. But thankfully, I’m a Cancerian, and one of the qualities of a Cancerian is tenacity, and I do possess quite a bit of that, and one of the qualities of a Cancerian is tenacity, and I do possess quite a bit of that. So I kept reminding myself, and I also kept reminding myself of the other work that I’d done and the reading that I’d done in putting the model together, because I didn’t only draw from the work of Bruce Perry, vandenhek and Hughes. I also drew from this amazing book, which was based on the work that had been done in the UK for decades.

Colby: 32:42

Yes.

Adela: 32:43

You know, people like Adrian Ward, who was one of the editors of that book and who I later met, people who ran the Mulberry Bush School, people who had been operating in a similar way to what we were doing at Hurstbridge and what we proposed to do, because that was source documentation that I was drawing from for sometimes 70 or 80 years, yes, grounded in the work of people like Winnicott and….

Colby: 33:19

Dr Drysdale.

Adela: 33:20

Dr Drysdale, all of those really good thinkers who put together longstanding and reliable months of books. So they’re the two main source documents. When I was putting it together I drew from Plus a couple of places that were very strongly grounded in trauma and attachment understandings in America. One was a place called Villa Santa Maria, which was in New Mexico, and another place called Chaddock, which was near Chicago, and again there were lots of their approaches that were brought together and sort of dovetailed in with Bruce Perry’s work.

Adela: 34:10

So when we talk about Hurstbridge Farm, I wanted to mention those, because I think sometimes people say oh, you know, adela just wrote that sort of off the top of her head. Well, I didn’t, no, I didn’t because I wouldn’t, because you can’t do that. If you’re going to produce something and devise something that is really going to have some gravitas, it’s got to have been based on something else that has had longevity and been tried and tested, because what kind of an idiot would I be, you know, to just dream something up and put it into action. So very important, I think, for anybody who’s drawing together and writing a model of new, a new model of care, to actually base it on the work that has gone before. Yeah, because otherwise that’s a fairly egotistical approach which you know doesn’t fit and doesn’t fit the needs of kids.

Colby: 35:27

I think we live in times where every agency wants to develop their own model. You’re right, yeah, and we also live in a time where evidence-based practice is reified. Yes, and that does get me thinking sometimes that when people kind of go it alone and look on, a lot of the question, a lot of the evidence is ethnographic in this. It’s so hard to do research in this area. You talked about the kind of people who do their own thing, but most you talk about Hughes, you talk about Perry Van der Kolk. You talk about Hughes, you talk about Perry Van der Kolk. I mean, they worked in this space for a very long time.

Adela: 36:14

A long time.

Colby: 36:21

And they operationalised their thoughts into an approach, and likely also in some ways, based on those who’d gone before them. So you, know Dan. Hughes, I would imagine, was heavily influenced by the work of Bowlby, for example.

Adela: 36:32

Oh, absolutely yes.

Colby: 36:35

My concern is there is such a plethora of agencies wanting to present their own model, and part of that, I think, is because we have competitive tendering environments.

Adela: 36:48

Yes, I agree.

Colby: 36:50

So agencies are trying to present a point of difference to their competitive tenderers. So, rather than, as you would say, drawing on everyone, drawing on the work that is tried and tested which I think they probably do to a certain extent, but they’re also wanting to bring something different. I think is what you’re saying and, if I understand you correctly, that concerns you from the point of view of departing from established knowledge and approaches that work.

Adela: 37:35

Yes, well, I can’t see other than what you’ve just referred to. I can’t see a good reason to not apply principles and tactics that have worked for 80 years in some settings again.

Colby: 37:57

And the Mulberry Bush School. Mulberry Bush would be probably one of the best examples of that.

Adela: 38:03

One of the best. And I must say, when I was in the UK I did go and see a few places and when I saw those places I could see coming to life why they worked. And people may or may not be familiar with a documentary that was made about the Mulberry Bush School in well, it was released in 2007,. I think it was called Hold Me Tight, let Me Go, and I presume it’s available still or perhaps you can see it on YouTube. But basically they had a documentary crew come and spend substantial amounts of time at the school and obviously take film of a lot of interactions and situations that they were dealing with and then presumably sit down and edit that into a watchable format. The documentary itself goes for, I think, almost two hours. It’s quite a lengthy piece of work. But when I had first started Hurstbridge, it was shown at the Melbourne International Film Festival here, was shown at the Melbourne International Film Festival here, and my daughter, who was actually working on the film festival, said oh, you have to come and see this documentary about a place in England because it’s what you’re doing. It’s what you’re doing at the Hurst Bridge. So I went to see it and I thought, well, thank you to my daughter because it felt so you could see its effectiveness. It was just fantastic to watch.

Adela: 39:59

And then I went there when I was in the UK a year later a bit more than a year and actually saw some of the children I’d seen on the documentary and how they had prospered and how far they’d come along as a result of the interventions. And I remember I was kind of constrained because they said you just have to sit quietly, can’t say anything or be involved in anything, just sit in the corner and be an observer. And I watched one of the children who in the documentary had been very troubled and he was leading the discussion about how they were going to do the end of the year nativity play and he was so calm and grounded and centered. It was palpably different to the way that he had been. And I remember I had just had tears running down my face because of the change in that time.

Adela: 41:04

And you know they were doing that again and again and again, reliably doing it. So people could send. You know people don’t send children to the Mulberry Book School for no reason. They send them there because they reliably have a model that works. And now I sit back and I think about those early days at Hurstbridge and how well terrifying which is probably the best how terrifying it was to know that I had actually taken that step and gathered together a group of people with an intent to undo harm and help children to heal. And I can now sit back and think, yeah, well, we did it, and they’re still doing it, because Hurstbridge Farm is still operating 18 years later.

Adela: 42:11

Well, we did it and they’re still doing it because Hurstbridge Farm is still operating 18 years later and it’s been reviewed twice with no changes substantial changes made to the model of care and it’s still working to produce those outcomes. So that’s quite exciting. It’s the possibly the only thing that actually makes me feel okay about the trauma of those drives, those long drives home, having had to process people’s criticisms and running in and reading that paragraph which, to be honest, I could probably almost recite.

Colby: 42:53

Yeah as a mantra.

Adela: 42:57

But again I think it goes to the importance of being able to use relationships to build safety and trust and do it in a very thoughtful and predictable way and have some confidence that it is actually going to produce the results that we wanted. I mean, one of the things that I drew from the model at Chaddock in the place near Chicago was that they had an approach which was very strongly attachment-focused and they were working a lot with Dan Hughes, working a lot with Dan Hughes. The way that they promoted attachment was that the children did not spend time on their own. They were actively engaged with during their waking hours.

Adela: 44:06

The only time they spent time alone was when, you know, they were having a shower or in the toilet, even when they were going off to sleep at night, until we felt that they could get themselves off to sleep. We followed what Chaddock talked about, which was to be with the child in a positive way, which was to be with the child in a positive way and I actually have a story to tell about that with a boy who radically altered in a very short space of time under that kind of administration of relationship relationship. He was in our second intake of kids at the beginning of 2008. And we used to meet the children hierarchically. So we wanted to very strongly deliver the message message as per all of the other models that I’d read that the adults were actually in charge and that we would take care of them.

Adela: 45:18

But I didn’t want them to meet the other children first. I wanted them to meet all the adults and feel confident and comfortable in those adult relationships. So I used to meet them first and then I would have my assistant manager go and meet them and then we’d go down through the hierarchy of the staff. So I went to meet this young man who was 10 years old, with significant attitude, and he was, you know, quite small.

Colby: 45:53

We smile because we know what you know. Other people would be like, well, he’s got an attitude problem. But you know, I mean our kids, I mean who doesn’t?

Adela: 46:04

Who doesn’t, why would they not? And why would they not? Why would they not? So he came out with his arms folded and he said this was, I think, quite a good use of a sort of pace-like response. He said first words to me were is it true, you don’t let kids out on their own up there? And so I thought now change the transaction. We don’t need to respond in like fashion.

Adela: 46:41

I said well done. I said you’ve been doing some research on us. It’s a great thing to do some research on a place you’re coming to. I’m sorry that you don’t like that bit of your research. But, yes, it is true. But do you know why we do that? No, I said well, the reason we do that is because we want you to be safe, and we want you to be safe no matter where you are and what you do. And I said I bet sometimes, when you’ve been out on your own, you’ve had a real whale of a time and, you know, done exciting things. But I bet also there are times when you’ve been in a bit of danger and a bit of trouble, and I bet those times you didn’t know what to do. Well, we don’t want you to have those experiences. So, yes, we do stay with you to make sure you’re okay.

Adela: 47:45

So he wasn’t convinced. He said, well, you won’t stop me. And I said well, we will do whatever we can to keep you safe. And I said here’s something else that I wonder if you know, but that if you do run off you’re, we run away with you. And he looked at me and he said what do you mean? I said, well, because we want you to be safe, our staff stick with you no matter what, and if you feel you’ve got to go, well, they’ll stick with you to make sure you’re safe.

Adela: 48:34

And he wasn’t in like that at all, so he sort of went oomph and walked off. And then he came back and said to me are you going back there now? And I said yes, that’s where I’m going now. He said, well, I hope you have a car accident on the way there and die. And I said, well, I hope I don’t, but I think you’re telling me that you’re a bit angry about what you’ve heard. That’s okay, we’ll work our way through that, that’s fine. And then I explained to him who was coming to meet him next and how it would all go on. Obviously, it wasn’t magic. It didn’t transfix things in that short a space of time, but it just, I think, gave him a taste that we weren’t going to be competitive.

Adela: 49:32

So that was February, beginning of February 2008. He never ran away, I might add. He only once walked up the driveway and the staff member who was working with him that day, doing you know good activities, said oh hang on a minute, mate, I’m just tying my shoelace, I’ll be with you in a tick. And he’d just turn around and walk back again. But fast forward to June. The end of June in that same year, 2008, I was driving into work one morning. It was about I don’t know half past nine, and as I got to the bottom of the driveway he was running around in his pyjamas. I mean, it was cold, you know it was June. Outside the house, adela, adela, waving his arms. So I wound down my window. I said what’s the matter? He said there’s no adult with me.

Colby: 50:43

So what did he do? He sought one out.

Adela: 50:46

So I said oh, how’s that? How come, have you just woken up? Yes, I’ve just woken up and there’s no adult with me. So we went and found out what had happened was he was fast asleep and the worker in the house had gone up to get some milk for his breakfast. So he happened to wake up at exactly that minute. Happened to wake up at exactly that minute. However, the message is clear He’d actually got to quite like having an adult who cared about him with him, and so, you know, we saw enormous changes in him, and in some ways, we hadn’t seen the extent of the change until that morning, when there wasn’t anyone with him, and we realised that he had learnt to accept being cared for.

Colby: 51:47

While I sit here and listen to you, Adela, and thinking about why I wanted you to come back onto the podcast. You’ve talked about the importance of relationships and relationship-based practice. You’ve also mentioned the importance of neurobiology and the neurobiology of trauma, thinking principally of Bruce Perry, and I think what I’m hearing you say is that it’s about the order and sequence. It’s about sequencing our work?

Colby: 52:29

Yes, it is, and that’s what the neurobiology of trauma brings. It’s about. This is actually where you start and this is where you go next, and this is where you go next, and the relationship is the containing environment yes, and you can’t substitute anything for that it you’ve actually got to go through those levels of connection.

Adela: 52:57

Now you can tag team a little bit because you know in a therapeutic milieu I can tell you how many times in a day I used to have staff come and say, oh, I need some space because it is intense. But that’s when you tag team. But if you do the building of relationships correctly you can do that, because kids are not developing only one relationship to rely on, which is what I discovered in the institution that one relationship might be great but it’s only going to work when you’re there. So what we used to really focus on at Hurstridge was developing those relationships across the board.

Adela: 53:49

That was what Chaddock talked about in their writing and also the Villa Santa Maria. Those relationships were transferable to a certain extent. I mean, obviously people are people and they have their certain quirks and you know personality, styles and they’ll actually bring the relationship to life in a slightly different way. But the underpinning of that relationship, which is the certainty of being cared for, the reliability of adults as protectors, the reliability of adults as people to like you, value, you, have fun with you, that can be shared and that can be an overarching experience.

Colby: 54:46

Yeah, a Prince William experience.

Adela: 54:48

With another boy. I won’t go into the entirety of his story but, again, very little capacity to trust adults. The day that I knew we’d actually got there with him was he’d been with us for about three and a half, four months. We used to walk everywhere with the kids. They didn’t walk anywhere on their own on the property it was 33 acres but anytime they went from one place to another they had someone walking with them, doing nice things, talking about you know what they were, but a presence, an adult, co-regulating, calming, valuing presence.

Adela: 55:37

And this particular day we were having a birthday celebration for one of the other kids and we were all on the balcony and had the barbecue fired up and this particular boy had said, had made a present for the other boy whose birthday it was. And he came up to me and he said will you walk with me up to the house because I’ve forgotten, you know the boy’s present and I want to go and get it. And when he asked me if I would walk with him, I knew that he had accepted being in the presence of a calming, co-regulating adult. Otherwise he would have just gone and I would have said hang on a minute, I’ll come with you or somebody would have. But no, he came to me and asked me to do it and I thought, hmm, okay, that’s good.

Colby: 56:39

So we hear a lot about trauma-informed practice, the importance of it, and I’d probably be well, I am one of the people who’s probably contributed to the narrative that trauma-informed practice is relationship, is the distinguishing feature of it, and developing relationship, and it is. But I think what you’re suggesting is that it’s more than that. It’s more than just the, it’s how you utilise that relationship, how you structure your work.

Colby: 57:15

Yes, and while I listen to you, I think what you’re talking about has real implications for staffing in community residential care. It also has real implications in foster care and kinship care and the ratio of adults to children.

Colby: 57:35

I’ve always had a saying, adela, when that, when I’ve been speaking to people who are starting out on their journey of having their own children, I’ll say to them never have more children than there are adults to attend to them. And then I’ll say but if you do happen to have more children than there are adults, have lots more children than you have adults so that the children have always got company, got someone to be with.

Adela: 58:06

But it’s really interesting, isn’t it you? What you say is so true, because it’s not just about what the adult says or does, but it is about the ratio as well. But it is also about the way in which you can generalize elements of those relationships so that you can tag team. And there will be times when children who have experienced such massive harm, particularly in the realms of attachment capacity, when they cannot let you go right, when they really really need you to be in the space with them to co-regulate, and sometimes, if it happens that you’re perhaps at the end of your capacity, that’s really quite hard. So that’s why a group milieu works effectively.

Colby: 59:11

Yes, I was having that very same thought. Across the podcast we’ve been talking about, there’s a couple of things One is just like.

Colby: 59:20

not every family is the same, neither is every endeavour in residential care and the residential care that works therapeutic residential care that works, therapeutic residential care that works. There’s a number of important things, components to that the opportunity for continuous relational connection through having not only other young people around, but having adults. It’s got to be staffed well, though for that. Adults it’s got to be staffed well though for that, and that’s that’s a message that that policy makers and funders really need to take on board strongly.

Colby: 59:58

Yeah, the. But the other thing I was thinking about as you were talking, was about the need for staff to have their own support in this space because, as you say, say some of the children, you’re not going to be afforded gratitude. I always think seeking gratitude is a fool’s quest from young people. Some adults will say we’re not praising you for doing well at school because that’s what we expect you to do. You know like it’s not noteworthy if you have a good day at school, if you flip it around. That’s not dissimilar to saying you know the argument against feeling like we should be validated all the time for the job we’re doing with, with our kids. No, that’s your job. Yes, that’s just actually your job to do a good job with the kids, but it’s as you said earlier, it’s hard work, it’s very hard and I think and and other other guests uh have well have also talked about.

Colby: 1:01:09

It is really important for staff to have the opportunity to feel, to reflect, to think about what they’re doing, to reflect, to reflect on their own reaction to the work and be supported in relation to that.

Adela: 1:01:25

I agree, and that is really, I think that’s incredibly hard to achieve. Some people say, or have said over the years, that Hurst Bridge Farm worked because of the farm environment. But actually I mean, yes, sure, that’s part of it, but that is not why it worked. That’s part of it, but that is not why it worked, because the work was in the relationships and how we used the relationships as vehicles for our knowledge of what needed to happen. So we know that kids, when they first came to Hurst Bridge, they could not regulate their presentation, they could not think effectively, they were not in a calm place inside their minds and they didn’t like themselves very much and we did all sorts of things. And I think one of the key elements is to not lower expectations but alter expectations. So when I used to say this many, many times in a day to the staff there times in a day to the staff there it’s not actually that I’m asking you to validate when a child is unpleasant towards you. What I’m suggesting is that if you can neutralise it neutralise it you’re better off in terms of your own response and what the child gets out of it. And that related directly to all the things that I read particularly Bruce Perry’s work about kids needing to like themselves first.

Adela: 1:03:30

I can remember an interaction that ended up with one of these erstwhile colleagues of mine ringing me because a child had been quite difficult with their visiting child protection worker and the staff, as always, had taken a decision internally not to humiliate them or shame them in the presence of that worker. So, yes, we would deal with it, but we would deal with it when they had gone and then I’d get a call from that person’s manager saying what are you doing up there? You know that he was really rude to whoever the worker’s name was and your staff member did nothing. And I said that’s right, they did nothing and let me explain why they did nothing. Went through what I, you know, just talked about and said can I tell you that right now that kid is out in a car with that worker unpacking why they got so upset when the child protection worker was there and that worker will try and go through it with them and help them unpack that until they have actually got somewhere. Even if they don’t manage to do the whole thing, they will keep going until they’ve got somewhere.

Adela: 1:05:07

And the reason they’re doing it in a car is because when you had little kids, what did you do if they wouldn’t go to sleep? You’d put them in the car seat and drive around the block a few times. We are helping that young person to regulate and to soothe. So please don’t tell me we’re doing nothing. We’re not doing nothing, but you can’t see it. And we had gone out of our way to help, you know, to visit and explain how we did what we did. But of course, until you saw it, it was impossible to know I like.

Colby: 1:05:47

I like the example of the car. I think it’s a very good example of the sequence. Yeah, I always in my own work, I always say you know, what do we do for babies? You know, we spend a lot of time thinking about their experience, responding to their experience, without them having to explain it to us Exactly. You know, thinking what’s going on for baby all the time. And then, yeah, and we didn’t expect them to regulate, we helped them regulate, and all of these kind of ideas. Some people will say, well, you’re just babying the children.

Adela: 1:06:30

But you know, I yes, I think we might have talked last time, but I’ve certainly.

Colby: 1:06:35

I can easily dispel that notion. When you think about um, what we do, a person’s needs are the same whether they’re one or 101 what they their relational care needs and their needs more generally. It just looks different in how you operationalise it. So we’re not babying the kids. What we’re doing is we’re filling in the gaps.

Adela: 1:07:00

Well, we are, and one of the things that I think that we if I said it once, you know, we must have all thought it and said it hundreds of times at Hurstbridge, which was Bruce Perry says you have to go to the lowest part of the brain implicated to create neurobiological change, and he talks really volubly about the amount of repetitions of corrective input that you have to provide. So if you think about that, that’s all we were doing that day. We were going to the lowest part of the brain implicated and we were going over it again and again and again, in a calm, non-punitive way, until even one little notch of awareness was achieved.

Colby: 1:07:56

Yeah, yeah, and we do this for years, you know, with our babies and young children and, like you were reflecting on a little bit earlier, I’ve had my doubters and the doubts rubbed off a bit.

Adela: 1:08:13

It’s always that, yeah.

Colby: 1:08:16

And it’s always been a challenge to advocate for therapeutic care for our children and young people. I think part of that has to do with other species in the animal kingdom. Don’t have experts telling them how to raise their young.

Adela: 1:08:37

We’re the only ones that have Exactly. But our young are dependent for so much longer than anyone else in the animal kingdom.

Colby: 1:08:44

And they’re capable of so much, and they’re also equally capable of a life that’s unproductive from a broader point of view. So there is complexity there that we need to acknowledge and tailor our approach to caregiving. We do that in the home anyway. Our kids aren’t all the same.

Adela: 1:09:09

Well, we do, and one of the things that I think is a really important skill for people who work in this field, with these kids who have been really impacted by complex trauma, is the skill to be able to let things wash over you. So you know when kids I don’t know how you go with expletives on your podcast do you commit them or do you blake them out?

Colby: 1:09:38

Go ahead, say what you need to say.

Adela: 1:09:41

Well, when kids say things you know to me, like oh, get fucked, or this or that or the other, if we buy into that we say goodnight really, because those are defences. We have to recognise them as defences and I have never been a person to buy into any of those kinds of expressions. And in fact I’ve got a million stories I could bore you to tears, you’d probably fall asleep. But one story I think really sticks with me we had, you know, in our first intake of young people that we had at Hurstbridge, we had probably eight of the young people who no one could work with.

Colby: 1:10:36

Yeah, they would have recorded them and sent you the most complex, troubled population of kids.

Adela: 1:10:43

We had, you know, children who’d had sometimes 42 placement breakdowns before coming to us, sometimes 42 placement breakdowns before coming to us. I said to the staff for that first year, when we were in about September, october, I said I would like let each of the kids know that I would like a Christmas list from them. I’d like a list of what I like for Christmas. And they said, yeah, right, that’s going to be easy. And I said, no, it won’t be easy because they won’t believe it. They won’t believe that we care, they won’t believe any of it. But we’ve just got to stay right and true and calm and see how we go. I still have the first list I got from the first child because it reminds me of the importance of relentless kindness, right? So, anyway, we got one or two and, to cut a very long story short, there was one in particular who’d had, you know, some pretty horrific childhood experiences, who just didn’t, wouldn’t do it, wouldn’t you know? No, I’m not going to do it.

Adela: 1:12:08

So I think about the beginning of December, I was walking out of the office building and she was leaning up against the wall and she said something like well, so when are we going to go and get this fucking Christmas present, then Now some people might have said, when you speak to me nicely, well, what would that have done, you know? So I just said now, yes, I went and got my bag and my car keys. And we got in the car and went to get it and on the way there I won’t tell the whole story because it’s very personal information, but on the way there a whole story came out about why this young person didn’t like presents and Christmas and it was an actual experience that she had. So very important not to get caught up in the. You know the niceties of nice behaviour At some point you can, but not at that point.

Colby: 1:13:35

Yeah, the importance is to avoid debate, to get involved in the behaviour and respond more meaningfully to the reasons why you’re seeing it. Adela, I could talk to you again. We could talk for hours, I’m sure maybe, maybe the next conversation we have can could be about how you I’m just thinking about this last little story how you explain to people, um, to that we it’s important to defer social niceties to another time.

Adela: 1:14:15

Yes, I think that’s actually a very good point.

Colby: 1:14:18

The reality is we don’t berate our babies for throwing up on us pooing on us weeing on us in the middle of the night when we’re trying. We don’t berate them for throwing whatever at us for spitting their food out. There’s a time to provide a corrective response, but there’s a whole lot of stuff that has to come before that.

Adela: 1:14:45

Has to come before that and it’s got its solid grounding in neurobiology because it’s go to the lowest part of the brain implicated. And I used to say that again and again and again to staff, because if you don’t go there you can’t go anywhere. You must go to that place because you’re building up from that place and you’re building up from that place with what the young person didn’t get in the first place, which is love and kindness and care. So you kind of have to say, okay, this is like a large baby walking around.

Colby: 1:15:34

People also take exception to that.

Adela: 1:15:37

Well, yes.

Colby: 1:15:38

Yeah.

Adela: 1:15:39

But this is what it is and sometimes you know, at a certain point you always, like you, can sense the point in the relationship where you can start to introduce that young person to some of the metaphor. So that same young person rang me up once, ages after leaving in a not very good state and, as we all know, anger is a couple of stages up from despair. So I did something which I thought might make them angry, but even if it did, it was probably better than despair. So I sent this young person a photograph of my hand, like that, my palm up, and the response was WTF. And then I texted back and I said can you not see it? And I knew it was provocative, but I knew the young person well enough to be able to do that.

Adela: 1:17:02

And the response was see what? And then I rang and said your hope, it’s in the palm of my hand. I’m looking after it. Until you can get it back, I’ll give it back to you. I’ll give it back to you now if you want it, if you’re ready for it, but if you’re not ready for it, I’ll look after it now, forever after. That has been a means of communication between us, so it’s kind of somewhere around Anne Hughes and Pace and metaphor as well. But in difficult situations in past times probably not so much in recent times but in times where you know things were a little bit tough I could just go and she knew exactly what that meant.

Colby: 1:17:57

Yeah, Well, Adela, again it’s been wonderful speaking to you, and if you’re going, we’ll probably have another conversation.

Adela: 1:18:07

Oh, I’m going yeah.

Colby: 1:18:09

About what I was just mentioning earlier, but thanks again.

Adela: 1:18:12

No problem, good to do it. See you, colby.

Colby: 1:18:16

Bye for now. Thank you.

The Hidden Strengths of Residential Care: Challenging the Status Quo with Dr Jenna Bollinger

Relationships: The Cornerstone of Stability in Out-of-Home Care

Dr. Jenna Bollinger’s groundbreaking research on stability in residential care challenges conventional thinking about what makes children and young people feel secure. Traditional measurements of stability in out-of-home care focus primarily on counting placements over time, suggesting that fewer moves equals greater stability. However, Jenna’s research reveals a more nuanced reality that practitioners, policymakers, and carers need to understand to create truly stable environments for vulnerable children.

The current system often defines stability as remaining in a single placement for a defined period. Yet Jenna’s research uncovers that children can remain in a placement for extended periods and still not feel stable. As she eloquently puts it, “If I was just told I have to leave my house today, I’m just told I have to get out for no reason and I don’t know where I’m going, I could be in my next house for 12 months, but I don’t know how secure I would feel.” This powerful insight reveals that stability is about much more than physical placement—it’s fundamentally about relationships.

Through extensive interviews with young people who had experienced residential care, Jenna discovered that those who formed strong connections with staff members felt a profound sense of stability, regardless of other factors. One particularly moving moment came when a young man corrected her interpretation of his experience. When she suggested that staff caring about him made a difference, he firmly stated, “No, I felt loved.” This correction highlights the depth of connection these young people need and can experience in residential care settings when relationships are prioritized.

This research challenges the commonly held belief that residential care is always inferior to other placement options. While Australia has one of the lowest rates of residential care use in the world (around 5-6% compared to Israel’s 95%), the outcomes may not necessarily be worse when considering the different starting points of children placed in various settings. Jenna points out that research rarely differentiates between care leavers from different placement types, making it difficult to accurately compare outcomes.

Another significant insight from Jenna’s work is the concept of “traumatized organizations.” When agencies responsible for caring for traumatized children become traumatized themselves, they struggle to provide effective support. Reflective practice, especially when implemented at leadership levels, can help organizations remain healthy and stable. As Jenna notes, “For an organization to work effectively, we need to start at the top and make sure that everything going on at the top is stable and healthy.”

Jenna’s “Secure House” model provides a practical framework for creating stability in residential care. The foundation is safety, the walls represent connectedness to consistent staff, the ceiling represents genuine care, and the roof encompasses training, supervision, and trauma-informed approaches. Additional elements include good matching, planned transitions, appropriate use of casual staff, and ongoing relationships with former staff members. This holistic approach recognizes that while change is inevitable, it can be managed in ways that preserve relationships and stability.

The research also highlights the importance of capturing diverse voices in understanding the out-of-home care experience. While we often hear from successful care leavers who have the language and connections to share their stories, we rarely hear from those who end up in the justice system or who didn’t even recognize they were in “residential care.” Understanding these varied experiences is crucial for developing truly effective systems of care.

You can listen to the podcast here:

You can watch here:

About Jenna:

Jenna has a Masters Degree in Forensic Psychology from the University of New South Wales, and a PhD from Monash University, where she investigated the experience of, and capacity for stability in, residential out of home care.

Jenna has worked in out of home care in different capacities since 2012 and is currently the Director of Psychology and Clinical Services for Knightlamp, which consults on assessment and implementation of therapeutic programs in out of home care across Australia.

Jenna also conducts a variety of assessments, including therapeutic assessments for out of home care, forensic assessments and parenting capacity assessments in the context of the child protection system.

Related Podcast Episodes:

Laura Steckley

Listen here:

Watch here:

Bruce Henderson

Listen here:

Watch here:

Transcript:

Colby: 0:00

Welcome to the Secure Start podcast.

Jenna: 0:04

If I was just told I have to leave my house today, I’m just told I have to get out for no reason and I don’t know where I’m going. I could be in my next house for 12 months, but I don’t know how secure I would feel. And so my research was trying to unpack what constitutes stability. Relationships are what makes stability. Those people spoke really highly of their time in residential care. They felt that they belonged to someone, that there was someone who cared for them, someone who loved them, someone who would protect them, someone who liked them. And I just don’t think the research bears out that residential care is as bad as what everyone makes it out to be. While the outcomes may be somewhat worse, maybe, not are, but may be somewhat worse for residential care, comparatively they may not actually be worse at all because they’re not on an even playing field at the starting point. Organisations become traumatised in and of themselves and so for an organisation to work effectively we need to start at the top and make sure that everything going on at the top is stable and healthy and therapeutic care is astonishingly difficult we need to have good staff who are trained who have really good supervision who have time together to build a connection as a team because fundamentally this all lives and dies with the staff.

Colby: 1:33

Welcome to the secure start podcast. I’m Colby Pearce, and joining me for this episode is a local, to me, expert in the design and delivery of therapeutic programs in out-of-home care here in Australia. Before I introduce my guest, I’d like to acknowledge the traditional custodians of the lands that we meet on. For me, it’s the Kaurna people of the Adelaide Plains. For my guest, it’s the Darug people. And I’d like to acknowledge the continuing connection the living Kaurna and Dharug people feel to land, waters, culture and community. I’d also like to pay my respects to their elders, past, present and emerging. My guest this episode is Dr. Jenna Bollinger. Jenna has a master’s degree in forensic psychology from the University of New South Wales. and a Doctorate of Philosophy from Monash University where she investigated the experience of and capacity for stability in residential out-of-home care. Jenna has worked in out-of-home care in different capacities since 2012 and is currently the Director of Psychology and Clinical Services for Nightland. which consults on assessment and implementation of therapeutic programs in out-of-home care across Australia. Jenna also conducts a variety of assessments, including therapeutic assessments for out-of-home care, forensic assessments, and parenting capacity assessments in the context of the child protection system. Welcome, Jenna.

Jenna: 3:24

Thanks for having me.

Colby: 3:26

Well, yeah, and thank you for coming on. And I’m really excited about doing this podcast because I think we both have done, well, you do, and I have done similar things in our work, particularly insofar as developing and implementing therapeutic approaches to care. Jenna, I’ve I just wanted to start off by asking you how you got into working in this space.

Jenna: 4:00

Yeah, look, it was by accident, actually. I was doing my master’s and I was working in hospitality and hated it. And so I applied for a bunch of jobs and I got a call back from a residential care agency and I did not know what residential care was. But I went. and went to an info session and did a bit of an interview, I think. And I got hired as a casual residential care worker. And that was where it started, really. So I worked on the floor. for about 18 months. And then I finished my master’s degree. And at that point, they happened to, you know, the stars aligned and one of the psychologists went off on maternity leave. So there was a one-year maternity leave cover as a specialist psychologist. And for whatever reason, I got it, which was amazing. And I think it was actually really fortuitous that I, it was only for one year because it didn’t actually end up that way she resigned and I got a permanent position but I felt really compelled to do as much as I could because I only had a year you know I didn’t have time to settle in and find my way and work out what to do you know it was sort of boots on the ground, full steam ahead. I only had a year to learn as much as I could. And because I’d worked on the floor, I had some sense of what happened and what didn’t work and what did work. And then I pretty much just stayed in varying capacities ever since.

Colby: 5:55

And you said… Interestingly, you talked about, you tried to learn as much as you could in that first year. I wonder who were the, what were the bodies of work or who were the people that you drew the most knowledge and or inspiration from? Look,

Jenna: 6:16

Bruce Perry was right up there for me. He was quite a remarkable inspiration for me. And I would, is… I would still say that his book, The Boy Who Was Raised as a Dog, is the most compelling and easily read and digested book about trauma that has ever been written. And I recommend it to anyone, really. I’ve got three copies of it myself. And I just think it’s a brilliant book. And I have read everything that he’s written. I’ve seen him in person regularly. And I think that the way he explains things is so readily understood and readily read. You know, you could read it like a novel. And so his work on brain development and trauma therapy were really influential for me. And since then, I have sort of expanded my reach, looking at Bessel van der Kolk. I’m a huge fan of Martin Teicher at Harvard. I don’t know if you’ve heard of him, but he is extraordinary.

Colby: 7:28

Tell me what’s extraordinary about him.

Jenna: 7:31

Well, if you ever have the opportunity to hear him speak, You’ll need to take some Ritalin first because he just speaks so fast that you’re basically, you know, you need something to help you keep up. He’s brilliant. And the work he has done on identifying the impact, you know, Bruce Perry talks a lot about type and timing of trauma, which we know, but Martin Teicher has worked on that. on being more precise. You know, in girls aged six to eight in the corpus callosum, this is some of the effects if you have this type of abuse. Like it’s extraordinary work and it’s really complicated and difficult to digest. So it’s not a beginner material, but his work is just extraordinary. So there’s been a lot of researchers that have influenced women me and the way I do things. Oh, I also really like Dave Ziegler. I think he’s fantastic too. I’ve seen him present. I’ve got a couple of his books. So, you know, it’s sort of all over the place.

Colby: 8:40

What does Dave Ziegler, what does he bring to the work?

Jenna: 8:45

Well, so he runs a facility in America called Jasper Mountain. And he has written a number of books and a number of papers as well that are also really accessible. You can read them. You can understand the impact of trauma on children. But because he runs sort of a residential facility for even young children, because it’s different over in America, I suppose. And so he’s got lots of approaches that are a bit novel. I think there’s this amazing facility and I haven’t been, I haven’t been, I wanted to go, but I think it’s in Oregon. So it’s a bit, it’s not really on the track holiday, but you know, and there’s, there’s horses and chickens and there’s, you know, a school on site, you know, it’s just, it looks like a really amazing sort of place to do really good work. And his writings are really accessible.

Colby: 9:44

Yeah. I’m getting the sense that the neurobiology, what comes really under the heading of the neurobiology of trauma is really influential in your work and your approach to the work. Are there any other kind of theory traditions or theoretical traditions that you find also of benefit toJ

enna: 10:07

you? Look, I’ve written a lot about attachment theory. I’ve read a lot about attachment theory, which is every psych student’s trauma memory. You talk to anyone who studied psychology and say attachment, they go, oh, God, no, Baldy. But I think when you look at it through the lens of trauma and development, attachment can really help as an important theory and an important way of looking at it. And I’ve had the opportunity to talk to a lot of people about about attachment and attachment theory and You know, they happily say, oh, I get it now. I get it now. I see it’s not just a strange situation. It actually applies to real life.

Colby: 11:01

I’ve written a little bit about attachment too. And it wasn’t ever a trauma memory because there may be different epochs, time epochs, but they never taught attachment theory when I was at university um i had to i got it yes people asked me when i appear on podcasts and i think how i really first started to become interested in it was part of a an assignment in my masters where we were all split up to do developmental domains researched them brought a paper on them and i got social emotional so um that’s where There were some precursors to it, but attachment theory became important then. And I agree with you. I think attachment theory also provides a very strong explanatory basis for things that… for when parental care goes seriously awry.

Jenna: 12:01

Absolutely. Couldn’t agree

Colby: 12:05

more. Yeah. And you… I mentioned when I talked about your bio a little bit earlier, you researched residential care as part of your Doctor of Philosophy project. Can you tell me, tell the people who watch and listen to this podcast all about your research and what you found?

Jenna: 12:30

Yes.

Colby: 12:31

Yeah.

Jenna: 12:31

So my PhD was looking at stability in residential care. I was just looking at it in New South Wales, but I don’t imagine that findings would be massively different around Australia, but I haven’t done that. So I was interested in looking at stability because… Well, because decisions get made about where to place children in residential care. And, you know, I believe firmly that everyone does the best that they can do with the information that they have. But from my experience, there was very little frameworks guiding how decisions are made. It’s rather just a matching template that someone’s put together and you kind of hope for the best.

Colby: 13:18

Yeah.

Jenna: 13:19

And so I thought, well, what do we do with that? What do we do with that information? And so I wanted to explore stability, this sort of broad concept. And when I started looking at the literature, I found that not only is there not much research that looks at stability, there’s virtually none… There’s very little that looks at instability. There is virtually none that looks at stability itself. But I think I found two. I think I found two papers that actually looked at stability, not instability. And they found that there was virtually no effect of stability. Instability is bad. Stability, null. And I thought, well, that doesn’t make sense. It doesn’t make sense. So what do we do with that? So then I dug a little deeper and the conclusion I came to when I was looking at this sort of broad brush of stability and instability research is that they were measuring stability in basically a placements over time form. So X number of placements in X amount of time is stable. Y amount of placements in X amount of time is unstable. Pick a timeframe, 12 months, 18 months. If you have zero or one moves in that time, you’ve got stability. If you have more than that, you have instability. Let’s look at the outcomes. And I thought, well, if I was just told I have to leave my house today, I’m just told I have to get out for no reason and I don’t know where I’m going next. I could be in my next house for 12 months, but I don’t know how secure I would feel because, well, now I know I can just get kicked out. So is not moving placements for a period of time sufficient to be considered stability? Shock? The answer is no. And so my research was trying to unpack what constitutes stability. And look, to be honest with you, it’s really basic. It’s really simple. And I genuinely worried that the PhD wouldn’t pass because it’s so straightforward. But actually, it was really, really well regarded, really well regarded. And I think that’s because while nothing I found is jaw-droppingly remarkable, it puts an academic basis to what We all essentially know to be true, even if we haven’t thought about it that way before. And so essentially the findings were that relationships are what makes stability. For the young people that have strong, profound relationships with the staff members that they live with, they feel stable. They have good outcomes. And for those that don’t, they don’t feel stable and the outcomes are potentially if you’re depending on where they may find that stability from. So obviously remaining in a placement for a prolonged period of time is a fundamental part of stability. You can’t build relationships. You can’t have anything else, but it’s just not enough. It’s not the core features, not the defining feature of stability. Does that make sense?

Colby: 17:08

Yeah, yeah. There’s two things that I wonder about listening to you speak about. The first of it is, why were you interested in stability as a topic of research interest? The second bit I was going to say was probably more an observation, but of the last little bit, which was talking about relationships and connection. I wondered whether you considered belonging, a sense of belonging in that.

Jenna: 17:39

Yes, that was actually one of the findings, yes, quite literally. So, I mean, look, my thesis is massively long. You’re welcome to read it. But absolutely belonging is, was a key thing that was part of it. You know, it’s going to take me forever if I rattle through the thesis to try and find it. But that sense of having a home, that sense of belonging to someone. So one of my favourite quotes in the whole thesis is, All of my research was I talked to a young man who had had some really solid relationships with some staff he’d worked with for a long time. And he was telling me about the relationship he had with them. And he said that he felt loved. And I said, oh, wow. So it made a difference to you that you felt like they really cared about you. And he said, no, I felt loved. And he corrected me. I had undersold it. I underplayed what he was saying to me for whatever reason. And he said, no, I felt loved. And those staff, I mean, at the time it was a good couple of years ago that I interviewed him, but at that time he said that those staff knew his children, that he still called them if he needed a hand. And I would imagine that that was still going on now. And, you know, another thing, Actually, a few of them told me that the staff knew their children after they had left and they were still in touch with them. A number of staff had referred them to me for my research, so they had strong enough relationships that they could do that. And those people spoke really highly of their time in residential care. They felt that they belonged to someone, that there was someone who cared for them, someone who loved them, someone who would protect them, someone who liked them.

Colby: 19:40

Yeah, it’s interesting, isn’t it? When you contrast that with other roles in the sector, so for example, the therapeutic role, the role of the therapist, and especially long-term therapy with young people in out-of-home care, that’s something that has been, I guess, the mainstay of my practice over the last 30 years. And As a psychologist, we have different boundaries around our work, but it is the case, though. I have had the same phone number since about 2001. So the young people still contact me that I knew. Not all of them, obviously, but quite a number of them do. And I think that that’s, yes, it stems from feeling like they mattered. Yeah. To me. And we hung around. Yeah. Yes. You know, hanging around for them. And I wonder, the other part of my question was just about what piqued your interest in stability versus what did you think was the case in relation to instability before you did your interviews? I

Jenna: 20:55

don’t know. Look, as I said, I don’t think anything came out of it that I was like, what? Oh, my goodness. That’s amazing. There were a number of moments of, wow, that’s so cool, but very little was shocking. You know, no one said, oh, actually it’s having eggs for breakfast on a Saturday, where you go, wow, okay, fair enough. You know, it all made sense. It was about feeling cared about. It was about feeling safe. It was about… the staff showed up. What was maybe a little bit surprising and unexpected was that no one really talked about co-resident stability. That was less of an issue. I don’t know that anyone really raised it. If I asked about it, they’d all kind of, not all actually, a number of them would say yes. Yeah, that matters. But that didn’t really come up. And even then it sort of felt like it was a bit more of if it’s good, that’s great. If it’s bad, it’s bad. But if it’s okay, that’s fine. That doesn’t really matter. And I thought that would have been more of a feature.

Colby: 22:24

Absolutely. I do too. I think in foster care, where you’ve got multiple young people fostered in the same home environment and one of the children moves out, then I’ve always thought and observed that that can be quite destabilising for the children who remain in that placement. Residential care. one of the things, ways in which I’ve always thought about it is that it does provide an opportunity for stability of care, for stability of relational connection that is superior to foster care. And that’s one of those things that people would be like, Don’t say that. You can’t say that. No, no, no. Residential care, bad. Option of last resort. Option of last resort. Why would you want to send any child to residential care? You only send those who cannot be placed elsewhere to residential care. But there are… And it is one of the things that I like to pursue on this podcast. There are clear… aspects of residential care where there are opportunities and superiority, where it’s superior in some respects, and there are opportunities afforded to us with residential care that are much less vexed than with foster care. For example, family contact and family reconnection, I think much easier with residential care.

Jenna: 24:03

There’s lots that’s easier in residential care, I think. And I just don’t think the research bears out that residential care is as bad as what everyone makes it out to be. In Australia, we actually have one of the lowest levels of residential care use in the world. I think we’re at about 5%, 5% to 6%, whereas over in Israel, it’s at 95% residential care. Oh, look, I’ve done a little thumbs up.

Colby: 24:32

What

Jenna: 24:33

was that? It’s the way of doing things. out of high care, right? And all in between, UK and USA, about 13%, give or take. And so, but the research also shows that in countries with lower levels of use, those in foster care and those in residential care, they’re actually not the same at baseline. So while the outcomes may be somewhat worse, maybe, not are, but maybe somewhat worse for residential care. Comparatively, they may not actually be worse at all because they’re not on an even playing field at the starting point. But the research doesn’t necessarily suggest that residential care outcomes are worse because the leaving care research very, very rarely differentiates the groups of care leavers. So you can very rarely find outcome measures that striated for residential care, for foster care, for kinship care. So it’s very, very hard to actually identify whether the outcomes are any worse at any rate.

Colby: 25:42

Yeah, there is a serious dearth of good quality research into care leavers and I think your point about where they start is really interesting. And effectively, you would be needing to look at effect sizes, treating foster care and residential care as interventions and then looking at effect sizes to see. So you work with organisations who are delivering care. I was just wondering, Really keen to hear a little bit about your experiences of doing that. And in particular, what sort of work are you doing with those organisations?

Jenna: 26:28

So we do work with various organisations doing various things. Doesn’t that sound… suspicious. It just really depends on what they need. So, you know, sometimes we will advise on therapeutic care plans for foster kids, for whole agencies. Sometimes we deliver reflective practice to the management teams. Sometimes we work directly in the houses, you know, giving advice as to what the staff might need. And other times we do assessments of what’s happening and if it’s appropriate or whatever. So whatever is needed is kind of what we do. My boss delivers training. And so, you know, we do whatever is needed and with the various organizations who need things from us.

Colby: 27:29

Okay. You mentioned in there something piques my interest was the reflective groups with leadership.

Jenna: 27:36

Yes.

Colby: 27:36

Yeah. Tell us a little bit more about implementing reflective practice with leadership.

Jenna: 27:44

Reflective practice is a bit like attachment theory, really, and it tends to get a reaction from people until they do it. And once you do it, you tend to be relatively sold on it. It’s quite an extraordinary opportunity to reflect, but also to sort of recenter a lot of the work, you know, because we know that trauma is traumatic and working with trauma is traumatic, that organizations become traumatized in and of themselves. And so for an organization to work effectively, we need to start at the top and make sure that everything going on at the top is stable and healthy and untraumatized. And so starting at the top by doing the reflective practice, we can get everyone back on the same page. They can communicate with each other. They can reflect on what’s going well. They can reflect on what’s going not so well. They can help each other. There’s not so much of an agenda as there often is when you have those big team meetings where every minute is structured of people telling you all the things that they’re doing well. And so people have the opportunity to really talk about things. And by the end of it, you know, it feels a bit magical almost that people feel happier at the end of it. They feel more connected to each other and more positive about the work that they do.Colby: 29:18

It’s therapeutic.

Jenna: 29:20

Yeah. So we found all the hard parts.

Colby: 29:23

Well, I think, yeah, I think there’s a couple of things I would say is that, yeah, When people are able to be collectively in a leadership team a little bit vulnerable with each other to talk about the challenges, their own challenges in delivering the work. the response is often an empathic one and connection deepens. And I’ve spoken to, in various other podcasts previously, this issue of reflective supervision has been quite a significant one in terms of it being a very common theme of saying, one, it’s really good. Two, it really helps with the work. And also three, that there’s something in it for retention

Jenna: 30:22

as

Colby: 30:22

well, which relates a little bit back to what you were saying about stability and your thesis. And, you know, those relationships that those young people had in residential care, one of the factors that would impact that is the stability of the workforce. So that’s a very interesting thing. part of the work. Yeah. And traumatised organisations. I mean, every time I hear it put like that, which is not very often, I think of big organisations like our statutory child protection agencies, who are subject to a high level of scrutiny from time to time. And in some senses, they’re very large and probably unwieldy. And I often think about and turn my mind to how difficult it is working in those organisations from the top to the bottom. and how good it would be to… I think how much benefit there would be to the children to roll out reflective supervision from the top. I hate saying to the bottom, but let’s just say from the top and keep going. Yeah. Everyone has an opportunity to do it. And I have a little saying, which is… There is the old, there’s the meme saying that you see, which I’m ambivalent about, which is that the hurt people hurt people, which is kind of true, but a lot of hurt people don’t hurt people. But what I think is probably more true is that hurt people hear people. Yeah. heard people, hear people. And so when you’re in a reflective group where you feel heard and acknowledged in your experience, you are then better able to consider the experience of others.

Jenna: 32:41

Yes. I couldn’t agree more. And that was one of the things that did come out of my research was this sort of need for staff to be supported. to do their work. And exactly as you were talking about feeling heard, I think that one of the greatest challenges of the organisations is to communicate. And I think, you know, when I was talking to, you know, I talked to floor staff and they say, you know, we talk to management, we tell them we’re at capacity, we can’t take any more, we can’t handle this, this match is going to be bad. This is a bad idea. And the management say, cool, thanks for letting me know. And then they go ahead and do whatever they need to do anyway. But when you talk to the management team, it’s not that that’s not an accurate representation, but there’s so much more behind it where, you know, the funding bodies set up targets and if you don’t meet those targets you don’t get funded so if you’ve got one bed available and they’ve got a child that needs a placement fundamentally it doesn’t matter if it’s a good match necessarily you could you could push back i suppose but there’s a limit to how much pushback you can have and still get funded and so i mean i think uh some more of that backwards and forwards communication would really ease some of those relationships where the staff are feeling heard You’ve told us that you can’t handle this. And I hear you. Unfortunately, the funding rules mean that there’s nothing I can do about this. But as soon as we can do something about it, we will. What support can we give you to help you manage this, given the limits of what we can do? And I think those conversations don’t happen. And so the staff feel unheard and they feel put upon and their workloads increase because as soon as you put a new person in, it is harder. As soon as you change things, it is harder. And if the match is bad, it is harder again, right? And so they’re overwhelmed, they’re pressured. So they take leave. So then you put in casual stuff or agency stuff and then it explodes again. And we don’t have anyone feeling heard. We don’t have anyone feeling supported. When in the first instance, everyone was right. Everyone did the right thing. Everyone did the best that they could. And so some reflective practice with with everyone, with, you know, line managers and with floor staff and with whole management teams and with whole floor teams and everything in between, I think we can get somewhere a little bit more productive because, I mean, everyone has, I’m sure everyone can understand all of those limitations. You know, they’re all intelligent, competent people that I speak to and I’ve worked with and they would understand everything. those limits and we could work together better.

Colby: 35:56

If we understood each other’s experience

Jenna: 35:59

more. Yeah.

Colby: 36:00

Yeah. And I think, you know, when you were talking, I was thinking about, yeah, the floor staff and management as well. Management feel put upon by the funding bodies. Exactly. Yeah, the bodies that engage them to do it. And just all round, it is a difficult process. job and it’s a bit i think of it a little bit like this is that um across a long career talking to lots of children predominantly children recovering from a tough start to life i haven’t found that there’s many who like school

Jenna: 36:39

yeah

Colby: 36:40

but um but they have to go to school it’s the law and i think so there are always problems that cannot be solved cannot be solved But at least they can be heard about. And that’s almost as good, if not just as good, in many instances.

Jenna: 37:05

Yes.

Colby: 37:05

We can’t solve or change the situation, but feeling heard and understood and acknowledged about it is very powerful.Jenna: 37:15

Absolutely.

Colby: 37:16

Yeah. Apart from those challenges of staff and management, What else do you see as the challenges that exist in terms of delivering good residential care to children and young people? I

Jenna: 37:34

think probably one of the biggest challenges is that all organisations these days purport to being therapeutic. Trauma-informed. Trauma-informed care. We all do therapeutic care. No one says that they don’t. But therapeutic care is astonishingly difficult and it is not something that is necessarily happening all the time. And I think that helping people, helping organisations to understand what it means to be trauma-informed and what it means to have those really… considered, planned conversations with young people for everything to be considered. Every interaction is understood. Every interaction is thought through. That is astonishingly difficult for the relationship to be front and center is astonishingly difficult when we’re talking about attachment disordered young people who are not going to see your care and say, oh, gosh, thank you so much. That’s what I was after. Thank you. No.

Colby: 38:59

No.

Jenna: 38:59

They don’t. If they did, it wouldn’t be hard. But, you know, attachment trauma, I mean, sometimes manifests that way, I suppose. We probably don’t get called in to talk about those kids. But so much of the time it doesn’t. It manifests with testing and pushing and rejecting and damaging, not necessarily physically but emotionally and emotionally. To consistently show up and understand and feel hurt and cope with that is astonishingly difficult. Yeah. And I think that is the challenge for us for now, forever. I can’t really see that changing, which is why we need organisations to be less traumatised so that we can support staff better.

Colby: 39:54

And reflective… Circa vision is important in that key, really. I’m wondering if there’s anything else that you have come across that helps to detraumatize organizations. It’s a bit like a cure for tantrums in kids. If you can come up with that,

Jenna: 40:19

you

Colby: 40:20

are set. You’re like the family that invented the little umbrellas that go into the alcoholic drinks.

Jenna: 40:30

Yes. No, I mean, I don’t know. I don’t know the answer to that. I really don’t know the answer to that. I think, you know, when I did my research, I put together a model. of what I call a secure house, a stable house. And if I can find it really quickly, I’ll talk you through it. But it was, you know, this sort of this house that I designed, you know. In the end, I got it drawn up by a graphic designer because my version was done on, you know, paint, you know, with a square and a triangle on top and some, you know, handwritten and then on my iPad, you know, just writing in various things. And so, you know, sort of based on the analysis that I put together, I sort of put together this model of a home that is sort of has the key features in the, you know, the floor and the roof and the walls. And these are the key things that you need. But then, you know, you’ve got to have your roof and your windows and your front door. You know, you can’t have a house without four walls and a floor. But you don’t really have a house if there’s not a door and some windows either. So there might be slightly less room. necessary but but really necessary you know and so my house sort of takes that sort of form and so in the four main you know the floor is safety on the main walls we’ve got connectedness to staff and consistent staff on the ceiling we’ve got genuine care that’s that love that we talked about but then on the roof we’ve got training and supervision we’ve got trauma-informed care In the windows, we’ve got good matching and peer relationships. Coming out of the chimney, we’ve got pushback so that we’ve got the higher-ups pushing back against the agencies when they can and saying, this is not good, we can’t be doing this. And then you’ve got, you know, in the front door, we’ve got planned and communicated changes because change is inevitable. Staff will leave. Staff will retire. Staff will get moved to different houses. Young people will have to move for various reasons. And so that is part of life. Change is part of life. That’s why I put it on the door because it comes and goes. I thought that was quite clever.

Colby: 43:03

That is clever.

Jenna: 43:04

And then I’ve got a plant on the outside where we’ve got casual staff and ongoing staff contact, which were some of the other features. You know, casual staff are also an inevitability, but there are ways of doing it better, you know, ways of having pools of casual staff that work with various houses, that know the kids and know the staff. And so while they may not be permanent staff, they’re not randoms either. They’re known. They’re familiar. And that idea of ongoing staff contact. In this house, it doesn’t solve all the world’s problems, but I think if we put it all together, we’d probably be a little bit closer to solving those issues that are plaguing residential care. Because the staff are cared for. They’re supervised properly. They’ve got good training. We’ve got good casual. So if the staff need to take time off, it doesn’t destabilize the house for the other staff that’s left on shift or when everyone comes back from leave. You know, if we do it right, it’s just less hard for everyone all the time.

Colby: 44:15

So you’re in a meeting with the heads of the commissioning body, the funders, the policy makers. Invariably in this space, it’s the local statutory child protection agency. What are you going to tell them? What are you going to say? This is what you need to do to improve the quality of education therapeutic residential care or residential care for children and young people across our jurisdiction? What are you going to say to them?

Jenna: 44:53

Well, you need to fund it, which I think they do. I think the funding’s probably there. We need to have good staff who are trained, who have really good supervision, who have time together to build a connection as a team because fundamentally, This all lives and dies with the staff. You know, the young people, they are who they are and it is not their responsibility to make this work. You know, you can’t ask them to be anything other than who they are and to be loved as they are. So it lives and dies on the staff. So how do we get them to be as good as they can be doing this impossibly hard job? and that is that we need to support them. And, you know, the funding rules are what they are, so we can’t change that, really. We just have to support them and we need to listen, as you say, be heard.

Colby: 45:49

It’s interesting. That’s probably a piece of advice that can go all the way through their own organisation as well, looking after the staff. Yeah. Looked after staff, yeah. are more effective in their role.

Jenna: 46:09

Yeah.

Colby: 46:10

Yeah. Now, I had a question from my previous podcast guest, who was Ben Pryke and Susan Barton from the Lighthouse Foundation. I give my guest, and I’ll give the same to you, I give my guest an opportunity to ask a question for the next guest. Now, I actually, as we’ve been talking, I’ve been thinking this is probably been at least partially answered by you. I’ll read the question just so our listeners or watchers know what the question is. So the question was, how can we meaningfully integrate the voices and insights of people with lived experience into the development, delivery and evaluation of therapeutic residential care models or services, I guess?

Jenna: 47:02

Yeah. I reckon I’m going to answer this differently to how you think I’m going to.

Colby: 47:06

Well, okay. Let me tell you what I thought. Okay. Why I think there’s been a little bit of overlap is that in a way your thesis went some way along towards that. Is that how you thought I was going to answer it?

Jenna: 47:22

Yeah, probably.

Colby: 47:22

Okay. Well, you go ahead.

Jenna: 47:25

Okay.

Colby: 47:26

You go ahead.

Jenna: 47:26

All right. Okay. I don’t know. is my answer. And the reason I don’t know is because, all right, so this is a bit of a long story. So give me a minute. Let me give a bit of backstory. Through the course of other work that I do, I do a lot of forensic assessments and I interview people for upcoming court appearances. Through the course of that, I interviewed a number of people who were in residential care who didn’t know that they were in residential care. Now, you ask, I say, they hadn’t heard the term residential care. So some careful questioning, they could tell me that they’d been in a group home or a boy’s home, or they, you know, could tell me that there were staff and other kids, it wasn’t a family, but they’d never heard the term residential care. And so when we think about lived experience voices, they are crucial, but they’re The lived experience voices we usually hear are of remarkable young men and women who have done really well, who have the words, who have the language to talk about their experience, who have the connections to people who can say, hey, Jill, tell us about your experiences. Someone who wants to go to create and be a youth ambassador. Someone who wants to go into social work and psychology and do research. There’s a lot of PhD students with lived experience and they are remarkable. And those are the voices that we hear. You know whose voices we don’t hear? The young people in prison. The ones who are on the street, the ones who don’t have any connections to anyone, and the ones that didn’t even know they were in residential care, even if they saw my flyer on the side of the road saying, hey, were you in residential care? I want to talk to you. Even if they felt compelled to ring me, they didn’t know that that applied to them. So my thinking is we actually need to work out how to engage people not everyone necessarily, but a broader community of lived experience, young people, not just the ones who are doing well enough to stay connected and who can use their words. What about the ones with intellectual disabilities, the ones who have gone on into NDIS-funded accommodations? How do we hear everyone’s voices? Because I’m not sure that the voices that we hear are representative, even though they’re remarkable. And I want to hear what they have to say. I’m just not sure we’re covering everything that we need to with regards to lived experience. I’m hoping, I’m trying, I’m trying with a group of researchers at Monash to forward some research in this area. We are looking to pay attention to people whose voices have not been heard. We are looking to research. There’s been a lot of research about the pathways from out-of-home care into youth justice. There’s been remarkably little research into the pathway from out-of-home care to adult justice and the adult prison system. And there’s been a number of people that I have interviewed who have bypassed the juvenile justice system entirely. And they go straight from out-of-home care into the world and then randomly into the adult justice system. And we want to know what those pathways are. And those are voices we don’t get to hear too often. You know, what happened? What is that pathway? Is it more like the out-of-home care to juvenile justice pathway? Or is it more like… a different pathway. You know, if I ended up in prison, what is that pathway? Is it more like that? I don’t know. But there’s voices that we need to hear in order to inform our ongoing development. So Lighthouse Foundation, if you want to do some research with me, give me a call or if anyone else wants to.

Colby: 51:51

Yes, Lighthouse. Well, absolutely. And Lighthouse Foundation, I think probably themselves have captured a little bit of the picture here. I couldn’t agree with you more in what you’ve said. I think in order to capture the broader spectrum of care leavers, we need to follow them up. And the research with them is highly lacking. No one’s following them up. Our statutory child protection agencies, at least to date, there hasn’t been significant endeavour that I know of in the jurisdictions that I’m across, including my own, to really make sure we keep tabs on or have a relationship with our young people such that we can keep tabs some level of involvement with them. An organisation like Lighthouse is in a better position to track these young people transitioning to adulthood because they are a service provider and they provide services beyond 18. Another group that you mentioned, when you were mentioning the groups that we need to consider, are the care leavers who have their own children removed, which is quite, you know, which is, I’m not sure, I can’t say with any authority what proportion of care leavers that is the case, but that would represent a really significant challenge for our statutory child protection agencies that the children you raised had such poor parenting models that they were considered unsafe to raise their own children. Their parenting models, often their most dominant parenting model was the state as a parent.

Jenna: 53:57

Yes. Look, there’s a couple of brilliant researchers at Monash who have looked at early parenting in care leavers. And they might be interesting people for you to have a chat to, because I think from my conversations with them, that there’s also a whole lot of you know, oversight and intervention. And often I think they’re not even given much of an opportunity to parent. before having state intervention. So I’m happy to pass on some details to you if you’d like to have

Colby: 54:26

it. Yeah, I’d love to. I’m always open to hearing about other people I could have on the pod. And I was writing down David Ziegler’s name. I hope I spelled it correctly earlier. And listen, it’s been great to have you on. Before we finish, I tend to give my guests an opportunity to ask ask me a question without notice before we finish up. I’ve asked you a lot of questions. Is there anything you’d like me to respond to before we finish up?

Jenna: 55:05

What would you say is the biggest challenge facing residential care?

Colby: 55:14

I think that it probably is staff. Not that the staff are the problem, but in terms of how we look after the staff. And I do think that funding needs to take into account opportunities for ongoing reflective practice. See, the big challenge, I guess, in the work that we do is that We are the only species that has psychologists that tell people how to raise children. Yeah. So a lot of people are like, well… we know how to raise children. We remember being raised. We learnt as much from what our parents did well as what they did poorly. And we obviously have an instinct, just like every other species, the parents, the young has. I think part of it, part of the problem is amongst residential staff as well as kinship and foster carers is seeing the value in in being trained in therapeutic care so but also but also um i think ensuring that they’re looked after that they hang around they’ve got that stickability that that kinship carriers for example excel with you know because if they’re kin they do stick more um and that they think about what what they’re delivering. They spend more time being mindful and holding the young people in mind that they’re working with. I think those are challenges. I do think that there needs to be more money into residential care in order to support more reflective practice. I think reflective practice, my view is you need to have at least some guide a model that guides and becomes a framework for reflection, for supporting reflection and developing understandings. Which probably I could talk for a very long time about. But yeah, I think I agree with you. I think the staff is where we… should primarily be putting our focus to. And look, I would also say, as I’ve said before, I don’t intend to criticise stuff. It’s not my intention to make staff feel criticised for the job that they’re already doing. They’re doing the best they can, in my observation, the best they can with the structures and support and… funding that they have. And it’s unfair to put all residential care, residential childcare together because there’s great variability in what organisations like the Lighthouse, you know, for example, the difference between what the Lighthouse can provide, what is provided at Hurstbridge Farm and what’s provided in other residential childcare organisations. concerns. So I think getting consistency of residential care. So, you know, when we talk about research, see, this is what I mean, I could keep going. When we talk about research and we want to look at outcomes for residential care, we have to consider that not all residential care is the

Jenna: 59:16

same. For sure.

Colby: 59:16

And is that a problem? We need to perhaps be looking at um remedying that um yeah just like not all families are the same and you know foster care outcomes well how far down that rabbit hole do you want to go in terms

Jenna: 59:32

of tough research it’s really it’s why no one does it

Colby: 59:35

yeah yeah you’re undoubtedly uh onto something there

Jenna: 59:40

But

Colby: 59:41

look, as I said, thank you again for coming on and perhaps our paths will cross another time and maybe I’ll have you back again for another conversation if I

Jenna: 59:53

haven’t

Colby: 59:54

scared you off.

Jenna: 59:57

Thank you.

Building Hope: Lighthouse Foundation’s Legacy of Love

The Lighthouse Foundation: Transforming Youth Homelessness Through Relationships and Community

In a world where vulnerable children and youth often fall through the cracks of support systems, the Lighthouse Foundation stands as a beacon of hope. Founded 33 years ago by Susan Barton AM, this Australian organisation has pioneered a therapeutic approach to youth homelessness that focuses on healing through relationships, community involvement, and long-term support.

Susan’s journey began over four decades ago when a life-changing experience in Sri Lanka opened her eyes to the suffering of vulnerable children. Witnessing malnourished babies in dire conditions prompted a profound personal transformation. Upon returning to Australia, Susan discovered that while Australian children weren’t dying of severe malnutrition, they faced different challenges, with youth suicide rates among the highest in the Western world. This realisation sparked her mission to create safe homes for homeless youth, beginning with fostering teenagers who had nowhere else to go.

What started as Susan opening her home to vulnerable young people evolved into a comprehensive therapeutic model. The Lighthouse model isn’t merely about providing shelter; it’s about creating healing communities where young people can form meaningful relationships and begin their journey to recovery. Their approach has yielded remarkable results, with 87% of young people leaving Lighthouse never returning to homelessness again, effectively breaking the cycle of intergenerational trauma.

Central to Lighthouse’s success is their understanding that relationships are the primary vehicle for healing. Their therapeutic residential care homes provide young people with consistent, emotionally available adults who don’t just “do to” but “be with” children and their families. The organisation supports young people up to 25 years of age—far beyond what most services offer—and continues relationships through their “On For Life” program, recognising that healing takes time and that young people need ongoing support, just as they would in a family environment.

The Lighthouse model incorporates several unique elements that distinguish it from traditional approaches. Community committees surround each home, creating a network of supportive adults who act as surrogate extended family. Regular reflective practice helps carers understand their own emotional responses and how these might impact their work with young people. Their psychosocial screening ensures that everyone in the organisation, from therapeutic carers to board members, aligns with their values and approaches.

Perhaps most revolutionary is their approach to birth families. Lighthouse understands that children who have been abused by their parents don’t stop loving their parents—they stop loving themselves. By working non-judgmentally with parents and involving them in their children’s healing journey, they honour the importance of family connection to identity and recovery. Their Young Parents and Babies Programme supports young parents to heal from their own childhood trauma while raising their children free from inherited emotional wounds, embodying their philosophy: “We care for the parents so they can care for their children.”

The Lighthouse Foundation demonstrates that therapeutic residential care can be a powerful intervention rather than a last resort. By focusing on relationships, community involvement, and long-term support, they provide a model that challenges traditional approaches to youth homelessness and offers hope for meaningful, lasting change.

You can listen to the podcast here:

You can watch here:

About Susan and Ben:

Susan Barton AM founded Lighthouse Foundation 33 years ago and has dedicated her life to helping the most vulnerable children and youth. Her mission is to change the way Australia looks at the issue of child and youth homelessness towards a more therapeutic approach where we create caring communities where all young people – from babies to young adults – can feel safe, form meaningful relationships, and begin their journey to recovery.

Susan has co-authored two books on childhood trauma, was awarded an Order of Australia for services to youth in Australia, was named Melburnian of the Year in 2009, and was inducted into the Victorian Honour Roll of Women for her significant achievements and contribution to the Victorian community, in 2012.

With over fifteen years of experience in therapeutic residential care, residential communities, and educational settings, Ben brings a wealth of understanding and passion to his role at Lighthouse Foundation.

Ben honed his reflective skills at Fairways, an award-winning children’s services charity in the UK. It was during his time there, that Ben encountered Therapeutic Residential Care for Children and Young People: An Attachment and Trauma Informed Model for Practice, written by Susan Barton, alongside Rudy Gonzalez and Patrick Tomlinson.

Inspired by the Lighthouse Foundation’s values and vision for high-quality care, Ben joined the organisation in 2018 as a Therapeutic Carer, supporting children, young people, young parents, and babies in need of a secure base.

In 2021, Ben became the Manager of Youth and Family Services; leading Lighthouse Foundation’s nine therapeutic residential care homes.

Related Podcast Interviews:

Adela Holmes

Listen here:

Watch here:

Kiran Modi

Listen here:

Watch here:

Transcript:

Colby: 0:01

Welcome to the Secure Start podcast.

Susan: 0:04

And children grow in the love of someone. If you can hold with them and stay with them during that really difficult time, they’ll usually find a little spark of hope and see it through and get out the other side. Every time we open a home in a community, we build a community committee around that home and the um. The importance of that is that they’ve got all these surrogate parents and brothers and sisters and aunts and uncles and there’s a really deep responsibility that I’m a conduit for the young people who can’t tell their story to those who don’t know their story.

Ben: 0:45

And we contract all our forensic carers to engage in reflective practice. Children have been abused by their parents. They don’t really stop loving their parents. They stop loving themselves and we really see parents as an integral part of their identity and their healing process. And that was all the child needed. Really. He didn’t need to affix, he just needed to be heard. We care for the parents so they can care for their children. When I was a child, playing was very terrifying because it it meant abuse. Um, you’ve, you’ve taught me how to play with my children, so she was very grateful for that.

Colby: 1:23

Welcome to the Secure Start podcast. I’m Colby Pearce, and joining me for this episode are two representatives of an Australian endeavour providing homes and therapeutic care to the young people who need it, where they need it and for as long as they need it. Before I introduce my guests, I’d just like to acknowledge the traditional custodians of the lands I’m coming to you from the Kaurna people of the Adelaide Plains and the continuing connection the living Kaurna people feel to land, waters, culture and community. I’d also like to pay my respects to their elders, past, present and emerging. My guests this episode are Susan Barton and Ben Pryke of Lighthouse Foundation.

Colby: 2:13

Susan Barton AM founded Lighthouse Foundation 33 years ago and has dedicated her life to helping the most vulnerable children and youth. Her mission is to change the way Australia looks at the issue vulnerable children and youth. Her mission is to change the way Australia looks at the issue of child and youth homelessness towards a more therapeutic approach where we create caring communities where all young people, from babies to young adults, can feel safe, form meaningful relationships and begin their journey to recovery. Susan has co-authored two books on childhood trauma, was awarded an Order of Australia for services to youth in Australia was named Melburnian of the Year in 2009 and was inducted into the Victorian Honor Roll of Women for her significant achievements and contribution to the Victorian community in 2012.

Colby: 3:09

With over 15 years of experience in therapeutic residential care, residential communities and educational settings, ben brings a wealth of understanding and passion to his role at Lighthouse Foundation. Ben honed his reflective skills at Fairways, an award-winning children’s services charity in the UK. It was during his time there that Ben encountered therapeutic residential care for children and young people, an attachment and trauma-informed model for practice written by Susan alongside Rudy Gonzalez and Patrick Tomlinson. Inspired by the Lighthouse Foundation’s values and vision for high quality care, ben joined the organisation in 2018 as a therapeutic carer, supporting children, young people, young parents and babies in need of a secure base. In 2021, ben became the Manager of Youth and Family Services, leading Lighthouse Foundation’s nine therapeutic residential care homes. Welcome, susan and Ben. Thanks, colby.

Ben: 4:23

Thank you, colby, thank you for having us.

Susan: 4:24

Can we acknowledge the traditional owners of our land, the Wurundjeri people, and thank them for the beautiful country we live in.

Ben: 4:34

Yeah, we pay respect to elders past, present and emerging and we extend that respect to Aboriginal children, young people and families who entrust lighthouses with their care.

Colby: 4:43

Yeah, well, thank you for that. Now, was there anything about either of those bios or anything that you would wish to add at this point?Susan: 4:53

I don’t know, I’ve placed over a bit of time.

Ben: 5:01

Oh God, would that add to the bio? No, I was thinking Colby. It made me think about, uh, the podcast you had with lisa cherry recently, I believe it was, and it reflected on being a parent. Um, so just to add, that’s our professional roles, but, um, I’m also a father and a husband and take those roles with the same level of seriousness and care that we give to Lighthouse Foundation young people.

Susan: 5:27

Yeah, okay, and if you want a more personal one, I have six grown-up children and 12 grandchildren, and I would like to push for a 13th if my kids are cooperative.

Colby: 5:42

Well done, that’s lovely. I know if you’ve listened to a couple of the other podcasts. It seems to be excruciating for some people to sit and listen to their bios. Yes, on the one hand, and on another hand, there it’s almost an opportunity to reflect on how much you’ve done across a career in this space, and we do spend a lot of time, I guess, focused very much on the task that is at hand, what’s right in front of us, and don’t always have the opportunity to sit back and reflect on the span of our activities. Yeah, so I thought I’d just get going by asking, perhaps starting with you, susan, if you could tell us a little bit about Lighthouse Foundation, the work that you do and perhaps even how you came to found Lighthouse Foundation all those years ago.

Susan: 6:52

Yeah, thanks, colby. Well, it’s a bit of a long story so I’ll try and encapsulate it very succinctly, but I actually started probably 43 years ago. But I actually started probably 43 years ago showing my age, and I happened to. A group of Australians were supporting a project over in Vietnam, and then there was the fall of Vietnam. So we had to refocus somewhere else with our wish to make a difference, and that place ended up being Sri Lanka, and we found out in Sri Lanka they needed a nurse to help and set up a nutritional crèche for all abandoned children, and so we sent money over and the French nurse was employed, and then she arrived and realised there was such an enormous task to set up. She put out an SOS to the global community for anyone that might be able to come and help her, and so I’d never been out of partly my suburb, let alone my country, before, and I strangely put my hand up and found myself over in Sri Lanka.

Susan: 8:07

My mum was minding my two sons and I thought it was going to be a very short stint and it ended up being a little bit more elongated. But what happened there was she asked me to take a really sick baby to the infectious diseases hospital. While I was there I noticed a severely malnourished baby with abscess, scabies and flies sucking on it. I was just stunned that that would happen to children, because that doesn’t happen in our country. And I in that time also saw many babies languishing in cots three at a time in excrement, and it so shocked me that that happened in my world. And I looked at myself and I wondered couldn’t I be doing more about this and shouldn’t I be doing more about this? And who was I as a human being that was allowing this to happen? And I was looking at it and had no power to intervene. And I found out that one of those little babies died and I came back to Australia a really different girl, one that knew that I couldn’t live in the world and see that going on in my watch and do nothing about it.

Susan: 9:32

And I knew then that I needed to find out more about myself and what was holding me back. And I started then looking at what was happening in Australia around homelessness and realised, although our children weren’t dying of severe malnutrition, we had one of the highest suicide rates in the Western world. And that stunned me and I thought but I love teenagers so much and I guess that was a seed that germinated and to the point where I thought, oh, I can foster children. And I found out that kids over 16 that didn’t have money attached to them was so easy to be fostered. You know, they’re almost pushed at you and before I knew it I had a home full of children. It started with a little Aboriginal sibling group and then it grew to having including my own children. I had 16 kids living with me and was looking at fostering another one and went oh my god, I’ve run out of bedrooms. And when I started eyeing off the bath and thinking I could put a mattress in there, I knew that I was stepping out of what I was doing, which was loving these children, to really setting up another orphanage.

Susan: 10:54

And at the same time I happened to my cousin, thought I needed help and sent me to a course called Money Anew, run by Robert Kiyosaki, who wrote the book Dad, rich Dad, poor Dad, and If you Want To Be Rich and Happy, don’t Go To School. And that kind of sung to my heart a little bit, because I’d only gone to year 10 and my stepfather then pushed me out into the workforce before I was ready, and so going to that course changed my life. He taught me about the processional effect. You know, the honey doesn’t really know what they’re doing, they’re just going from tree to tree, but it makes honey, and so if you’re on course, what you’re meant to be here on the planet to do the rest falls into place. He taught me about policies and procedures and, most importantly, he taught me about franchising. He said so you need to do what you’re doing. That is having such a strong outcome compared to the system that you need to duplicate that. Well, I thought he was mad and I thought, oh, how am I ever going to do that?

Susan: 12:08

And at the time we got some funding from one of our philanthropy supporters and they paid for a psychologist to come on board.

Susan: 12:20

And so Dr Sarah Crome, our first psychologist, followed me around for a year and looked at what I was doing organically with the young people, which is really just loving them so much.

Susan: 12:32

And my measurement was how much I love my own children and I’m so territorial about my kids. You don’t come. I say you don’t fuck with my kids or you deal with me. That’s how you know kind of territorial I am, and it was my measurement to know if I was doing the best job I could is to measure my love for them against that of my children and to make sure I kept working on that until I did that. And Sarah Chrome really was the first person that put all that I was doing into a framework that had a psychological underpinning and references to it, and really it was just attachment and relationships, loving and object relations, and so that was really. The rest is history. We went from there to having an independent report done just a couple of years ago that 87% of our young people leaving us never into homelessness again and changes the trajectory of intergenerational trauma.

Colby: 13:42

Wow, that’s wonderful. What an inspirational story. And Ben or Susan, one of you, I wonder if you’d like to just kind of expand a bit on what the Lighthouse Foundation is doing at this time, what their services encompass? Yeah, thank you.

Ben: 13:59

Cobby, certainly so. Ultimately, lighthouse Foundation is a trauma informed organisation that supports children, young people and families here in Victoria, australia. Our key modalities of healing are through relationship. We support with caretakers who don’t do too, but be with children and their families. And, as Susan explained, time is a critical component to healing to allow deeply ingrained expectations of people and self to change. It can be very slow but deeply meaningful work. I believe we provide a sense of belonging. The community helps young people to feel safe and accepted and part of something meaningful. We’re purposeful with intention. We respond with empathy and understanding that you know.

Ben: 14:47

Children, young people, may have had a bad experience, but they’re not bad people and through season susan’s vision and values, we we believe in you and we put great thought into everything we do.

Ben: 14:59

I’m privileged to work alongside young people and carers in our therapeutic residential care homes. So we have a Young Women’s Freedom Programme which supports young women who are survivors of forced marriage and modern slavery. We provide them a safe therapeutic environment to heal. A Young Parents and Babies Programme which core aim is to support young parents to heal from their own childhood trauma in the hope that they can raise babies free from those inherited emotional wounds and we support young people who’ve often experienced complex trauma, who are unable to live with their biological families currently, and we support them up to 25 years of age within therapeutic residential care homes, which is a different experience to many organisations who are kind of maybe forced to stop providing care at 18. We continue to provide care to 25 and actually much longer through our on for life program and sense of belonging so our on for life is really important to us and probably what sets us apart.

Susan: 16:03

Um, we we were, because we didn’t at the time get any recurrent funding. We were able to create Lighthouse, really in the way we thought was best practice for young people, and really we looked at what families do. It’s a family system and you know my kids, god, they come back when they’re 40. I don’t think I’ll ever get rid of them. You know, with six of them, there’s always someone at home or someone that needs moving or someone that’s broken, their washing machine’s broken down or all the sorts of machinations of what a real family is.

Susan: 16:42

And exactly like our young people, some of our young people now on our Alan for Life program are in their early 50s and it’s such a joy for us to see them coming back, even if it’s because of relationships broken down. How, you know, we can walk beside them to help them, give the time and space for them to think and see what their next steps are, but also to celebrate with them when their child’s growing up and getting married themselves or having a child or um, you know, we’ve got a couple of our kids that are millionaires now and and then we’ve got other kids that have got, you know, know mental health issues, but we see them shortening the time each time they have a whoopsie. The next time they’ve learned something. So the time to get back on their feet and get going again is shorter and shorter each time. So it’s really, like Ben said, a privilege to walk beside them and sharing that joy of their parenting and breaking that cycle.

Colby: 17:50

You said something very interesting in a couple of spots in there, susan Talking. Initially you were saying how, if you’re kind of doing what you’re meant to be doing on the planet, the money tends to follow. And you’re not the first kind of founder who I’ve had on the podcast who’s said something very similar to that. If not, you know the same, maybe with some slightly different words. And I always, I mean mean, in my own practice, I’ve always followed the motto that you, you just make sure you provide a good service and uh, and money follows. It doesn’t always. It can be a bit of a bumpy ride at times, it doesn’t always follow like that, but but overall, um, it does, um, yeah, and then you and then I think, if I understood you correctly, you were, you were kind of saying um, because you didn’t have recurrent funding from, I guess, from um government funding bodies you were able to create a service based more on what you thought a service should look like in this space. You weren’t constrained by funding bodies and their requirements.

Susan: 19:15

No, I wasn’t constrained by the quantitative exercises it might be, it was more qualitative for me, but I also always did it alongside a psychologist, either clinical or community, who understood what I was getting at and could always relate it back to a framework so that it had real rigour to it.

Susan: 19:43

And I think that was probably, know, really important for me, that, you know I wasn’t just going off going doing, oh well, I’ll just love every child, and that’s what we do, but also that it had had something to um, harness to, that was of value in the community and I guess hence the book.

Susan: 20:06

You know we’ve had some fabulous psychologists I mean I shouldn’t name any because then I’ll get stuck but Dr Sarah Crome in the beginning, you know, rudy Gonzalez and Taimur Hussain had a real influence on the place. Laura Petrie, ben beside me, simon, who is our CEO, and I think you’ve had on before Simon Benjamin they’re all people that played a large role in bringing forward everything they know and adding to it. So it’s not a static organisation. We keep learning and growing and as we branch out to different um I guess for one of the better word young people or cohorts as some people call them um, we have to change and grow and think more and think differently. So I think that’s also important that we can then relate it back to well, how does that have an underpinning with a psychological framework?

Colby: 21:09

Yeah, and you referred to attachment theory and being one of those significant frameworks. Yes, yeah.

Susan: 21:17

Yeah, well, I used to call it love and I get myself into trouble all the time, so it’s much better to say attachment.

Susan: 21:24

But it’s really about a relationship and children grow in the love of someone. You know, I think it was Chilton Pierce that said it only takes one person to love a child and they’ll usually make it through and that’s always been my experience, even young people that are suicidal. You know, if you can hold with them and stay with them during that really difficult time, they’ll usually find a little spark of hope and see it through and get out the other side. So I always see us as a containment. You know, a great big glass bowl of holding and the young people, you know a great big glass bowl of holding and the young people, you know, grow and learn in that until they’re ready to do their interdependent living, you know, outside that containment area. So for us it’s about giving them the opportunity and the time, as Ben said, to grow and learn and have hope. You know, and I think if you can find a spark of hope for them, that’s really what will. You know, see them through, and that’s love and attachment.

Colby: 22:36

And, I think, especially suicidal young people. You know having that experience of being a person of worth. When you love a young person, their experience of that is that I am an adequate, worthy person. Yeah, and young people, indeed everyone who has a healthy sense of their own worth, or has at least some semblance of a healthy sense of their own worth, or has at least some semblance of a healthy sense of self-worth, do tend to make better decisions for themselves in their life. Going forwards, ben, I want to go over to you because we kind of skipped past you a little bit, but you have an accent. You started your career in the UK. How did you come to be working in this space?

Ben: 23:31

Yeah, thank you, colby. Yeah, that’s correct. Yeah, so I actually started off in play in primary schools. I couldn’t believe my luck when I was offered the chance to be paid to play football. It wasn’t quite the Premier League but I was having a great time in primary schools, great joy alongside the children, and it was one of the head teacher there saw my kind of ability to be with children and help co-regulate I wasn’t quite sure of that terminology at the time. She invited me to work in the primary school and support children.

Ben: 24:18

At the time it was in the UK, there were music professionals who had social, emotional, behavioral difficulties and social, emotional, behavioral made sense to me. The social experience of where the trauma may come from. Then the emotional impact. Then we see that through behaviour and I was unsure on the difficulty part, like maybe difficulty for the young person but certainly difficult for the school to tolerate and accept as well. And it was in the school environment. A wonderful school and a wonderful head teacher who was really focused on community, would integrate families. They would have alternative educational on a Friday, cooking and play experiences.

Ben: 25:00

But I saw a young child steal food from a lunchbox during. I think she’d excused herself from the class and I witnessed that and I saw a teacher and I saw that experience and I thought, oh, clearly the child’s hungry, maybe they need some food or have not had breakfast or I’m not sure what’s happening in their home life. I saw a teacher come out and I expected them to provide that level of care but instead they shouted at the child for stealing and it just didn’t make sense to me and it just didn’t make sense to me and I thought I think I need to work in an environment, more in a home setting really. So I found myself working in a 20-bed residential care community setting. There was three homes on site. It’s like a developmental process where the children would move through homes on site. It’s like a developmental process where the children would move through.

Ben: 26:01

We had a school in the middle, mechanics, um vegetable patch and you’d live there for a week alongside the young people. Then you’d have a week off and that really gave me an experience of the importance of relationship and containment and living alongside that, what that can offer. And it’s a beautiful setting, not too dissimilar to Hurstbridge farm, like adela holmes spoke about, but there wasn’t the systemic levels of holding for staff to process, being that close to uh, expressions of trauma, and I noticed I was starting to get quite physical symptoms of back pain, um, which I thought was from a, an injury, um, but had a, had an MRI scan and, um, there was nothing physically wrong. So it got me thinking about, um, the unconscious, really, um.

Ben: 26:47

I moved to another organization called Fairways and there was a mentor there called Michael Crutchley, who was a mental health nurse, um, and we go out and ride our motorbikes together and each share stories with me about high quality forensic residential care, which included, uh, the book that susan rudy and patrick um published, and, and we also spoke a lot about pepper harrow, which was so interesting. But richard rollinson was on there and had a community, had decision-making together and involvement, and I believe that the only this is my interpretation the only kind of expectation is that you came to a community meeting every day and ruptures were repaired. So, after reading the book that Susan had published, I convinced my I was assistant manager at the time at Fairways and convinced my wife to quit our jobs and fly to Australia, and I was lucky enough to become a therapeutic carer in 2018 at Lighthouse Foundation.

Colby: 27:48

Wow. Well, that’s an incredible story as well. Thank you, ben, and we’ve obviously had a bit of a chat before this podcast, you and I, ben, so I’ll come to a couple of things from that, but I couldn’t, I couldn’t leave behind. Move on. I guess, before just going back to something that you were saying, susan, about in in the correct parlance it would be after care, but the decision that has been taken by Lighthouse to continue to provide support, direct support, right through to 25 and indeed subsequent support it reminded me a lot of what Kieran Modi, who was on the podcast from Udayan Care, was talking about in terms of they support through to 25, and then they have alumni and she does a lot of work, or her organisation does a lot of work in terms of supporting care leavers. It was also mentioned by the Livramento people in Portugal, but if you can just tell us a little bit more of your thoughts behind how, I guess how Lighthouse went in that direction of supporting young people beyond 18.

Susan: 29:15

Funnily enough, I’ve been over to Kira Modi’s place and she’s been over here, probably about eight years ago, to look at what we were doing, and we talked about the importance of On For Life and having a psychologist with your team to make sure that the frameworks, to make sure that the frameworks keep evolving. And our book’s been translated into Portuguese and Japanese, so now I know the link, which is good. But for me it was really again modelled on the way I cared for my young people. And you don’t stop being a mother and a parent just because they’re moved out people. And you don’t stop being a mother and a parent just because they’ve moved out. In fact, they’re at age 16, 18, 20. Even if they’ve come from a really good enough family life, they still aren’t always quite ready to do it alone. They always need an attachment or that umbilical call that brings them back to ask questions or check in and all that sort of thing. And so it was really important for me for us to develop that against a lot of pushback at the time, not so much at Lighthouse but with the system. You know the Australian system and how they operated but I was determined that we were going to do that, and so we just pressed on.

Susan: 30:40

But we also developed from there our community committees, because I think young people need not just their mum and dad or one parent, they also need a network of people, like you do when you come up in a family, you know you’ve got your school parents and your parents have got friends, and so you become part of a strong, resilient group, and so I wanted to build that for the young people.

Susan: 31:12

So another unique thing about Lighthouse is every time we open a home in a community, we build a community committee around that home, and the importance of that is that they’ve got all these surrogate parents and brothers and sisters and aunts and uncles and what I call corporate parenting, where everyone can take some responsibility for caring and nurturing and developing these young people.

Susan: 31:43

So on the community committee there might be a school teacher or a policeman or a person that’s lost a child to suicide or the local I call it the butcher, the baker, the candlestick maker and they all come together to parent that child. And it’s just been quite amazing really, some of the things. Some of them have become foster parents of a 16 or 17-year-old and said well, before they transit into, you know the community. Why don’t they come to live with me for a year or two and let them see parenting as we do it? So when they become parents they’ll have learnt something. So they’ve all you know there’s been some amazing stories of people. I keep saying I’d love to write a book about all the people that have been part of those community committees, that have got stories of their own and what brought them to help me parent these young people.

Colby: 32:43

That’s remarkable, and how do you access them, susan?

Susan: 32:50

Again that processional effect. I just go out and tell the story, anybody that reaches in or anyone that donates, even if it’s a dollar, to me they are the king and queen of the place. If it’s a dollar or if it’s a million dollars, I love them all the same because all that helps. But going to Rotary meetings I’m a Rotarian myself going to talks at corporates, just I say yes to everything because I think I was saying to you at the beginning, there’s a really deep responsibility that I’m a conduit for the young people who can’t tell their story to those who don’t know their story, and if I can share part of their story with their, okay, then most Australians want to help in some way. I’ve just got to provide that pathway for them to be able to do that.

Susan: 33:49

And everyone’s pathway is different. Some don’t want to have any contact with the young people. Others want to be right in there and helping the house and doing a barbecue every week, or you know things like that contact with the young people. Others want to be right in there and helping the house and doing a barbecue every week, or you know things like that. So just finding unpacking what it is they want to do to help this young person. An example might be the ANZ in August are putting on a big Diwali event and there’ll be thousands of people all doing Indian and Sri Lankan dancing, and that funding will come to Lighthouse and we’ll be able to promote and tell our story there. So I’m not just telling it for the day, but there’ll be people there that then want to do workplace giving and donate $5 a month, you know and so they become a surrogate parent in their own way.

Colby: 34:39

So there’s all sorts of ways you can parent, I believe, and so we just have to find that in each person that comes forward again, it reminds me of the work that Kieran and Udain Care are doing as well, the way the, the way in which they use volunteers in their model of care. And you know, I just highlight the similarity between the two to make the point that it is possible to one access people who are concerned and committed and really want to be part of facilitating better life outcomes for children and young people in need, and there are really positive ways to utilise those people for the benefit of the young people.

Susan: 35:35

Yeah, and just on that. I think the important thing to then remember is that the level of support and screening you give and so we do psychosocial screening, and to me that’s a real key to keeping the organisation safe, just to mention that, yeah.

Ben: 35:56

Yeah, yeah, yeah, yeah, and that’s a really important integral function of the forensic care we offer. So we don’t really ask of young people what they’re not willing to do for ourselves, and a psychosocial screen really allows us to understand people’s unconscious motivations to be in the work. Do they have a reflective capacity, emotional capacity and are they willing to ask for help, which we think is a really important component? Some of the committee members we have a chair of our Young Women’s Freedom Programme who I believe has been 14 years but before her her brother looked after it for about five and then all her family are involved.

Susan: 36:34

So it’s like her home and I’ve almost got to put my hand up to see if I want to tiptoe in. And there’s Rolf Tedisco, who’s an immigrant from Italy. He wanted to open a home. I said, oh, the governance around it. Rolf is so overwhelming, why don’t you do it under our umbrella? So he’s got the Springvale home who takes care of most of our really pointy and young people and he’s proud as punch and he’s been with that probably 25 years now, you know. And so when people come in, their loyalty and long-term commitment is probably what we look for, and honour in those people and the emotional intelligence of our staff really is what we look forward to that warmth and humanistic qualities.

Ben: 37:25

Yeah, it’s interesting. I’m sorry, colby.

Colby: 37:27

No, I was just going to you first, because people want to hear more of you and less of me.

Ben: 37:34

I was going to say that chair I was speaking about uh katherine. She’s also on our care subcommittee, um, so the the openness of communication goes throughout the organization. So she’s there to uh hear stories, share stories of the young people, what she sees, and provide a voice to the ceo and the care subcommittee. Members of the board, just to help us keep on track really and monitor for drift.

Colby: 38:02

Yeah, yeah, well, that, yeah, it’s interesting. It seems to be an opportune point to bring in that, and I have flagged this with you that we’ve started a little an aspect of the podcast where we get the previous guest to think of a question to ask the next guest on the podcast, and so I’ll be making, or have made public, patricia Sheridan from the Moore Group’s podcast today. Now, the question that she put to me, apart from she wished me to pass on her best wishes to you and your organisation, what really was around this issue of fidelity, which I think you’re starting to touch on in what you’re saying now, ensure that the carers that you have in the organisation remain aligned with the values of the organisation.

Ben: 39:07

Yeah, thank you, colby. Well, I think the psychosocial screen is a fundamental component of that. I think it sends a real clear message to therapeutic carers and it’s not just carers, everyone amongst the agency. I think it sends a real clear message to therapeutic carers and it’s not just carers, everyone amongst the agency. I think Simon spoke about that. We expect the same from our finance team and our marketing team that the primary task is the children and young people. So we’re interconnected to make sure that we remain focused to the quality care of children and young people. And the psychosocial screen sets us apart there. I believe you know it’s communicating to young people, to carers. We take this work seriously, um, and with kindness. Uh, so if you enter lighthouse, that’s the expectation a deep level of thought and care, um, I’m happy to share a little bit about my own experience of psychosocial screen, where I’d said to Andrew, who was the manager of clinical services at the time, I said, oh, I’ve done something similar to like this before at Fairways.

Ben: 40:11

It was a print profile, because they ask you what do you think your unconscious motivations may be? And this was, you know, was seven, eight years ago. I hadn’t done as much internal work or thinking at the time and I said, oh, it said I had a desire to feel special. And he said, oh, why do you think that’s where that’s come from, ben, and I wasn’t aware at that time that I am. Now I said, oh, I’m not sure, it’s just a test. And he said, oh well, lighthouse, we encourage you to think into those parts of yourself. And that’s really important actually, because as a therapy carer, I need to be aware of my own emotional availabilities and what might light me up to make sure that doesn’t impact the work of the children and they remain focused. So I mean, that’s an important, a really important part of my learning. Really, we’re a learning organization.

Colby: 41:07

It expects deep, deep thought and I think all my podcast guests, who are representatives of well-respected and, I guess, successful however you might define that have talked about the need for fidelity, the need for alignment through the whole organisation. Simon talked about Simon, benjamin talked about. You know what we do with the kids? We do with everyone in the organisation. There’s that alignment all the way through.

Susan: 41:45

And particularly, you know it has to be the board included. And to get you know a whole lot of professional people to talk about their feelings is hilarious. However, we’ve managed to hold on to that probably more challenging aspect of it. But it’s really interesting that once people get into the habit of it, after three or four months they actually they’re the ones calling for it. They actually they’re the ones calling for it and there’s something intangible about the warmth and connectedness you get from sharing your feelings at a board level that they feel and take away with it. It’s actually they don’t want to leave the board and we have board members 12, 14 years.

Susan: 42:38

You know that long-term loyalty, which is fabulous, I know, from a governance perspective, they like changing you. You know there’s three year on three year, but there’s something to be said for. You know, having those grandparents around as well as new blood staying on board and holding the culture throughout and having that emotional intelligence and then having to share the journey alongside the young people in that way that they’ve got to do the same practices, I think holds us all together. And when you do get wobbly because there’s always times no matter how great you are, you know you have different leadership and different people coming into the organisation and you grow wider and so you’ve got to make sure even more that you hold tight to those. You know different practices that we have and hold them dearly.

Ben: 43:40

Now I can speak to that a bit more, colby, if you like, because, as we spoke about, the model of care has kind of evolved and adapted. It’s like a living thing and it’s kind of since Susan and Patrick and Rudy, yeah, it kind of developed the model. It was co-designed, youdesigned with Patrick Tomlinson, which I think was really important because it shows a level of involvement and ownership for the organisation, and since then it’s kind of evolved to four key domains really, which is the home, a home environment where you want to provide a secondary care experience where the home is a warm, beautiful home. That is maybe different to what our children and young people have experienced of feeling worthy. We have young people interventions, so that could be a daily, weekly and monthly intervention. So we have daily reflections that the carers are involved in. We have weekly one-to-one times where the carer or the psychologist are solely available for the child for that time, whether they wish to step in or not. We will hold that space and that’s the same for the carers.

Ben: 44:46

We have weekly clinical and operational supervision, depending on the program and the level of need required for those children. That may be fortnightly of program and the level of need required for those children. That may be fortnightly, um, but I’ve recently gone weekly, uh, and so has the clinician in in the focus of central care program. So we’re trying to um step in early, really, before feelings get too big for staff, um, and understanding young people. When you say it out loud, an hour a week, there’s only 52 hours, you know. A year it’s not actually very much, but people seem to think that’s too long to sit and be with, yeah, and then, as I said, we have community, which is an important component as well, and we contract all our prognostic carers to engage in reflective practice. So you can’t extend the clear communication, communication really. Now, if you want to be part of this organization and care for young people, we expect that practice of you, um, and I can share an example from this week, if that’s of helpful around focus on feeling and how that supports, uh, our understanding of children, young people go ahead, yeah.

Ben: 45:57

So we’ve just recently opened a new Fremont residential care home, so the young person has recently returned to the area, which can be quite scary. We believe it to be of great benefit to be closer to family and we’re hoping to interconnect in with family and bring them into the residential care home, but ultimately still a scary experience to leave people that you’ve, you know, the safety of their old residential care home in those relationships, to come to somewhere new. And we had a phone call on the weekend where the young person had asked I’m out with my friends, can you come and pick me up? And then he he said, oh, I have a weapon. And I was unsure, you know, did he have a weapon or was he just feeling very unsafe? Because I’d read in the referral previously that when he changed homes before you know, he was found with a weapon on him or seemed to have a weapon, we believe, communicating this feeling of unsafe. So the group really took it serious. Um, and I spoke to the carers directly on the on the uh in the home and they said no, benny, it sounded like um, he didn’t sound like he was joking. We need to take him seriously, which we did, you know. We enacted a process to go up and make sure he was safe and our carers were safe and brought him home and he fell asleep in the lounge and they put a blanket over him.

Ben: 47:18

Um, and then I still attend the reflective practice space alongside the carers, uh, fortnightly in in the home, um, and they were speaking about a razor. They were saying, oh, we’ve seen that, we’ve noticed the razor in the shower and it was getting quite big for them, the razor. They were saying, um, you know, he’s moving into adolescence. It’s quite an important part of development. It’s something you sometimes do with your own father. And then they say, but we want everyone to be safe.

Ben: 47:46

And then they were coming up with a uh, an intervention of like well, maybe you know, we could get a lock box and he can have a key and we can have a key and we can lock it up. And I, we’ve asked him to focus on the feeling. What is the feeling that the razor has given you? And it’s one of um. You’re feeling quite unsafe and scared, and that gave us an insight into how he may be feeling in his world.

Ben: 48:08

Where we hadn’t focused on the feeling, you could see how that, you know, intervention of the razor could really escalate.Ben: 48:14

But that wasn’t the case.

Ben: 48:15

We were able to bring in one person, brought in the feeling of um, how he may have felt like a black sheep of the family was his words many years ago, another one was able to hold on to like the empathy and hope, um, and then so the group could hold that and tolerate that distress, um to respond with empathy.

Ben: 48:34

So when he called a couple of days later and said, you know, started to give him and his friends started to give the character a bit of grief, ultimately, on the phone they were able to say, oh yeah, if Billy’s there, let him know we’re thinking about him and we care about him, which was a really important message not just to him but also to his friends. There’s adults out there who show you care and think about you, where if we hadn’t had that space on feeling they may have been reactive or put the phone down. And actually the fact he was calling us when he’s outside the home, when he’s new, was a wonderful win for us. It shows that he’s holding us in mind when he’s not in the home and that’s what you know we do as well. We we hold our young people in mind.

Colby: 49:20

Yeah, lovely yeah, there’s so much we could talk about um.

Colby: 49:27

I wanted there was something just going back to to what you were saying as well, susan, before um, talking about um reflection, holding, you know, holding people in mind, but also reflecting on what’s happening for us and having that experience of sharing and other people connecting with us around our experience.

Colby: 49:56

And you talked about how people, for example, on your boards or committees hanging around for a very long time and other family members getting involved, and the thought that was going through my mind is that this jurisdiction is probably more characterised by staff just going through the system at a rate of knots. Yeah, that there is a lot of changeover in the workforce in these jurisdictions, maybe not in your organisation, but certainly in this jurisdiction, and what I had in mind listening to you talk about um, your experience there at lighthouse, was the importance of um not just the children being feeling heard, but but the staff, or the everyone connected with organisation, feeling heard and acknowledged and valued around their experience, which is, I guess, another way of talking about you know what we do with our children, with the children we should be doing at all levels of the organisation, as Simon said. There’s one thing, though, that I really wanted to also speak to you guys about, which is the involvement of birth family.

Ben: 51:26

One of you mentioned that I think it was you, ben no families.

Ben: 51:31

Yeah, families, and from our pre-meet conversation, ben, you talked a little bit about that and I think it would be really useful at this juncture to hear a bit more about how Lighthouse connect with involve birth families. You want me to go? Yeah, yeah, thank you, colby. I guess we really ultimately think that children have been abused by their parents. They don’t really stop loving their parents, they stop loving themselves and we really see parents as an integral part of their identity and their healing process. We all entered the world attached to our mothers, as Susan said, and a lot of the time we crave that attachment to our families to remain. We work non-judgmentally with our parents and we really try to understand their own history and involve them in the young person’s experience and their own experience and clear that we’re not the parents that they are.

Ben: 52:36

When I was a care in our secure base program, every Monday I would meet a father in the park so he could play with his son and play on the swings or ride bikes together, and I was just there in the background providing support to them both. That was enabled to transition into one of our residential care homes where he was able to get the experience of really he would like own the barbecue cooking for his son. Read his son a story. Kiss him good night to bed, um, and then him and I would just, you know, sit together once his son was asleep, you know, have a cup of tea and chat. And he would also come to Youth Resource Centre here, which is the heart of the organisation.

Ben: 53:27

He may do parental courses, like Circular Security, alongside some of our other staff members, and there was an experience once the sense of safety was kind of formed with all of us, that the child was able to sit alongside his kind of key carers not not myself, but some really important people in his world in the living room and he was able to say to his father um, you know, where where were you? Why didn’t you keep me safe? Um, and the child was crying and the father was crying, and whilst the father couldn’t give him an answer, he was able just to acknowledge it and apologise and that was all the child needed. Really, he didn’t need a fix, he just needed to be heard.

Ben: 54:08

And once that young person was ready to kind of fly the nest from lighthouse, we also created a book for the father of memories that we had together and stuff that we’d learnt from him, and he was able to say you know, I wish I had a lighthouse when I was a child, so really we’ve got great respect for families and, yeah, really think deeply into their own experiences and try to involve them as much as we can. Yeah, really think deeply into their own experiences and try to involve them as much as we can.

Colby: 54:39

Yeah, yeah, I am on record as saying the most healing relationship for our children is the relationship with their parents. Yeah, the most healing relationship. Yeah, that leads into Ben. We also talked a little bit about the Mothers and Babies Program, and I was keen for you to talk a little bit about that as well in our time together.

Susan: 55:10

And keeping our siblings together too. Yeah, the White House.

Ben: 55:14

Yeah, of course. Yeah, yeah, I’ve been lucky enough to work in our Young Parents and Babies programme. I believe it was started with yourself and Vicky Vidal, Susan, is that correct? Yeah, and really at. Its aim, as I said, is to support young parents to heal from their own childhood trauma in the hope that they can raise their own babies free from these inherited emotional wounds. Ultimately, we’re trying to provide an environment where we care for the parents so they can care for their children, the developmental programme, so as the young people kind of attach and join, we’re just really trying to see if they can seek support and receive care for parents. It’s a really wonderful programme.

Ben: 55:59

You get to see changes very quickly, as you know, in the first two years of life, and we’re similar to what we were saying in reflective practice. We’re there with kindness and boundaries, but we don’t rush things. We allow things to kind of percolate and come to fruition. So an example of that is we had a young mother who I’m very proud of. The experience that she received of what she gave her children is very different and when she first joined she was unable to play with her children. But we just noticed that and we would role model, play ourselves, you know cues and um, bedtime routines and things like that. And one time she was able to say, um, yeah. Then in time, we saw her starting to push the child on the swing or, you know, play with the trucks, etc. Take an interest in their world, and she was able to, you know, many years later, reflect to us that, um, when I was a child, playing was very terrifying because it it meant abuse. Um, you’ve, you’ve taught me how to play with my children, so, uh, she was very grateful for that um. But if we’d rushed that in the early stages, if we kind of thought, why is she not playing with her child? And tried to make that happen too quickly, we would have missed that opportunity and not playing with her child and trying to make that happen too quickly, we would have missed that opportunity and not had given her that experience.

Ben: 57:23

We have young mums, uh, now that they kind of form a little community together, don’t they, susan? They’ve, uh, they live together now in the community and the two of them have started their own business together, um, and that they pop back. I think we currently have about 13 families uh being supported closely through One for Life in terms of like their own little community that comes together. And just a couple weeks ago I looked after one of the uh, a little boy who was six months old when I first looked after him and now would be five years old, so his mum could attend a business course on beauty just in the community. So really able to kind of come back and reach out for support when needed, yeah.

Susan: 58:09

I think that we’ve got 1,350 young people that have graduated the program now and that’s long term. So it doesn’t sound like that it is. You know, I often think you know if a young person’s been abused for 10, 15 years, that needs to be equalled on the other side of you know that good parenting another 15 years. So for me, you know, when Ben talks about about you know we shouldn’t be quantifying time, it’s when they’re ready. So I think that’s an important thing. You know, you’ve got a lot of abuse to abuse to unpack and it will take as much time as it takes and not to rush that process.

Ben: 58:56

Yeah, we had yeah in there. Something we really wrestle with in the programme is phones, you know, and the gaze that we all have towards our phones and we ask of our young parents, during kind of bath time or dinner time, that we have a little kind of clear container on the side and we ask them to put the phones in. And that can be very difficult in the early stages but, um, I’ve seen so many times after eight weeks or so, but, um, yeah, you, you notice them just being left in there overnight so they can respond to the baby. And that’s a lovely kind of it doesn’t feel that big but it’s a lovely little measure that I I take in of growth one of my previous podcast guests, um, said something very chilling, uh, at the time or it is chilling, she.

Colby: 59:49

I mean, she was talking about, um, this attachment relationship or this, this relation, relational dynamic that exists for young children, that has three parties to it the child, the parent and the device these days, and what is going to be the longer-term implications of that? I think we just yeah, we will see, but it is. Yeah, it gave me chills hearing her talk about that.

Susan: 1:00:22

Well, I think the mental health issues will skyrocket. Really, you know, unless we have some boundaries around it, you know some positive ways of dealing with it.

Ben: 1:00:33

It’s probably worth mentioning Colby that we’re realistic in our task and sometimes we may work with parents who have kind of 10 out of 10 of adverse childhood experiences on the study In time. We wish for their children to have less and their other children to have less. It’s not always realistic that we might not have an instant quick fix, but we want to give people an opportunity. Yeah, and I think that’s where that program is philanthropically funded, because it’s very hard.

Susan: 1:01:11

We don’t get a lot of recurrent funding. The government have partnered with us now and we’re very excited about that and I think they’re keen to look at our model of care. We’ve got a CEO, brenda Boland, who comes from Child Protection and I think that as a leadership, she’s showing them the work we’re doing and I think they’re really excited to hear about our work and partner with us. So that’s great. But, as Ben was saying previously, we’ve really done it from philanthropic partners and to pay for two living carers, a salary you know that’s a couple of hundred thousand to run the program, couple of hundred thousand to run the program. So, um, but if you look at you know incarceration and that long, long term consequence. We’re much better doing that early intervention piece and putting the time and money and investment into our young people early.

Susan: 1:02:13

But it is always a challenge for organisations that aren’t recurrent funded. So one of the things probably in our world and of interest to you is that we’re looking at how do we self-fund into the future. So we’re looking very much at getting a futures fund established so that we’ll be able to live off the interest rather than continually go cap in hand, and we still want to do that. We want to reach out because we believe it’s community that help heal our young people in that kind of resilience membrane that they all belong to us. But also we want to be able to, as good parents do, be able to afford. You know what we, how we live, and so we need to demonstrate that ourselves. So we’re looking at developing. We’re going out to developers to help us find lots of land. We’ve got a corporate that will build houses for us. So we’ve got a whole range of projects we’re working on to be self-funded, but it’s a long-term strategy.

Colby: 1:03:25

Yeah, yeah, that’s wonderful. I just wonder you raised the issue of government being interested. It kind of leads me into what you know if you could sit down with them and I’m sure you will what are the key things that you would want to be communicating to them about how to deliver therapeutic care to young people in need and their families?

Susan: 1:04:00

Well, I think we understand their constraints and the governance that underpins what they do, and so, really, I’m excited to work alongside them to come up with a way of working that really focuses on the best practice for young people Do you want to?

Ben: 1:04:25

Yeah, for me as we were speaking, I truly believe in residential care. I think, as we’ve spoken about, a lot of the trauma experience where our young people experience this is in a home with unsafe adults. We want to give them a secondary strength of a safe home and emotionally attuned and available adults and I find, as we spoke about, the young parents and babies program is a wonderful way of providing high quality preventative care. If the money was invested early in programs like that, you may not see the significant distress or complexities that we see in adulthood. But what I find is that often government are willing to put the money towards 16, 17, 18 years old when they’re leaving care, but not so much the preventative space of parents and children. I really think that would make a huge difference to society.

Susan: 1:05:22

Yes, so we’d encourage that as much as we can, and for us it’s about like Vicky Vida has paid for our mums and bubs home for the last probably 15 or more years, and their family have donated this building we’re in, so they’ve really given us that foundation underpinning. That is just. You know, you can’t put words on that or understand how that’s really been able to formulate our way forward but also give us a sense of empowerment to actually build a model of care we believe is second to none, and about those trauma-informed practices rather than the roof over their head. The roof over their head isn’t the main story, it’s just part of, isn’t the main story? It’s just part of. It’s the trauma-informed practices.

Susan: 1:06:23

And if we can have an impact on the way young people are cared for in out-of-home care in a much more, you know, empowered and loving way, that would be amazing for us. So, you know, and also we’re learning things from government too that we may need to put in place as well, because we understand that we’re, you know, in a lot of cases, the guardian of these young people and it’s a huge responsibility. So working as a team for us, with government as a partner, is really important for us, you know and and our next steps to have had an impact in that arena would be amazing for us.

Colby: 1:07:05

Well, I’ve really enjoyed our chat this morning and hearing more about Lighthouse, and I’m sure the people who will listen to this podcast will take a lot from it as well. So thank you to you both for coming on and for all that you’ve shared and your continuing endeavours on behalf of children and young people and families in need. I do give my guests an opportunity to ask me a question without notice. At the end, I wondered if there was anything that you particularly wanted to ask me before we sign off.

Susan: 1:07:46

Well, I just wanted to give a shout out to Patrick Tomlinson, who helped us or co-authored the book and gave us an opportunity to be global in sharing our model of care, and also Mulberry Bush for opening their place to us when we visited, and for me it’s having that global sense of community I think is very empowering for trauma, informed practices and the more we can share with each other and promote what we do I think is important. But do you want to answer that next question?

Ben: 1:08:25

No, I guess I’ll give you a talk about it the other day and you were wondering with Colby whether there’s an opportunity to create like a free music community or a group process where we could all come together to think and share our experiences.

Susan: 1:08:39

Yeah, like every two months is there an open forum where we can all share and have an agenda. But you know whether that’s possible or not.

Colby: 1:08:49

Well, it’s interesting because you will have heard, I guess, from the podcast that I’ve done with people in the UK, and Simon brought it up as well, was the community have heard, I guess from the, from the podcast that I’ve done with people in the uk, that they there’s, and I and simon brought it up as well was this the community of communities?

Colby: 1:09:03

yes, that they have yeah that they have in in the uk where there’s a number of org, social care organizations, that um meet collectively, I look, as I understand understand it, I should say and that they kind of order each other as well to kind of keep yeah, keep in a supportive way to keep everyone you know on track and maintaining the vision of those organisations. I think it’s a really interesting point that you raise, susan. Let me first say that Patrick and I talk a lot about this podcast and he also puts me in contact with a number of the podcast guests that we’ve had on, in contact with a number of the podcast guests that we’ve had on. He’s a remarkable individual who has a global network, and so I think that question is probably one that I would like to have Patrick’s input into about a global, would like to have Patrick’s input into about a global. I think what we’re trying to do with this podcast, amongst other things, is establish, in a way, establish a place where global, good or great practice, informative practice, kind of comes together, is is collected. I understand what you’re saying it would be good to to have a forum. Oh, I think it, I think it’s possible.

Colby: 1:10:49

I I think everyone who’s come on this podcast has, you know, been really excited to come on and be a part of, amongst other things, changing the story that exists around therapeutic residential care or around residential care. I do think that there are residential care being seen just as the final resort. You know the place. You send kids that you can’t send anywhere else. I think it’s got hairs all over it, as we would say. It’s a real. Even if we, even if policymakers, just continue with that thinking about residential care and its role, I think it is highly problematic. You know, like we need to. If that’s what your thoughts are about residential care, then it needs to change. You need to invest in and be a part of the change. But I, you know, the reality is, through this podcast, is that we can easily show that there are, is that we can easily show that there are fantastic therapeutic endeavours occurring in residential care worldwide. There’s more guests that I’m really excited to have on from organisations like your own who demonstrate that.

Susan: 1:12:15

So yeah, I think, yeah, it’s about having that groundswell where there’s enough of this that force policy to change because there are better outcomes and, collectively, when you evidence all that, then you’ve got. You know. Robert kiyosaki always said to me so you need to have artifacts, artifacts, artifacts a bit like like Patrick and all these books and talking about it. So you need to have that collective. If we all did something together, collectively, and it was on the global stage, then that’s when you make real change, I think, you know, rather than working in silos and pockets. But I think, as you said, your podcast is a really big part of getting that sort of you know, your kind of the linchpin to get us all together and maybe, you know, get that happening.

Colby: 1:13:09

I think it would be really exciting to do that, and all of my podcast guests, I think, who I’ve had communication with about wanting to, are willing and wanting to reappear and talk more. So I think that what you have kind of proposed is probably another way in which we can ensure that the voice of people who you know, who have substantial experience and expertise in this sector, can come together and influence.

Susan: 1:13:47

Yeah, what about a world conference with each of us speaking? Sorry, I’ve gone a bit wild.

Colby: 1:13:58

If you’re asking me, me, what I what, what I think about, I think it, you know. Look, I think I think we’re heading in a direction of their. You know we’re making these connections between good practice, um endeavors around the place. If you’re asking for me to organise it, I’d need a little bit of help. This is not my day job. I think my wife, who also manages our practice, would have a bit of a. I hope she wouldn’t have a heart attack. She’d be very supportive, but she’d be asking me where the money comes from. You know, susan, as you say and not just you, others have said as well, if it’s the right thing to be doing, if it’s the right thing to do, then yeah, the money will come, the support will come for it. Yeah.

Susan: 1:14:51

But also Robert told me about also. You’re on purpose, but you’ve got to take action as well. Robert told me about also. You’re on purpose, but you’ve got to take action as well. It’s to be, you know, be and do and be and do and be and do you know in equal measure, is you know?

Colby: 1:15:08

Yeah Well, we’ll definitely rope Patrick in to such an endeavour and others, but look, thanks again for agreeing to be on the podcast A great pleasure. Yeah, pleasure was mine as well. Thank you Ben, thank you Colin, and yeah, I’ll look forward to speaking to you another time.

Susan: 1:15:31

Yeah, well, now Ben’s not nervous anymore and me will be right, that was my question.

Ben: 1:15:37

Patrick’s very encouraging of us to come on, but I’ve not seen him on Spotify yet. I’m still waiting, yeah.

Colby: 1:15:46

I’m going to treat that as an observation rather than a question.

Ben: 1:15:51

Thank you, colby, lovely to see you in person.

Susan: 1:15:54

Thanks, colby. Thank you, bye-bye Thank you.